Use the labels in the right column to find what you want. Or you can go thru them one by one, there are only 34,278 posts. Searching is done in the search box in upper left corner. I blog on anything to do with stroke. DO NOT DO ANYTHING SUGGESTED HERE AS I AM NOT MEDICALLY TRAINED, YOUR DOCTOR IS, LISTEN TO THEM. BUT I BET THEY DON'T KNOW HOW TO GET YOU 100% RECOVERED. I DON'T EITHER BUT HAVE PLENTY OF QUESTIONS FOR YOUR DOCTOR TO ANSWER.
Changing stroke rehab and research worldwide now.Time is Brain!trillions and trillions of neuronsthatDIEeach day because there areNOeffective hyperacute therapies besides tPA(only 12% effective). I have 523 posts on hyperacute therapy, enough for researchers to spend decades proving them out. These are my personal ideas and blog on stroke rehabilitation and stroke research. Do not attempt any of these without checking with your medical provider. Unless you join me in agitating, when you need these therapies they won't be there.
What this blog is for:
My blog is not to help survivors recover, it is to have the 10 million yearly stroke survivors light fires underneath their doctors, stroke hospitals and stroke researchers to get stroke solved. 100% recovery. The stroke medical world is completely failing at that goal, they don't even have it as a goal. Shortly after getting out of the hospital and getting NO information on the process or protocols of stroke rehabilitation and recovery I started searching on the internet and found that no other survivor received useful information. This is an attempt to cover all stroke rehabilitation information that should be readily available to survivors so they can talk with informed knowledge to their medical staff. It lays out what needs to be done to get stroke survivors closer to 100% recovery. It's quite disgusting that this information is not available from every stroke association and doctors group.
Scientists have demonstrated how nasal drops containing a particular
molecule can help mice recover from the damaging biological consequences
of a stroke – and the hope is that the treatment could eventually be
transferred to humans.
Crucially, the treatment isn't applied straight away but is
initiated seven days after the stroke. That means those who are unable
to be assisted immediately after a stroke could still be protected
against the worst effects of the condition.
The key molecule in
the drops is the complement peptide (a chain of amino acids) C3a, which
we already know plays an important role in the body's immune system, as
well as in the development and plasticity of the brain.
"With this method, there's no need to race against the clock," says neuroimmunologist Marcela Pekna from the University of Gothenburg in Sweden.
"If
the treatment is used in clinical practice, all stroke patients could
receive it, even those who arrive at the hospital too late for
thrombolysis or thrombectomy. Those who have remaining disability after
the clot is removed could improve with this treatment too."
The delay is actually deliberate. Applied too early, the C3a
peptide can increase the number of inflammatory cells in the brain,
where they would start doing more harm than good.
Scientists
induced an artificial ischemic stroke, the most common type of stroke
there is, in mice. After a week, however, the nasal drops proved to help
mice recover motor function faster and more completely, compared to a
placebo group.
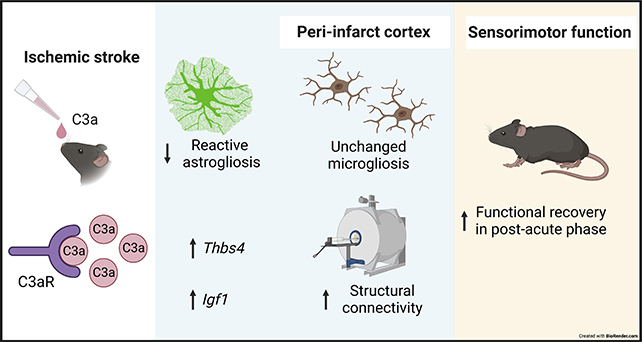
C3a was shown to help mice recover their motor function after a stroke. (Stokowska et al., Journal of Clinical Investigation, 2023)
The new study also gives us a better idea of the effect of C3a on the brain. MRI scans revealed that the peptide helped to increase the number of connections between nerve cells in the brains of the mice.
"Our results show that the C3a peptide affects the function of
astrocytes – that is, cells that control many of the nerve cells'
functions in both the healthy and the diseased brain – and which signals
astrocytes send to nerve cells," says neuroscientist Milos Pekny from the University of Gothenburg.
The study builds on previous work
by some of the same researchers into how the C3a peptide can protect
against and reverse stroke damage. That they were able to repeat their
results demonstrates the potential of this particular approach.
Some 7.6 million people
a year experience an ischemic stroke, with more than half then going on
to develop some kind of physical or mental impairment as a result: a
loss of voluntary movement in an arm or a leg, speech disturbances, or
issues with depression and anxiety.
Nosal
drops with the C3a peptide could make a massive difference in those
figures – though we're going to have to make sure that the treatment is
viable in humans as well as mice first. We can add it to the list of several possible options researchers are exploring.
"Our
ambition is to develop the method to make it usable in clinical
practice, but to get there, and especially to be able to carry out the
necessary clinical trials, we need to team up with a partner in the pharmaceutical industry," says Pekna.
Researchers push the boundaries of how late is too late for intervention
by
Nicole Lou, Senior Staff Writer, MedPage Today
December 27, 2022
Last Updated December 28, 2022
Endovascular thrombectomy (EVT) benefited select
stroke patients presenting beyond 24 hours of the time they were last
known well, a small observational cohort study showed.
Compared with such very late-presenting stroke patients receiving
medical management alone, those selected for EVT were more likely to
achieve functional independence at 90 days (38% vs 10%, adjusted OR
4.56, 95% CI 2.28-9.09), according to SELECT Late study investigators
led by Amrou Sarraj, MD, of Case Western Reserve University in
Cleveland.
The between-group difference in functional independence, defined by
modified Rankin Scale scores of 0-2, persisted after propensity score
matching by clinical characteristics, CT findings, and perfusion
parameters (45% vs 21%, adjusted OR 4.39, 95% CI 1.04-18.53), study
authors reported in JAMA Neurologyopens in a new tab or window.
As for safety, EVT was associated with reduced mortality (26% vs 41%,
adjusted OR 0.49, 95% CI 0.27-0.89) but more symptomatic intracranial
hemorrhage (sICH) at 24 hours (10.1% vs 1.7%, adjusted OR 10.65, 95% CI
2.1-51.69).
"Our data demonstrated that EVT is feasible and may improve outcomes
in very-late window patients, albeit with increased risk of hemorrhage,"
Sarraj and colleagues wrote. "This finding, along with evidence of
viable ischemic penumbra beyond 24 hours and subsequent infarct
progression with poor clinical outcomes, may open doors for EVT being
potentially offered to a carefully selected group of patients."
While the findings suggested higher probability of benefit in
patients with favorable imaging characteristics, "the observational
study design cannot exclude a benefit of EVT vs medical therapy in any
subgroup," they noted.
In the present report from SELECT Late, most patients treated with
EVT beyond 24 hours had good imaging characteristics. Over 80% showed a
presence of mismatch among those with perfusion imaging.
Predictors of that feared complication of EVT, sICH, were longer
times from last known well to procedure and Alberta Stroke Program Early
CT scores in the 0-5 range.
"Hypothetically, an increasing risk of sICH may outweigh potential
benefit in patients presenting very late with significant ischemic
changes and requires further evaluation in prospective studies,"
Sarraj's group wrote.
Meanwhile, they suggested, "Considerations of patient-level clinical
and imaging characteristics and a thorough discussion with patients and
their families about the balance of risks and benefits of EVT is
required when deciding whether to offer EVT beyond 24 hours."
The retrospective cohort study included 301 patients (median age 69
years, about half women) presenting more than 24 hours after last known
well during the period from July 2012 through December 2021 at 17
high-volume stroke centers across the U.S., Spain, Australia, and New
Zealand. Participants had occlusions in the internal carotid artery or
middle cerebral artery (M1 or M2 segment).
This very late-presenting cohort had wake-up stroke in 20% of cases; almost 80% had unwitnessed stroke onset.
Of the cohort, 61% received EVT and 39% got medical management alone.
Those selected for EVT tended to have lower stroke severity and earlier
arrival to an EVT-capable center.
Ultimately, the study was likely subject to various selection biases
that affected results, despite the investigators' attempts at
adjustment.
The researchers acknowledged that prospective studies are warranted
for confirmation of their findings, although supported by prior
exploratory studies on EVT beyond 24 hours. A randomized trial has not
been conducted for stroke patients presenting beyond 24 hours and would
be challenging to accomplish, they added.
"Patients with a very extended time since they were last known to be
well have a wide range of true onset times and therefore considerable
heterogeneity. These patients represent a very small portion of acute
ischemic stroke presentations in clinical practice, which may pose
logistic challenges for conducting a randomized clinical trial,"
according to Sarraj and colleagues.
Nicole Lou is a reporter for MedPage Today, where she covers cardiology news and other developments in medicine. Follow
Disclosures
Sarraj reported grants and personal fees from Stryker Neurovascular and personal fees from AstraZeneca.
Primary Source
JAMA Neurology
Source Reference: opens in a new tab or windowSarraj
A, et al "Association of endovascular thrombectomy vs medical
management with functional and safety outcomes in patients treated
beyond 24 hours of last known well: the SELECT late study" JAMA Neurol
2022; DOI: 10.1001/jamaneurol.2022.4714.
Whom the fuck is going do something about this? Followup studies? Translational interventions? Never mind, NOTHING WILL OCCUR. 3 earlier studies back to Nov. 2012 gives you an idea of the incompetency out there in stroke. And it doesn't need to be delivered in minutes or hours to do some good. If I wasn't such a calm and nice person I would have exploded by now. http://europepmc.org/abstract/med/29330155
High-mobility group box 1 (HMGB1) is increased in the cerebrospinal fluid (CSF) and serum during the early- and late-phases of brain ischemia and is known to contribute to brain damage. However, detailed characterization underlying cell type-specific HMGB1 release and pathophysiological roles of extracellularly released HMGB1 in ischemic brain remain unclear. Here, we examined cell type-specific HMGB1 release and therapeutic potential of amlexanox, an inhibitor of non-classical release, and an anti-HMGB1 antibody against ischemic brain damage. HMGB1 depletion from neuronal nuclei was observed within 3 h after transient middle cerebral artery occlusion (tMCAO), whereas the intracerebroventricular (i.c.v.) pretreatment with amlexanox blocked HMGB1 release from neurons, resulting in HMGB1 redistribution in the nuclei and cytoplasm. HMGB1 was selectively released from astrocytes 27 h after tMCAO and this HMGB1 release was blocked by the late-treatment of amlexanox (i.c.v.) 24 h after tMCAO. Proximity extension assay revealed that HMGB1 level was elevated in the CSF at 3 and 27 h after tMCAO. This late-treatment of amlexanox significantly protected the brain from ischemic damage, but its pretreatment 30 min before tMCAO failed to show any protection. The late-treatment (i.c.v.) of anti-HMGB1 antibody 24 h after tMCAO also ameliorated ischemic brain damage 48 h after tMCAO. Thus, the inhibition of brain damage by late-treatment of amlexanox or anti-HMGB1 antibody indicates that late HMGB1 release plays a role in the maintenance of stroke-induced brain damage, and the inhibition of this release would be a novel therapeutic target for protection of ischemic brain damage.
 (mr.suphachai praserdumrongchai/iStock/Getty Images Plus)