Changing stroke rehab and research worldwide now.Time is Brain! trillions and trillions of neurons that DIE each day because there are NO effective hyperacute therapies besides tPA(only 12% effective). I have 523 posts on hyperacute therapy, enough for researchers to spend decades proving them out. These are my personal ideas and blog on stroke rehabilitation and stroke research. Do not attempt any of these without checking with your medical provider. Unless you join me in agitating, when you need these therapies they won't be there.

What this blog is for:

My blog is not to help survivors recover, it is to have the 10 million yearly stroke survivors light fires underneath their doctors, stroke hospitals and stroke researchers to get stroke solved. 100% recovery. The stroke medical world is completely failing at that goal, they don't even have it as a goal. Shortly after getting out of the hospital and getting NO information on the process or protocols of stroke rehabilitation and recovery I started searching on the internet and found that no other survivor received useful information. This is an attempt to cover all stroke rehabilitation information that should be readily available to survivors so they can talk with informed knowledge to their medical staff. It lays out what needs to be done to get stroke survivors closer to 100% recovery. It's quite disgusting that this information is not available from every stroke association and doctors group.

Showing posts with label stroke protocol. Show all posts

Saturday, May 9, 2026

Rehabilitation of motor impairments in patients after cerebral stroke in the early recovery period using a treadmill with biofeedback

 Send your competent? doctor after the EXACT PROTOCOL! Inability to do that IS PURE INCOMPETENCE!

Rehabilitation of motor impairments in patients after cerebral stroke in the early recovery period using a treadmill with biofeedback

Abstract

Aim: to evaluate the clinical effectiveness of integrating treadmill training with a biofeedback (BFB) system into an early post-stroke rehabilitation program for managing motor disorders and improving functional outcomes.

Material and methods. The study involved 60 patients during the first 6 months after ischemic stroke. Participants were randomized into two groups: the main (experimental) group and the control group. Both groups received standard comprehensive therapy, including physiotherapy, mechanotherapy, and occupational therapy. The main group additionally underwent a course of treatment on a treadmill with BFB (Walker View), which provided feedback on parameters of the support reaction and step symmetry. For an objective assessment of dynamics, a set of clinical scales (Timed Up and Go test, 10-meter walk test, Berg Balance Scale) and instrumental analysis of gait parameters (walking speed, step length) were used. The assessment was conducted before and after a 14-day rehabilitation course.

Results. The conducted study demonstrated a statistically significant improvement in all assessed parameters in both groups, confirming the effectiveness of standard rehabilitation. However, in the main group where BFB was applied, the dynamics of improvement were better. A comparative analysis showed that these patients achieved a more pronounced reduction in the time taken to complete the “Timed Up and Go” (20% vs. 17%) and 10-meter walk tests (23.3% vs. 23.1%), a substantial increase in scores on the Berg Balance Scale (27.4% vs. 15.1%), as well as a significant increase in step length (41.2% vs. 27.3%) and no difference in walking speed.

Conclusion. The integrating treadmill training with biofeedback into an early post-stroke rehabilitation program increases the effectiveness of walking recovery compared to standard therapy. The method promotes improved gait symmetry, balance, increased speed and step length, ultimately leading to enhanced functional independence of patients. Further research is required to determine the clinical effectiveness of treadmill gait training with BFB in a larger sample of patients and with a longer follow-up.

Wednesday, November 22, 2023

Improving Deep Sleep May Prevent Dementia

 With your risk of dementia post stroke, what is your doctor's protocol to consistently get you to deep sleep?

Your chances of getting dementia.

1. A documented 33% dementia chance post-stroke from an Australian study?   May 2012.

2. Then this study came out and seems to have a range from 17-66%. December 2013.`    

3. A 20% chance in this research.   July 2013.

4. Dementia Risk Doubled in Patients Following Stroke September 2018 

The latest here:

Improving Deep Sleep May Prevent Dementia

Enhancing or maintaining deep sleep, also known as slow wave sleep, in older years could prevent dementia, according to a study published in JAMA Neurology.

“Slow-wave sleep, or deep sleep, supports the aging brain in many ways, and we know that sleep augments the clearance of metabolic waste from the brain, including

facilitating the clearance of proteins that aggregate in Alzheimer’s disease,” said Matthew Pase, PhD, Monash University, Victoria, Australia. “However, to date, we have been unsure of the role of slow-wave sleep in the development of dementia.”

For the study, Jayandra Himali, PhD, University of Texas Health Science Center, San Antonio, Texas, and colleagues looked at 346 participants with a mean age of 69 years who were enrolled in the Framingham Heart Study. The patients completed 2 overnight sleep studies within the time periods 1995 to 1998 and 2001 to 2003, with an average of 5 years between the 2 studies.

These participants were then carefully followed for dementia from the time of the second sleep study through 2018.

The researchers found that, on average, the amount of deep sleep declined between the 2 studies, indicating slow wave sleep loss with aging. Over 17 years of follow-up, there were 52 cases of dementia. Even after adjusting for age, sex, cohort, genetic factors, smoking status, sleeping medication use, antidepressant use, and anxiolytic use, each percentage decrease in deep sleep per year was associated with a 27% increase in the risk of dementia.

“We also examined whether genetic risk for Alzheimer’s disease or brain volumes suggestive of early neurodegeneration were associated with a reduction in slow-wave sleep,” said Dr. Pase. “We found that a genetic risk factor for Alzheimer’s disease, but not brain volume, was associated with accelerated declines in slow wave sleep.”

“Our findings suggest that slow wave sleep loss may be a modifiable dementia risk factor,” he concluded.

Reference: https://jamanetwork.com/journals/jamaneurology/article-abstract/2810957

SOURCE: Monash University

Wednesday, May 24, 2023

Memory Boosted With Daily Multivitamins

Is your doctor competent enough to see this and immediately prescribe a protocol on vitamins for you immediately post stroke? You do want your memory boosted and cognitive decline slowed? 

Do you prefer your  doctor  incompetence NOT KNOWING? OR NOT DOING?

Memory Boosted With Daily Multivitamins

Effects strongest for people with underlying cardiovascular disease

A photo of an open bottle of vitamins spilling out onto a counter.

Multivitamin supplementation slowed cognitive decline in older adults, the COSMOS-Webopens in a new tab or window study showed.

Compared with placebo, participants who took a daily multivitamin/multimineral supplement had significantly better immediate recall at 1 year (P=0.025) and across 4 years of follow-up on average (P=0.011), reported Adam Brickman, PhD, of Columbia University in New York City, and co-authors in the American Journal of Clinical Nutritionopens in a new tab or window.

Multivitamins improved memory performance above placebo by the equivalent of 3.1 years of age-related memory change, the researchers estimated. The effect was more pronounced in people with underlying cardiovascular disease.

The findings are consistent with data from COSMOS-Mind,opens in a new tab or window another COSMOS ancillary study that showed daily multivitamin use led to better cognition, episodic memory, and executive function. Effects in COSMOS-Mind also were more pronounced in people with cardiovascular disease history.

"There is evidence that people with cardiovascular disease may have lower micronutrient levels that multivitamins may correct, but we don't really know right now why the effect is stronger in this group," Brickman said in a statement.

"Supplementation of any kind shouldn't take the place of more holistic ways of getting the same micronutrients," he cautioned. "Though multivitamins are generally safe, people should always consult a physician before taking them."

COSMOS-Web was designed to examine the effects of dietary flavanol or multivitamin supplementation on hippocampus-mediated cognition in older adults after 1 year.

"There is converging work that the hippocampus is particularly susceptible to the effects of normal aging and our previous intervention studies with dietary supplementation showed a positive effect on the hippocampus, indexed both by neuroimaging and neuropsychological assessment," Brickman and colleagues wrote.

The COSMOS-Web cognitive battery included neuropsychological outcome measures designed to be sensitive to cognitive changes typically seen in older adults, they added.

COSMOS-Web was embedded in the parent COSMOSopens in a new tab or window trial, which tested cocoa flavanol extract versus placebo or a Centrum Silver daily multivitamin versus placebo in people 60 and older. (Flavanol data will be reported in a separate paper, the authors noted.) Randomization occurred between April 2016 and March 2018.

The COSMOS-Web primary outcome was performance after 1 year on the Modified Rey Auditory Verbal Learning (ModRey)opens in a new tab or window immediate recall test of 20 words. Secondary outcomes included change in ModRey immediate recall performance after 2 and 3 years, ModRey retention (ratio of delayed recall to immediate recall, which relates to entorhinal cortex function), and performance on tests of novel object recognition and executive function. Tests were administered through a web-based platform.

The intention-to-treat analysis included 3,562 participants randomized to multivitamin or placebo who completed at least one follow-up measurement at year 1, 2, or 3. Demographic characteristics and baseline performance measures were similar between groups.

Pill compliance was 94.4% at 6 months and 91.8% at 1 year. In a small subset, the researchers assessed blood samples and confirmed increases in folate, vitamin B12, and serum 25(OH)vitamin D with multivitamin supplementation versus placebo.

Compared with those on placebo, participants receiving multivitamin supplementation had significantly greater improvement in ModRey immediate recall memory between baseline and year 1. In the multivitamin group, performance improved from a mean of 7.10 words at baseline to 7.81 words at 1 year; in the placebo group, it rose from 7.21 words to 7.65 words.

The average improvement in memory compared with placebo appeared to be sustained over at least 3 years post-baseline. Secondary outcomes did not differ significantly between groups in any of the follow-up years.

In participants with a history of cardiovascular disease, the effect versus placebo on ModRey scores was higher at 1 year (mean difference of 1.24 words, P=0.009) than it was for people without underlying cardiovascular disease.

The data support growing evidence that nutrition may play a roleopens in a new tab or window in brain heath.

"The finding that a daily multivitamin improved memory in two separate cognition studies in the COSMOS randomized trial is remarkable, suggesting that multivitamin supplementation holds promise as a safe, accessible, and affordable approach to protecting cognitive health in older adults," said co-author JoAnn Manson, MD, of Brigham and Women's Hospital in Boston.

The results might not apply to all older adults, the researchers acknowledged. The sample consisted mostly of white, educated adults. People were required to have a computer and internet connectivity to participate in the study.

  • Judy George covers neurology and neuroscience news for MedPage Today, writing about brain aging, Alzheimer’s, dementia, MS, rare diseases, epilepsy, autism, headache, stroke, Parkinson’s, ALS, concussion, CTE, sleep, pain, and more. Follow

Disclosures

The study was supported by grants from Mars Edge and the National Institutes of Health. Multivitamins were supplied by Pfizer (now Haleon).

Researchers reported relationships with Pure Encapsulations, Pfizer, Council for Responsible Nutrition, BASF, NIH, and the American Society of Nutrition.

Primary Source

American Journal of Clinical Nutrition

Source Reference: opens in a new tab or windowYeung L-K, at al "Multivitamin supplementation improves memory in older adults: A randomized clinical trial" Am J Clin Nutr 2023; DOI: 10.1016/j.ajcnut.2023.05.011.

Tuesday, April 25, 2023

Simple memory test may identify people most likely to develop cognitive impairment

 With your already higher risk of dementia/MCI post stroke, is your doctor testing for this to create a baseline for you? And what EXACTLY is your doctor's protocol for preventing dementia? Doesn't have one! You don't have a functioning stroke doctor! Why are you seeing them if they are that incompetent?

Your risk of dementia, has your doctor told you of this?

1. A documented 33% dementia chance post-stroke from an Australian study?   May 2012.

2. Then this study came out and seems to have a range from 17-66%. December 2013.`    

3. A 20% chance in this research.   July 2013.

4. Dementia Risk Doubled in Patients Following Stroke September 2018

The latest here:

Simple memory test may identify people most likely to develop cognitive impairment

In people with no thinking and memory problems, a simple test may predict the risk of developing cognitive impairment years later, according to a study published in the April 19, 2023, online issue of Neurology®, the medical journal of the American Academy of Neurology.

There is increasing evidence that some people with no thinking and memory problems may actually have very subtle signs of early cognitive impairment. In our study, a sensitive and simple memory test predicted the risk of developing cognitive impairment in people who were otherwise considered to have normal cognition."

Ellen Grober, PhD, Study Author, Albert Einstein College of Medicine, Bronx, New York

The study involved 969 people with an average age of 69 with no thinking or memory problems at the start of the study. They were given a simple memory test and were followed for up to 10 years.

The test includes two phases. For the study phase, people are shown four cards, each with drawings of four items. They are asked to identify the item belonging to a particular category. For example, participants would name the item "grapes" after being asked to identify a "fruit." For the test phase, participants are first asked to recall the items. This measures their ability to retrieve information. Then, for items they did not remember, they are given category cues. This phase measures memory storage.

The participants were divided into five groups, or stages zero through four, based on their test scores, as part of the Stages of Objective Memory Impairment (SOMI) system. Stage zero represents no memory problems. Stages one and two reflect increasing difficulty with retrieving memories which can precede dementia by five to eight years. These participants continue to be able to remember items when given cues. In the third and fourth stages, people cannot remember all the items even after they are given cues. These stages precede dementia by one to three years.

A total of 47% of the participants were in stage zero, 35% in stage one, 13% in stage two and 5% in stages three and four combined.

Of the participants, 234 people developed cognitive impairment.

After adjusting for age, sex, education and a gene that affects a person's risk of Alzheimer's disease, APOE4, researchers found when compared to people who were at SOMI stage zero, people at stages one and two were twice as likely to develop cognitive impairment. People who were at stages three and four were three times as likely to develop cognitive impairment.

After adjusting for biomarkers of Alzheimer's disease including brain amyloid plaques and tau tangles, the SOMI system continued to predict an increased risk of cognitive impairment.

Researchers estimated that after 10 years about 72% of those in the third and fourth stages would have developed cognitive impairment, compared to about 57% of those in the second stage, 35% in the first stage and 21% of those in stage zero.

"Our results support the use of the SOMI system to identify people most likely to develop cognitive impairment," said Grober. "Detecting cognitive impairment at its earliest stages is beneficial to researchers investigating treatments. It also could benefit those people who are found to be at increased risk by consulting with their physician and implementing interventions to promote healthy brain aging."

A limitation of the study was that most participants were white and well educated. Grober said more research is needed in larger and more diverse populations.

The study was funded by the National Institutes of Health, Alzheimer's Association, Cure Alzheimer Fund and the Leonard and Sylvia Marx Foundation.

Source:
Journal reference:

Grober, E., et al. (2023). Association of Stages of Objective Memory Impairment With Incident Symptomatic Cognitive Impairment in Cognitively Normal Individuals. Neurology. doi.org/10.1212/WNL.0000000000207276.

Be the first to rate this article

Posted in: Medical Science News | Medical Research News | Medical Condition News

Tags: , , , , , , , , , , , , , , , , , , ,

Wednesday, April 12, 2023

Comparative efficacy of gait training for balance outcomes in patients with stroke: A systematic review and network meta-analysis

So ask your doctor for the EXACT PROTOCOL to accomplish this. No protocol! You need to call the president and ask when competent staff will be hired.

Comparative efficacy of gait training for balance outcomes in patients with stroke: A systematic review and network meta-analysis

Tianyi Lyu1†, Kang Yan1†, Jiaxuan Lyu1, Xirui Zhao1, Ruoshui Wang1, Chaoyang Zhang1, Meng Liu1, Chao Xiong2, Chengjiang Liu3 and Yulong Wei1*
  • 1School of Acupuncture-Moxibustion and Tuina, Beijing University of Chinese Medicine, Beijing, China
  • 2L3 & Maintenance Solutions, SUSE Software (Beijing) Co., Ltd., Beijing, China
  • 3Department of General Medicine, Affiliated Anqing First People’s Hospital of Anhui Medical University, HeFei, Anhui, China

Background: Growing evidence suggests that gait training can improve stroke patients’ balance outcomes. However, it remains unclear which type of gait training is more effective in improving certain types of balance outcomes in patients with stroke. Thus, this network meta-analysis (NMA) included six types of gait training (treadmill, body-weight-supported treadmill, virtual reality gait training, robotic-assisted gait training, overground walking training, and conventional gait training) and four types of balance outcomes (static steady-state balance, dynamic steady-state balance, proactive balance, and balance test batteries), aiming to compare the efficacy of different gait training on specific types of balance outcomes in stroke patients and determine the most effective gait training.

Method: We searched PubMed, Embase, Medline, Web of Science, and Cochrane Library databases from inception until 25 April 2022. Randomized controlled trials (RCTs) of gait training for the treatment of balance outcomes after stroke were included. RoB2 was used to assess the risk of bias in the included studies. Frequentist random-effects network meta-analysis (NMA) was used to evaluate the effect of gait training on four categories of balance outcomes.

Result: A total of 61 RCTs from 2,551 citations, encompassing 2,328 stroke patients, were included in this study. Pooled results showed that body-weight-support treadmill (SMD = 0.30, 95% CI [0.01, 0.58]) and treadmill (SMD = 0.25, 95% CI [0.00, 0.49]) could improve the dynamic steady-state balance. Virtual reality gait training (SMD = 0.41, 95% CI [0.10, 0.71]) and body-weight-supported treadmill (SMD = 0.41, 95% CI [0.02, 0.80]) demonstrated better effects in improving balance test batteries. However, none of included gait training showed a significant effect on static steady-state balance and proactive balance.

Conclusion: Gait training is an effective treatment for improving stroke patients’ dynamic steady-state balance and balance test batteries. However, gait training had no significant effect on static steady-state balance and proactive balance. To achieve maximum efficacy, clinicians should consider this evidence when recommending rehabilitation training to stroke patients. Considering body-weight-supported treadmill is not common for chronic stroke patients in clinical practice, the treadmill is recommended for those who want to improve dynamic steady-state balance, and virtual reality gait training is recommended for those who want to improve balance test batteries.

Limitation: Missing evidence in relation to some types of gait training is supposed to be taken into consideration. Moreover, we fail to assess reactive balance in this NMA since few included trials reported this outcome.

Systematic Review Registration: PROSPERO, identifier CRD42022349965.

Introduction

Recently, stroke is the leading cause of death in China and the second leading cause of death worldwide (1, 2). Despite the fact that stroke mortality, prevalence, and incidence have decreased in the past 20 years, its prevalence is increasing in young individuals (3). Thus, the significance of stroke rehabilitation has grown. Balance disorders, one of the most common symptoms after a stroke, can affect patients’ physiological and social functions (4, 5). Therefore, balance disorders place a heavy burden on both individuals and society.

Balance is one of the main functional goals of postural control and involves the coordination of movement strategies to stabilize the center of body mass during self-initiated and externally triggered stability perturbations (6). Balance disorders account for a series of gait-related disabilities, including problems with transferring, maintaining body posture, and locomotion (7, 8). Therefore, balance is an important component of gait to stabilize one’s body during mobility. Meanwhile, growing evidence suggests that gait training can improve balance outcomes (9, 10).

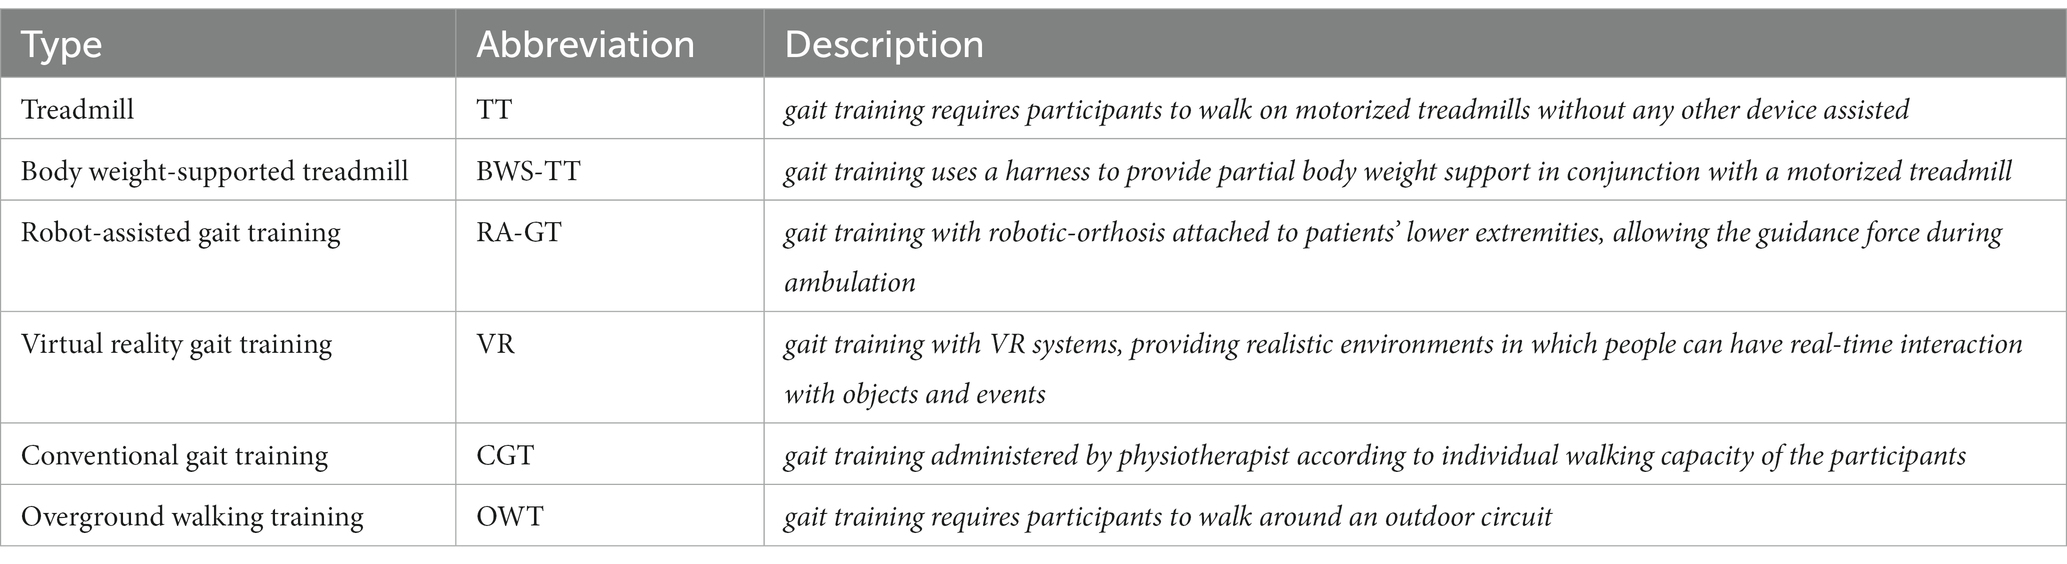
Gait training refers to specific types of physical therapies that help individuals strengthen and improve their walking capacity (11). Treadmill, body-weight-supported treadmill, robot-assisted gait training, virtual reality gait training, conventional gait training, and overground walking training are common types of gait training that have the potential to improve balance capacity (details in Table 1). Several studies have suggested that the aforementioned gait training could counteract the balance dysfunction caused by various diseases, such as stroke and Parkinson’s disease (9, 10). However, the effects of gait training on balance rehabilitation after stroke have been inconclusive. It remains unclear which type of gait training is the most effective. Canadian Guideline revealed that gait training (e.g., body-weight-supported treadmill) might improve dynamic balance in the subacute phase after stroke (12). A recent meta-analysis suggested that overground walking training and robotic-assisted gait training showed no significant effect on balance outcomes while treadmill showed a significant effect on balance outcomes (13). Another systematic review and meta-analysis reported that no significant balance gains were obtained from gait training (e.g., body-weight-supported treadmill and robot-assisted gait training) (14).

TABLE 1
www.frontiersin.org

Table 1. Characteristics of included gait training.

According to Shumway-Cook and Woollacott (15), balance performance can be divided into four types, including dynamic steady-state balance, static steady-state balance, proactive balance, and reactive balance. In addition, there are only small-sized correlations between different types of balance performance (16). With reference to these findings, balance outcome measures are further subdivided into five types, including static steady-state balance, dynamic steady-state balance, proactive balance, reactive balance, and balance test batteries (17). The first four types of balance outcome measures correspond, one by one, to the four types of balance performance, and the fifth type of balance outcome measure (balance test batteries) is added to assess the overall balance performance (18, 19). This classification has been used in several types of research to assess balance status and changes in response to exercise (20, 21). Thus, investigating the effect of gait training in specific type of balance outcomes might provide more comprehensive evidence in this field.

As mentioned earlier, evaluating the effects of gait training in post-stroke patients is of particular importance. However, selecting the optimal gait training to improve specific balance outcomes poses a challenge to clinicians. Because many gait training methods have not been directly compared in clinical trials, typical pairwise meta-analysis cannot be performed on them. Even when direct comparisons are available, the evidence is inadequate to make any conclusions. Therefore, we performed an NMA to compare the effects of different types of gait training on each type of balance outcome, thus identifying the optimal gait training for stroke survivors.

More at link.

Thursday, February 23, 2023

Sleep this way to add almost 5 years to your life

 What is your doctor's sleep protocol? Anything like this? No sleeping pills in the hospital? No wakeups at 7am for the vampire blood drawing club? I've gotten much better on this since retiring.

Will this be enough to recover from your lost 5 cognitive years from your stroke?

Sleep this way to add almost 5 years to your life

Want to live longer? Then prioritize sleep in your life: Following five good sleep habits added nearly five years to a man’s life expectancy and almost 2.5 years to a woman’s life, a new study found.

“If people have all these ideal sleep behaviors, they are more likely to live longer,” said study coauthor Dr. Frank Qian, a clinical fellow in medicine at Harvard Medical School and internal medicine resident physician at Beth Israel Deaconess Medical Center in Boston.

“If we can improve sleep overall, and identifying sleep disorders is especially important, we may be able to prevent some of this premature mortality,” Qian said in a statement.

What do you do? First, make sure you get a full seven to eight hours of sleep each night. That’s tough for many people: 1 in 3 Americans have a sleep deficit, according to the US Centers for Disease Control and Prevention.

But you have to do more than just lay in bed longer — you also need have to have an uninterrupted, restful sleep more often than not. That means you don’t wake up during the night or have trouble falling asleep more than two times a week. You also have to feel well rested at least five days a week when you wake up. And finally, you can’t be using sleep medications to achieve your slumber.

“We’re talking about not just quality and quantity of sleep, but regularity, getting the same good sleep night after night,” said sleep specialist Dr. Raj Dasgupta, an associate professor of clinical medicine at the University of Southern California’s Keck School of Medicine. He was not involved in the study.

“Recent studies have shown irregularity in sleep timing and duration have been linked to metabolic abnormalities and higher cardiovascular disease risk,” he said. “Encouraging maintenance of regular sleep schedules with consistent sleep durations may be an important part of lifestyle recommendations for the prevention of heart disease.”

A difference between men and women

The preliminary study, presented Thursday at an annual meeting of the American College of Cardiology, analyzed data from over 172,000 people who answered sleep questionnaires between 2013 and 2018 as part of the National Health Interview Survey. The annual survey is done by the CDC and the National Center for Health Statistics.

Each of the five healthy sleep habits — falling asleep easily, staying asleep, getting seven to eight hours of zzz’s, waking up rested and foregoing sleep meds — was assigned a number. People were scored on how many of the five habits they had.

About four years later, researchers compared those scores with National Death Index records to see if their sleep behaviors contributed to an early death from certain diseases or any cause.

The team then factored out other potential causes for a higher risk of dying, such as alcohol consumption, lower socioeconomic status and existing medical conditions.

“Compared to individuals who had zero to one favorable sleep factors, those who had all five were 30% less likely to die for any reason, 21% less likely to die from cardiovascular disease, 19% less likely to die from cancer, and 40% less likely to die of causes other than heart disease or cancer,” according to a statement on the study.

Men who followed all five of the healthy sleep habits had a life expectancy that was 4.7 years greater than people who had none or only one of the five elements of low-risk sleep, the study found.

The impact of healthy sleep habits was much lower for women: Those who followed all five sleep habits gained 2.4 years compared with those who did none or only one.

“That was an interesting part of the study for me, and I hope we can find that answer with more research,” Dasgupta said. One potential reason for that gender difference, he added, could be the difficulty of evaluating women for obstructive sleep apnea, a potentially deadly condition in which breathing stops every few minutes. The more severe the apnea, the greater the risk of coronary artery disease, heart attacks, heart failure and strokes.

“Women with obstructive sleep apnea often get underdiagnosed or misdiagnosed because they may not present with the classic symptoms that we see when we’re evaluating men,” Dasgupta said. “Maybe we need to ask different questions or look at different parameters, or is there something we’re missing here?”

Good sleep hygiene

Would your score be less than five? Don’t fret — the good news is that you can easily train your brain to better sleep by following what is called good “sleep hygiene.” It’s important to go to bed at the same time on most nights and get up at the same time most mornings — even on weekends and holidays.

Make sure your sleeping environment is optimal — cooler and darker is better — and block noise or try a sound machine. Avoid booze before bed — it may seem like you’re falling asleep more easily, but when your liver finishes metabolizing the alcohol at 3 a.m., your body will wake up, experts say.

Set up a sleep routine, with no blue lights or distractions at least an hour before bedtime. Try meditation, yoga, tai chi, warm baths — anything that relaxes you is great.

Parents and caregivers can learn these habits and teach them to their children, thus providing them with a better shot at a longer life, Qian said.

“Even from a young age, if people can develop these good sleep habits of getting enough sleep, making sure they are sleeping without too many distractions and have good sleep hygiene overall, it can greatly benefit their overall long-term health,” he said.

“Just like we like to say, ‘it’s never too late to exercise or stop smoking,’ it’s also never too early. And we should be talking about and assessing sleep more often.”

Friday, December 23, 2022

The Surprising Link Between Bedtime and Dementia

 Hopefully your doctor has a specific sleep protocol for you to follow.

The Surprising Link Between Bedtime and Dementia

The Surprising Link Between Bedtime and Dementia

Rawpixel/Getty Images
  • Alzheimer’s disease, a common form of dementia, is one of the top tenTrusted Source leading causes of death in the US.
  • New research indicates that time spent in bed and bedtime may impact dementia risk.
  • Those aged 60-74 were most affected.
  • Previous research also highlighted the role of sleep quality in memory and dementia.

Sleep can influence physical and mental health and is linked to conditions from heart disease and stroke to depression and obesity.

And a new studyTrusted Source published September 21 in the Journal of the American Geriatrics Society has provided further insights into sleep’s role in dementia.

Researchers in China, Sweden, and the UK looked at sleep data of 1,982 Chinese individuals with an average age of 70 — none of whom presented with symptoms of dementia at the start of the study.

An average of 3.7 years later, 97 participants (5%) had been diagnosed with dementia according to the Diagnostic and Statistical Manual of Mental Disorders, Fourth Edition (DSM-IV) criteria.

Those primarily impacted were aged between 60 and 74. Men were also at higher risk, which contradicts what many other dementia researchers have previously found.

“In most studies, women are known to have a two-fold greater risk of dementia than men. It is unusual that this study found the opposite,” shared Dr. Alex Dimitriu, double board-certified in psychiatry and sleep medicine and founder of Menlo Park Psychiatry & Sleep Medicine and BrainfoodMD.

The study found that longer time spent in bed (TIB) was associated with significantly increased dementia risk. Those in bed for more than 8 hours were far more likely to show a cognitive decline during a Mini Mental State Examination (MMSE) — a test used to measure cognitive impairment.

So why might older people need to spend more time in bed?

“As we get older, we see a fragmentation of the sleep states,” Dr. Michael Breus, a sleep specialist and clinical psychologist, told Healthline. This means “that we don’t seem to get the same type of physically restoring sleep (stages 3/4) as we did when we were younger.”

As such, “it’s possible that people with poorer quality sleep may require more sleep time to compensate,” added Dimitriu.

Other factors can play a role, too, explained Dr. Carl W. Bazil, PhD, Caitlin Tynan Doyle professor of neurology at Columbia University College of Physicians and Surgeons.

Depression (for which older adults are at greater riskTrusted Source) can make sleeping difficult, he explained. “But there are also many other medical conditions (such as heart disease or diabetes) and the medications taken for them that can increase tiredness and sleep requirements.”

The time individuals went to bed was also highlighted by researchers as a critical contributing factor. Early-mid evening hours were deemed riskiest. The research paper stated that “every 1 hour advance in bedtime [before 10 pm] was associated with a 25% increased risk of dementia.”

The study authors hypothesized that earlier bedtimes could be driven by disrupted circadian rhythm.

“Parts of the brain responsible for managing sleep start to change as we age. This impacts our circadian rhythm cycles,” said Dr. David Rabin, PhD, a neuroscientist, board-certified psychiatrist, and co-founder of Apollo Neuro, a wearable device for stress relief.

Age-related factors, such as having to use the bathroom more frequently during the night, also “impact us getting good quality and deep sleep,” continued Rabin. Accumulative sleep deprivation “results in a change in brain structures that regulate circadian cycles.”

Other influences might also be at play, stated Dimitriu.

“It is possible that people with early stages of dementia experience earlier brain fatigue in the day, leading them to want to sleep earlier,” he said. “‘Sundowning’ is a well-known effect in older people prone to dementia, where they can become confused and disoriented in the evenings.”

Study limitations to consider

One of the main drawbacks to the research is that TIB doesn’t necessarily reflect the time spent asleep. Sleep duration has been noted by scientists as a crucial factor in cognitive health and dementia risk.

Breus stated that longer TIB could indicate an underlying sleep-related issue, such as insomnia, which “could be affecting this situation and making it worse.”

A recent Canadian study also highlighted that those with insomnia were at higher risk of memory loss.

Furthermore, TIB doesn’t consider the quality of a person’s sleep — also regarded as important in cognition and dementia. For instance, not getting enough deep sleep can greatly impact memory (more on this later).

There’s one final consideration to bear in mind.

“This study, as well as many others like it, are association studies and, as such, do not show cause and effect,” explained Bazil.

“So it is never clear whether the observed association (in this case, short or long times in bed or sleep onset time) actually causes dementia, or is indirectly related to it,” he added.

A key signal of dementia is memory loss. However, in all stages of life, “we know that quality sleep is required for many, if not all kinds of memory,” Bazil explained.

So what happens when you’re in a state of slumber? With regard to memory, two main actions occur.

The first is the processing and ‘storing’ of memories.

“Short-term memory is initially stored in the hippocampus when it comes into the brain, which is the area where information is stored for short-term recollection and use,” explained Rabin.

“When we sleep, information from the hippocampus gets passed into the higher cortical structures of the brain that allow it to become long-term memory and integrate with past memories,” he continued.

Rabin revealed this process is called memory reconsolidation — and is particularly impacted by poor quality REM sleep or shorter sleep duration.

Second, sleep is when our brains clear out harmful toxins that, over time, can impact memory.

“When the brain is active during the day, it produces a lot of what we call ‘reactive oxygen species’ or inflammatory waste products,” stated Rabin. “When the brain is asleep and able to recover, especially in deep and REM sleep states, [it] detoxifies and removes inflammatory waste products.”

A build-up of toxins ultimately puts extra stress on the brain and prevents it from achieving memory reconsolidation.

“In summary, sleep quality, as much as sleep quantity, may be important,” said Dimitriu.

This study monitored dementia onset in older individuals — the time of life when its symptoms are most likely to arise.

“Dementias, like Alzheimer’s Disease, often present with symptoms [among people] in their 60s, although early onset in the 40s or 50s may occur,” Dr. Sandra Petersen, senior vice president of health and wellness at Pegasus Senior Living, shared with Healthline.

She continued: “Dementia is an ‘umbrella’ term for a group of diseases, of which Alzheimer’s is the most prevalent, in which progressive changes take place in the brain.”

Petersen explained that common signs and symptoms of dementia are:

  • Persistent and pervasive difficulty with memory, cognition, and ability to perform everyday tasks
  • Loss of focus
  • Inability to pay attention
  • Loss of language skills
  • A decrease in visual perception
  • A loss of problem-solving skills
  • Impaired reasoning and judgment

Risk factors in dementia

While this new study (among others) reveals sleep as a risk factor in dementia, it’s not the only actor involved.

“Researchers have considered a number of possible causes of dementia,” said Petersen. “We don’t know for sure, but it is likely a combination of factors that contributes to [its] development and progression.”

She revealed scientists hypothesize dementia may arise from:

  • Inflammation — resulting from poor sleep, poor diet, lack of exercise, and other unhealthy habits
  • The occurrence of abnormal ‘tau’ proteins in the brain
  • Genetics
  • Untreated and prolonged depression
  • The brain’s inability to use insulin correctly

Wednesday, December 21, 2022

Multimodal ambulatory monitoring of daily activity and health-related symptoms in community-dwelling survivors of stroke: Feasibility, acceptability, and validity.

So where did you put the protocol for this so all 10 million yearly stroke survivors

  now and into the future can find it and bring it to their doctor's attention?

 Multimodal ambulatory monitoring of daily activity and health-related symptoms in community-dwelling survivors of stroke: Feasibility, acceptability, and validity.

Archives of Physical Medicine and Rehabilitation , Volume 103(10) , Pgs. 1992-2000.

NARIC Accession Number: J90202.  What's this?
ISSN: 0003-9993.
Author(s): Lau, Stephen C. L.; Connor, Lisa T.; King, Allison A.; Baum, Carolyn M. .
Publication Year: 2022.
Number of Pages: 9.
Abstract: Study examined the feasibility, acceptability, and validity of multimodal ambulatory monitoring, which combines accelerometry with ecological momentary assessment (EMA), to assess daily activity and health-related symptoms among survivors of stroke. Over a 7-day period, 40 stroke survivors completed 8 daily EMA surveys about daily activity and symptoms (mood, cognitive complaints, fatigue, pain) while wearing an accelerometer. Participants also completed retrospective assessments and an acceptability questionnaire. Feasibility was determined using attrition rate and compliance. Acceptability was reported using the acceptability questionnaire. Convergent and discriminant validity were determined by the correlations between ambulatory monitoring and retrospective self-reports. Criterion validity was determined by the concordance between accelerometer-measured and EMA-reported daily activity. All participants completed the study (attrition rate=0 percent). EMA and accelerometer compliance were 93.6 percent and 99.7 percent, respectively. Participants rated their experience with multimodal ambulatory monitoring positively. They were highly satisfied (mean, 4.8 out of 5) and confident (mean, 4.7/5) in using ambulatory monitoring and preferred it over traditional retrospective assessments (mean, 4.7/5). Multimodal ambulatory monitoring estimates correlated with retrospective self-reports of the same and opposing constructs in the predicted directions. More intense accelerometer-measured physical activity was observed when participants reported doing more physically demanding activities and vice versa. Findings support the feasibility, acceptability, and validity of multimodal ambulatory monitoring in survivors of mild stroke. Multi-modal ambulatory monitoring has potential to provide a more complete understanding of survivors’ daily activity in the context of everyday life.
Descriptor Terms: CLIENT SATISFACTION, COMPLIANCE, DAILY LIVING, DEVICES, ELECTRONICS, EVALUATION TECHNIQUES, FEASIBILITY STUDIES, MEASUREMENTS, OUTCOMES, PERFORMANCE STANDARDS, REHABILITATION SERVICES, STROKE, TELECOMMUNICATIONS.


Can this document be ordered through NARIC's document delivery service*?: Y.

Citation: Lau, Stephen C. L., Connor, Lisa T., King, Allison A., Baum, Carolyn M. . (2022). Multimodal ambulatory monitoring of daily activity and health-related symptoms in community-dwelling survivors of stroke: Feasibility, acceptability, and validity.  Archives of Physical Medicine and Rehabilitation , 103(10), Pgs. 1992-2000. Retrieved 12/21/2022, from REHABDATA database.

Tuesday, December 20, 2022

My stroke was a lifequake, but music is helping me recover

WHAT EXACT PROTOCOL DOES YOUR DOCTOR HAVE LIKE THIS TO GET YOUR ARM/HAND RECOVERED?

YOUR DOCTOR'S RESPONSIBILITY!

My stroke was a lifequake, but music is helping me recover

Andrew Stopps
Andrew Stopps says his clarinet played a vital role in his stroke recovery.
Supplied
Andrew Stopps says his clarinet played a vital role in his stroke recovery.

Wellington music teacher Andrew Stopps is sharing his story in response to a series of articles about orchestra conductor Hamish McKeich’s stroke and recovery.

OPINION: One year ago, in November 2021, I had a severe stroke. This is the story of how I used music to increase my recovery and get myself back.

It is a very gentle thing when a stroke happens. For me, it was gradually increasing heaviness on the right side of my body and increasing difficulty making myself understood. There was no pain, no big flash and no fear, just confusion as to what was happening to me and overwhelming tiredness.

I later came to call it “the gentle assassin” which, in one stroke, took away the old Andrew and left me to rebuild Andrew 2.0.

I learned almost immediately that part of my brain had experienced a factory reset to default settings and my job now was to apply myself to teach it all over again.

While I was recovering in the hospital, in those early days post-stroke, my dear friend and fellow music educator, Vicky Thorpe, reminded me to use my clarinet as therapy.

That was a big ask, as at that time I had no movement at all in my right arm and a weak right lower half of my face.

There was no way then I could even hold a feather, let alone a clarinet and all the fine motor skills that come with actually playing it.

Having a stroke is a lifequake. Still, just four days after the stroke, I had my clarinet brought into the hospital and my rehab team helped me position my lifeless hand over the keys.

The hope was that it would trigger muscle memory and start my arm moving again, or even just one finger. It did not. At least not yet.

Having a stroke is a lifequake. It can be overwhelming, especially as there are so many parts of you that need rebuilding. Emotionally, you are without filters.

The Conductor
Iain McGregor/Stuff
Hamish McKeich was in the prime of his career when he suddenly collapsed and lost feeling in the right half of his body.

You express happiness and joy on your face. Beauty in music and art becomes tears in your eyes. Frustration and anger at your broken body become a good old foot-stamping tantrum. Your senses would overload very easily.

In the early days, I experienced all these and had to build new filters, but this time only the ones I wanted. I love the fact that if I am happy, joy breaks out on my face. I love that music now brings me to tears. I also learned that negativity impairs healing and learning, so I had to develop greater empathy and patience with myself.

Routine was important, and years of practice were a huge part of my recovery. I did my rehab every day and quickly started to see improvement.

I knew that even though my arm was limp, if I visualised it moving I would still build neurons and connections in my brain. The brain can’t distinguish actual movement from mental imagery, and eventually I was able to lift it a little.

Day by day, week by week, I kept visualising and mentally doing movements to music, like I was conducting, and my arm kept improving.

Improvement from brain injury is not like when you’re practising. You don’t see an immediate gain. Sometimes you can go days with nothing and then suddenly the movement happens, and just as suddenly as it comes, it goes again and you feel like you’re back at square one.

Despite the challenges, Andrew Stopps says he has much to be thankful for.
Supplied
Despite the challenges, Andrew Stopps says he has much to be thankful for.

You have to keep practising though and be very patient and kind to yourself. Every time it moves and does what you want, it does it better. If you can move it, you can improve it.

So with arm movement came wrist and hand. I would take clarinet music and mentally practice it with the actual piece playing. It was at this time I started using a mirror box and my piano keyboard. I would set the box in the middle of the keys, place my right hand inside and play the keyboard with my left, all while looking at the mirror.

Again, the brain cannot tell the difference between what my eyes were seeing and what was actually happening. My brain believed my right hand was playing the keyboard. Slowly my fingers started moving, from the little finger back to the thumb.

Slowly they moved independently. I could start using my hand again. The practice is ongoing. Mental imagery to music. Moving to music. Singing improved my speech.

Today, one year on and on the eve of my ‘stroke-versary’, I can hold my clarinet again and place my fingers on the keys. There’s still more practice to do. Finger strength and speed are still a work in progress, as is rotating my thumb down so it fits under the clarinet thumb rest.

My stroke specialist said, way back while I was in the hospital, that I was lucky I am a musician. Our brains are wired a little differently, which makes progress and improvement better than if we weren’t.

It’s so easy to descend into despair and let that voice in your head tell you all manner of terrible things: “You’re useless,” “No one will love you now,” “You’re broken,” “You might as well be dead.”


Cycling back from a stroke
MARTIN DE RUYTER/STUFF
Kathryn Lacy's e-bike is another part of her journey back from a life-changing stroke in 2018.

Well, I have learned this year that you can actually shout back at that internal bully. And I did. And it’s actually a coward. Like all bullies and abusers, it stopped and is gradually fading away.

The internal voice, the saboteur, as it’s sometimes called, is something we all have to a lesser or greater degree. It stops us from reaching our full potential and taking risks. It thinks it’s protecting us, but it’s actually harming us.

It’s one thing to say to yourself “don’t cross that freeway because you’ll probably be hit by a car” and “don’t bother going for a walk because you are fat anyway and everyone will stare at you”. One is sage advice and the other is plain abusive.

That internal abuser was very loud in the early days of recovery. I would grow frustrated with myself because I couldn’t do simple tasks. One of my rehab therapists noticed this and said anger and frustration interfere with healing. Be kind to yourself. That changed everything.

When I became frustrated, I reminded myself I’d been through a factory reset and I had to learn these skills again. I was more patient with myself and when the “abuser” turned up, I would shout back and shut it up.

I am thankful for being alive, I am thankful I can still read, write and talk and have all my cognitive functions, I am thankful that my emotional filters went and I was able to rebuild new ones, that I like. I am thankful I have full movement and am still recovering fine motor skills.

Finally, I am thankful this awful thing that is a stroke opened me up to all the amazing survivors and carers I have met and sent me off in a new direction on my life journey. It was a lifequake all right.

Another reason everyone should learn music, wouldn’t you say?