Changing stroke rehab and research worldwide now.Time is Brain! trillions and trillions of neurons that DIE each day because there are NO effective hyperacute therapies besides tPA(only 12% effective). I have 523 posts on hyperacute therapy, enough for researchers to spend decades proving them out. These are my personal ideas and blog on stroke rehabilitation and stroke research. Do not attempt any of these without checking with your medical provider. Unless you join me in agitating, when you need these therapies they won't be there.

What this blog is for:

My blog is not to help survivors recover, it is to have the 10 million yearly stroke survivors light fires underneath their doctors, stroke hospitals and stroke researchers to get stroke solved. 100% recovery. The stroke medical world is completely failing at that goal, they don't even have it as a goal. Shortly after getting out of the hospital and getting NO information on the process or protocols of stroke rehabilitation and recovery I started searching on the internet and found that no other survivor received useful information. This is an attempt to cover all stroke rehabilitation information that should be readily available to survivors so they can talk with informed knowledge to their medical staff. It lays out what needs to be done to get stroke survivors closer to 100% recovery. It's quite disgusting that this information is not available from every stroke association and doctors group.

Showing posts with label Bruce C.V. Campbell. Show all posts

Friday, December 17, 2021

Advances in Stroke: 2021 year in review of the Interventional Realm with Bruce Campbell

Reading the first page gives me no confidence that anything in 2021 was directed to solving 100% recovery. It all seems to be getting reperfusion done as fast as possible. Survivors don't give a fuck about reperfusion, that is just the first step to 100% recovery.

Reperfusion was a success, but the patient is still disabled. Not my definition of success or any stroke survivors definition.

You're not addressing survivor needs at all.

And yes I know Bruce C.V. Campbell is a rock star in the stroke world.

 Advances in Stroke: 2021 year in review of the Interventional Realm with Bruce Campbell

Originally publishedhttps://doi.org/10.1161/STROKEAHA.121.037039Stroke. 2021;0:STROKEAHA.121.037039
First page image
 

Saturday, July 11, 2020

Stroke from the Lancet

More tyranny of low expectations; 'management' NOT CURE OR 100% RECOVERY. And ignoring the really fast ways to diagnose stroke, doing this keeps neurologists employed. And yes, I know I'm criticizing a leader in stroke; but if leaders aren't leading they need to be deposed. 


Just maybe you want extremely fast diagnosis.

Hats off to Helmet of Hope - stroke diagnosis in 30 seconds   February 2017


Microwave Imaging for Brain Stroke Detection and Monitoring using High Performance Computing in 94 seconds March 2017


New Device Quickly Assesses Brain Bleeding in Head Injuries - 5-10 minutes April 2017

The latest here:

Stroke from the Lancet


Summary

Stroke is a major cause of death and disability globally. Diagnosis depends on clinical features and brain imaging to differentiate between ischaemic stroke and intracerebral haemorrhage. Non-contrast CT can exclude haemorrhage, but the addition of CT perfusion imaging and angiography allows a positive diagnosis of ischaemic stroke versus mimics and can identify a large vessel occlusion target for endovascular thrombectomy. Management of ischaemic stroke has greatly advanced(Really? I think it hasn't improved enough. No cures, no recovery.), with rapid reperfusion by use of intravenous thrombolysis and endovascular thrombectomy shown to reduce disability(NOT GOOD ENOUGH!). These therapies can now be applied in selected patients who present late to medical care if there is imaging evidence of salvageable brain tissue. Both haemostatic agents and surgical interventions are investigational for intracerebral haemorrhage. Prevention of recurrent stroke requires an understanding of the mechanism of stroke to target interventions, such as carotid endarterectomy, anticoagulation for atrial fibrillation, and patent foramen ovale closure. However, interventions such as lowering blood pressure, smoking cessation, and lifestyle optimisation are common to all stroke subtypes.


To read this article in full you will need to make a payment

Thursday, February 27, 2020

Increasing Tenecteplase Dose Does Not Improve Reperfusion in Ischaemic Stroke

But you had the wrong endpoint. Survivors care nothing about reperfusion, they want 100% recovery. WHEN THE HELL will you design research correctly to deliver that?  This is why we need survivors in charge, they will not take their eyes off the only goal in stroke, 100% recovery.

Increasing Tenecteplase Dose Does Not Improve Reperfusion in Ischaemic Stroke

By Alex Morrisson

LOS ANGELES -- February 24, 2020 -- Increasing the dose of tenecteplase prior to endovascular thrombectomy does not improve reperfusion or clinical outcomes in patients with stroke, according to a study presented here at the 2020 International Stroke Conference (ISC).

In the EXTEND 1A TNK Part 2 study, Bruce Campbell, PhD, Royal Melbourne Hospital, and the University of Melbourne, Melbourne, Australia, and colleagues enrolled 300 patients who were diagnosed with ischaemic large vessel strokes and randomised half to receive tenecteplase 0.25 mg/kg and the other half to tenecteplase 0.40 mg/kg.

Only 29 patients in each group achieved the primary endpoint, which of a >50% improvement in reperfusion of blocked brain blood vessels (P = .89).

“The findings suggest that the 0.40 mg/kg dose of tenecteplase does not confer an advantage over the 0.25 mg/kg dose in patients with large vessel occlusion ischaemic stroke in whom endovascular thrombectomy is planned,” said Dr. Campbell.

The EXTEND-IA TNK Part 2 trial was an investigator-initiated, multicentre, randomised, open-label blinded trial in patients with ischaemic stroke due to large vessel occlusion of the intracranial internal carotid, middle cerebral, or basilar artery who were eligible for intravenous thrombolysis and endovascular thrombectomy within 4.5 hours of stroke onset.

Secondary outcomes, including modified Rankin Scale score at 90 days and early neurological recovery, did not differ significantly between groups. The adjusted odds ratio in ordinal analysis of the modified Rankin Scale score at 90 days was 0.96. Symptomatic intracranial haemorrhage occurred in 7 patients (4.7%) in the 0.40 mg/kg group, 4 of which were associated with wire perforation during the endovascular procedure, and 2 patients (1.3%) in the 0.25 mg/kg group (P = .12). There were 26 deaths in the 0.40 mg/kg group and 22 in the 0.25 mg/kg group (P = .35).

“That the optimal tenecteplase dose for patients with ischaemic stroke appears to be 0.25 mg/kg,” said Dr. Campbell.

ISC is sponsored by the American Heart Association and the American Stroke Association.

[Presentation title: Abstract LB1: Determining the Optimal Dose of Tenecteplase Before Endovascular Thrombectomy (EXTEND-IA TNK Part 2): a Multicenter, Randomized, Controlled Trial. Abstract LB1]

Friday, May 31, 2019

Alteplase effective up to 9 hours after ischemic stroke

Then your definition of effective is an appallingly low bar. 100% recovery is my definition. WHEN THE HELL WILL YOU EVEN TRY TO GET THERE?

You might want to talk to stroke survivors sometime and compare what they want vs. what you are attempting to do. 

Alteplase effective up to 9 hours after ischemic stroke

Bruce C.V. Campbell
Bruce C.V. Campbell
In a meta-analysis presented at the European Stroke Organization Conference, alteplase was more effective than placebo for treatment of acute ischemic stroke between 4.5 and 9 hours after onset.
Guidelines recommend the use of a tissue plasminogen activator such as alteplase within 4.5 hours of acute ischemic stroke onset, but the researchers analyzed whether perfusion imaging could identify whether patients could benefit from alteplase after 4.5 hours or upon waking up with stroke symptoms.
Bruce C.V. Campbell, PhD, professor of medicine at Melbourne Brain Centre and Royal Melbourne Hospital, University of Melbourne, Australia, and colleagues conducted a systematic review and meta-analysis of 414 patients from three trials who were assigned alteplase (mean age, 73 years; 56% men) or placebo (mean age, 72 years; 58% men) after waking up with acute ischemic stroke symptoms or presenting with them between 4.5 and 9 hours after onset and were imaged with CT perfusion or perfusion-diffusion MRI. The results were simultaneously published in The Lancet.
The primary outcome was excellent functional outcome, defined as a modified Rankin Scale (mRS) score of 0 or 1, at 3 months.
The primary outcome was achieved in 36% of patients in the alteplase group and 29% of the placebo group (adjusted OR = 1.86; 95% CI, 1.15-2.99), according to the researchers.
Symptomatic intracranial hemorrhage occurred in 5% of the alteplase group vs. less than 1% of the placebo group (aOR = 9.7; 95% CI, 1.23-76.55).
“However, this did not negate the benefit of alteplase in ordinal analysis of the mRS, which accounts for transitions across the disability spectrum,” Campbell and colleagues wrote in The Lancet.
There was no significant difference between the groups in mortality (alteplase, 14%; placebo, 9%; aOR = 1.55; 95% CI, 0.81-2.96).
“This pooled analysis provides strong evidence in support of thrombolysis for patients with favorable perfusion imaging 4.5 to 9 hours after stroke, including patients with wake-up stroke,” Campbell and colleagues wrote.
In a related editorial in The Lancet, Shelagh B. Coutts, MD, MSc, and Bijoy K. Menon, MBBS, MD, MSc, both associate professors of medicine at the University of Calgary, wrote, “These findings should not prevent referral of a patient for endovascular clot retrieval, but might allow the use of thrombolysis as a bridge therapy during transport or a stand-alone treatment in settings where endovascular clot retrieval is not available.” – by Erik Swain

In a meta-analysis presented at the European Stroke Organization Conference, alteplase was more effective than placebo for treatment of acute ischemic stroke between 4.5 and 9 hours after onset.
Source: Adobe Stock
References:
Campbell BCV, et al. Official Welcome and Large Clinical Trials. Presented at: European Stroke Organization; May 22-24, 2019; Milan.
Campbell BCV, et al. Lancet. 2019;doi:10.1016/S0140-6736(19)31053-0.
Coutts SB, et al. Lancet. 2019;doi:10.1016/S0140-6736(19)31095-5.
Disclosures: Campbell reports no relevant financial disclosures. Please see the study for all other authors’ relevant financial disclosures.

Tuesday, May 7, 2019

Risk of Acute Kidney Injury with Consecutive, Multidose Use of Iodinated Contrast in Patients with Acute Ischemic Stroke

  Does your doctor and stroke hospital have a protocol to prevent this problem from happening? Or are they irresponsible and just hoping this won't occur?

Risk of Acute Kidney Injury with Consecutive, Multidose Use of Iodinated Contrast in Patients with Acute Ischemic Stroke

Z.Y. Jia, S.X. Wang, L.B. Zhao, Y.Z. Cao, H.B. Shi and S. Liu

    Abstract

    SUMMARY: Currently, CTA is the imaging technique most frequently used to evaluate acute ischemic stroke, and patients with intracranial large-vessel occlusion usually undergo endovascular treatment. This single-center, prospective, cohort study showed that consecutive, multidose use of contrast during CTA and DSA does not increase the incidence of acute kidney injury in patients with acute ischemic stroke, though acute kidney injury tended to have a higher incidence in the contrast multiexposure group (P = .172).

    CTA and CTP are the most frequently used noninvasive vascular imaging techniques to evaluate acute ischemic stroke (AIS).1,2 Analyses from a number of observational studies suggest that the risk of contrast-induced acute kidney injury (AKI) secondary to CTA/CTP imaging is relatively low in patients with AIS, particularly those with no history of renal impairment.1⇓–3
    Apart from CTA/CTP, most patients with AIS, within the time window of recanalization, undergo intra-arterial thrombectomy, which is associated with exposure to additional iodinated contrast medium during DSA.4⇓⇓⇓–8 Because the potential risk from iodinated contrast exposure is proportional to the dose of contrast medium administered, multiple, consecutive doses of contrast medium could imply a greater risk for AKI.9,10 Although several studies have cited data regarding the safety of the consecutive use of contrast medium in patients with AIS for CTA/CTP and DSA, the sample sizes have been small, most of the studies were retrospective, and the definition of AKI differed among the studies.11⇓⇓–14 Hence, AKI induced by consecutive multidosing of contrast medium is still a perceived risk. We therefore performed this prospective study to determine whether consecutive, multidose use of contrast increases the incidence of AKI compared with its single use in patients with AIS.

    Materials and Methods

    Study Design and Patient Enrollment

    This study is a prospective, registered, cohort study performed from September 2016 to September 2017 at a single medical center with the approval of the institutional review board of the center. Informed consent was obtained from all patients or their legal representatives.
    Patient inclusion criteria were the following: 1) 18 years of age or older; 2) suspicion of AIS; 3) seen within 6 hours of developing anterior circulation symptoms or within 24 hours of posterior circulation symptoms; 4) no intracranial hemorrhage; and 5) underwent CTA. Exclusion criteria were lack of a baseline creatinine level or lack of a follow-up creatinine level 48 hours after CTA.

    Imaging

    All imaging was performed on a 64-section CT scanner (Optima CT660, GE Healthcare, Milwaukee, Wisconsin). For CTA, isotonic contrast material (1.5 mL/kg) (iodixanol, 320 mg I/mL, Visipaque 320; GE Healthcare, Piscataway, New Jersey) was injected at a rate of 4 mL/s, followed by a 20-mL saline bolus chaser using a dual-head injector. The upper limit volume of the contrast material was 100 mL.

    Endovascular Treatment

    Intra-arterial treatment consisted of thrombolysis, mechanical thrombectomy with a stent retriever or aspiration catheter, balloon angioplasty and stent insertion, or carotid artery stent placement. The volume of the contrast (iodixanol, 320 mg I/mL, Visipaque 320) used during the procedure was recorded.

    Definition of AKI

    AKI was defined as a >25% increase in the serum creatinine value over the baseline value 48 hours after CTA. The incidence of AKI was compared between patients given iodinated contrast medium for CTA (single exposure, CTA group) versus those given contrast medium for CTA and DSA (consecutive multiexposure, DSA group).

    Statistical Analysis

    The Student t test or the Mann-Whitney U test (for unevenly distributed categoric variables) was used to identify the difference in continuous variables. The difference in each of the categoric variables between the 2 groups was tested using a χ2 or Fisher exact test. Two-tailed P < .05 was considered statistically significant.

    Results

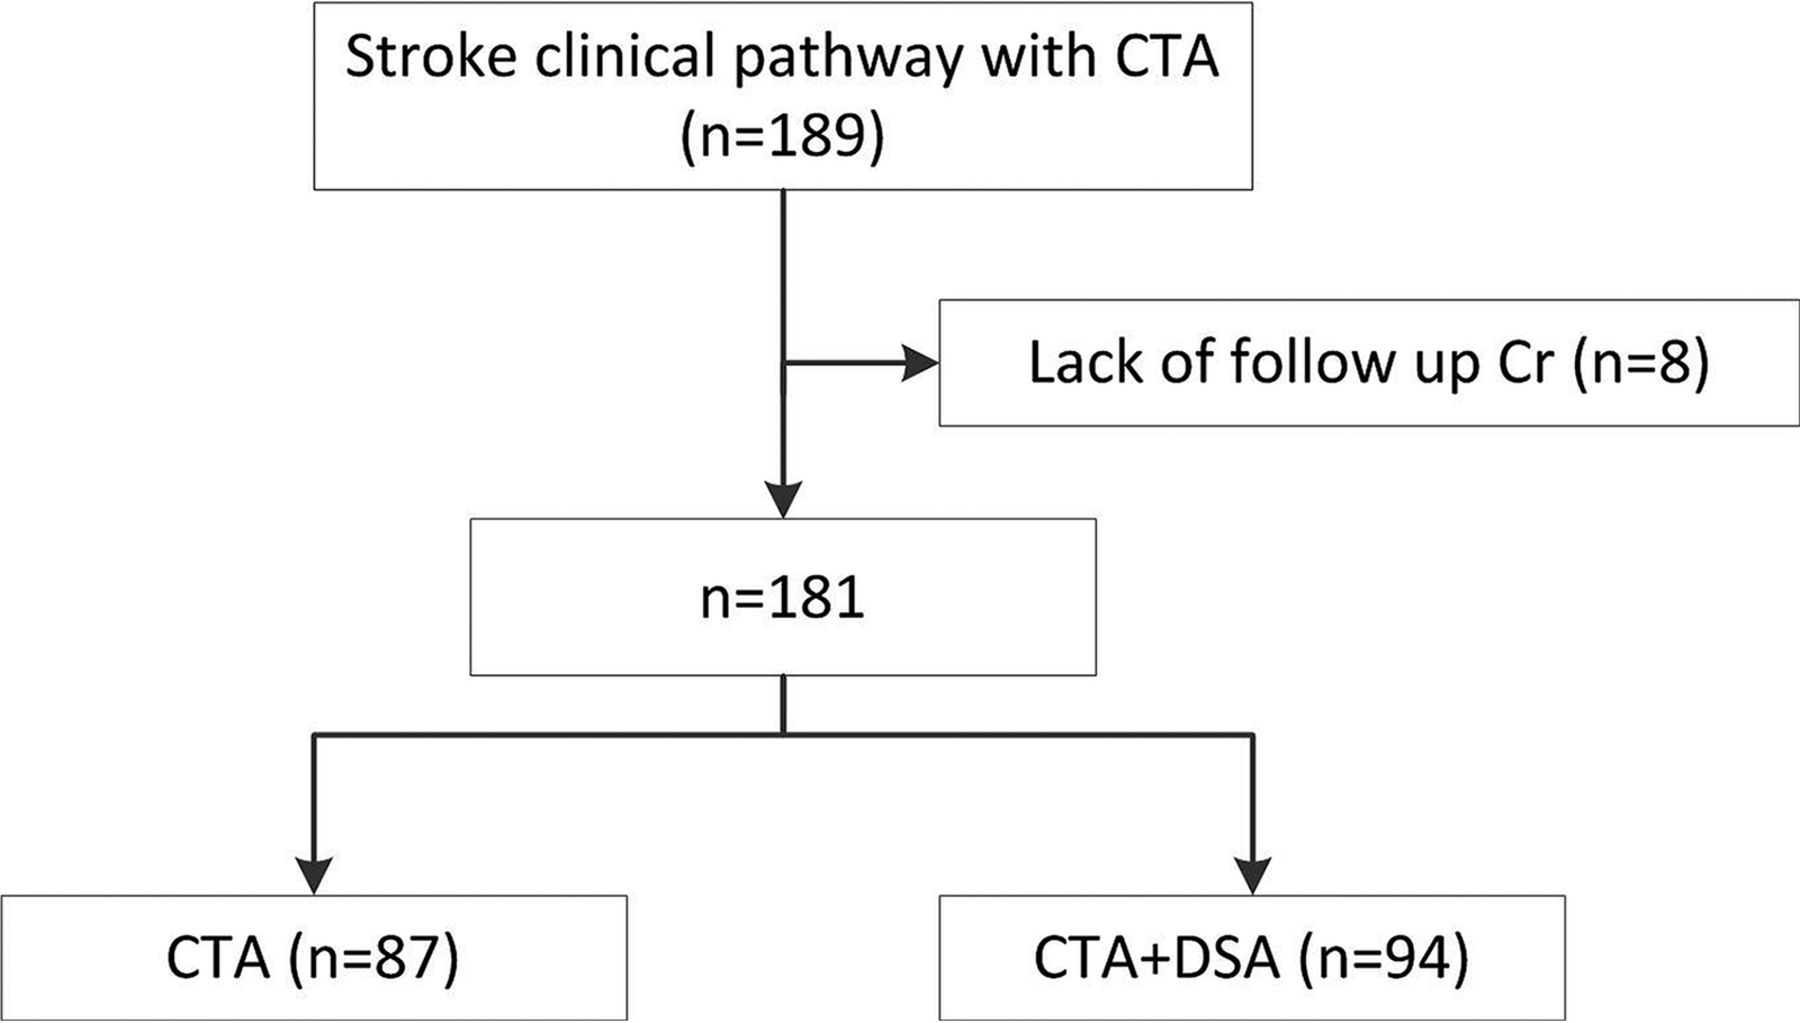
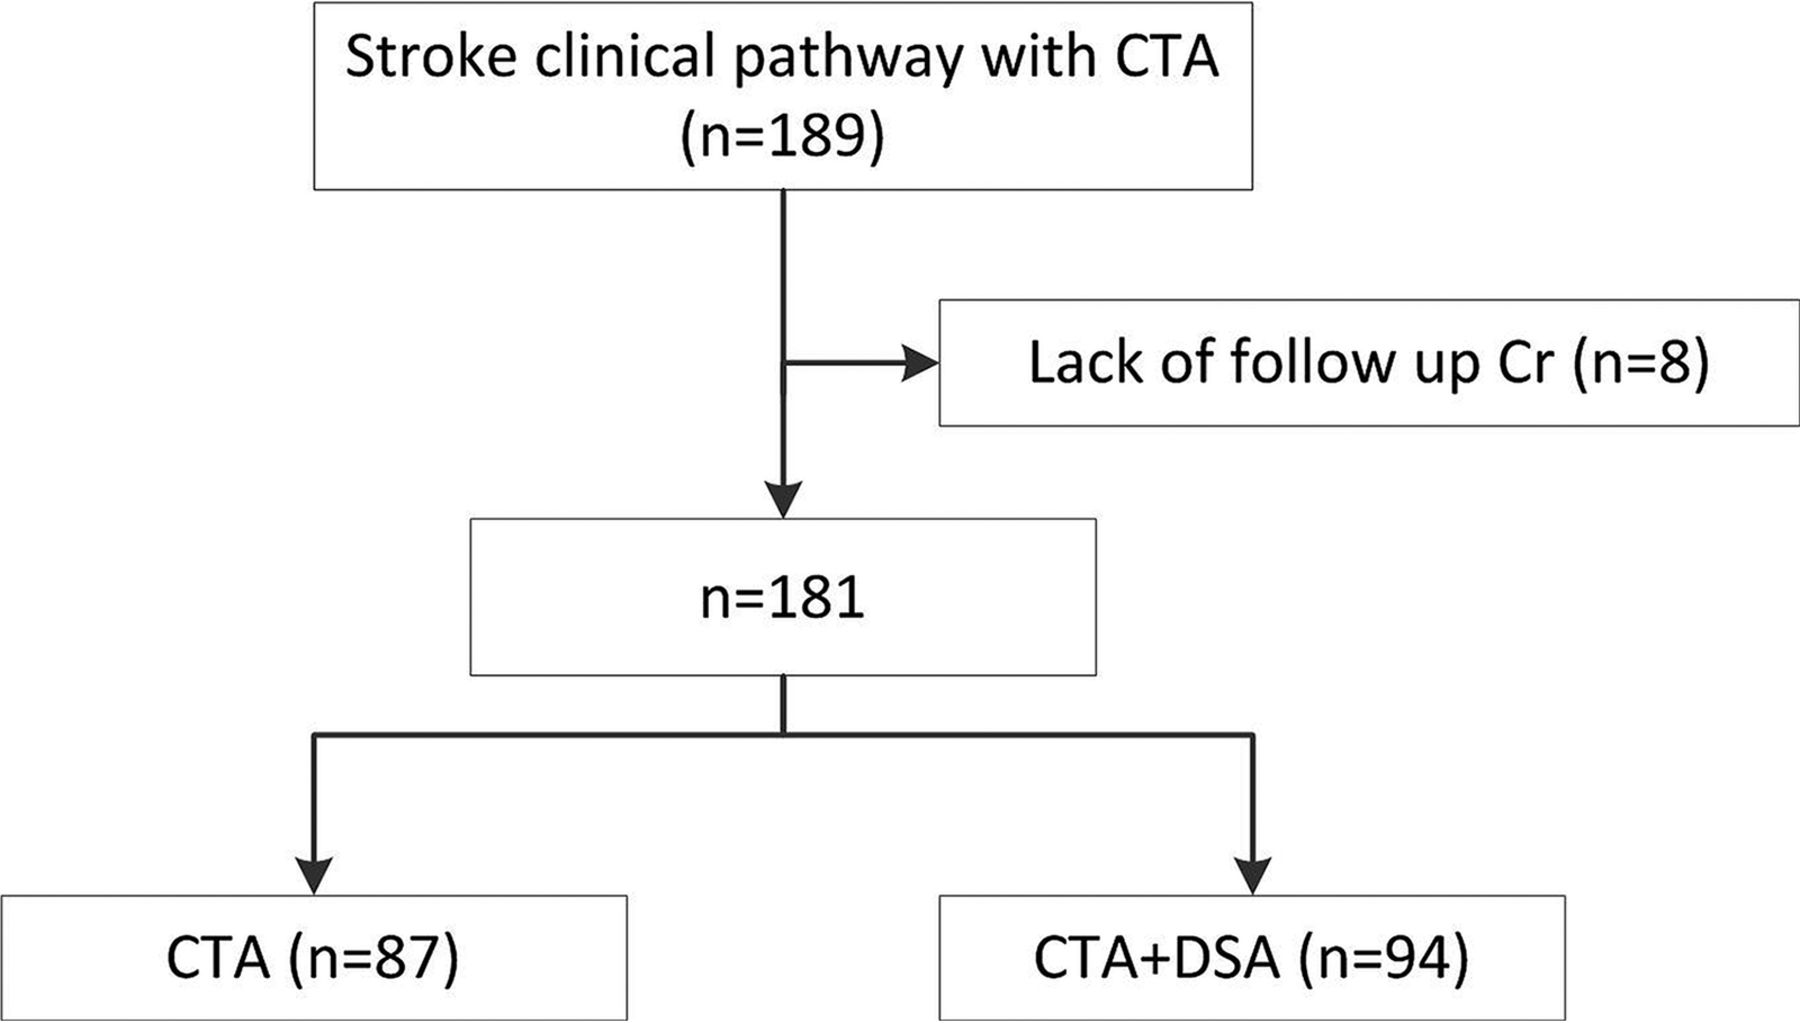
    Altogether, 181 patients with AIS were included in this study (Figure and Table 1), of whom 87 underwent CTA examinations and 94 underwent both CTA and DSA examinations. All patients were given intravenous normal saline for hydration.
    FIGURE.
    Flow chart of the study.
    Table 1:
    Baseline demographics and characteristicsa
    The mean serum creatinine levels are shown in Table 2. Nine patients (5.0%) met the diagnostic criteria for AKI: 2 in the CTA group (2.3%) and 7 in the DSA group (7.4%) (P = .172). On average, patients with AKI had creatinine level increases: 0.24 ± 0.06 mg/dL (31.0% ± 6.9%) in the CTA group and 1.71 ± 2.42 mg/dL (131.6% ± 160.2%) in the DSA group.
    Table 2:
    Incidence of acute kidney injury in 2 study cohorts

    Discussion

    This prospective study showed that the additional use of contrast for endovascular treatment after CTA did not increase the incidence of AKI, consistent with the results of previous studies.10⇓⇓⇓⇓–15
    Although the study was designed prospectively, we did not expect that the postimaging laboratory studies would be unavailable for patients with mild symptoms who left the hospital early. Loss of patients presents a potential risk of biasing the results. In addition, the prevalence of underlying medical comorbidities, such as atrial fibrillation and heart failure, was higher in the DSA group, which may predispose the patients to develop AKI.
    There was no statistically significant difference in AKI incidence between the CTA and DSA groups, though a trend toward a higher incidence of AKI was observed with consecutive, multidose use of contrast (7.4% versus 2.3%). We agree that the benefits of the endovascular treatment most likely outweigh the potential risks of AKI because these benefits were confirmed in 5 prior trials.4⇓⇓⇓–8 We do think that controlling the total volume of contrast medium during the endovascular treatment is still necessary.
    The definition of AKI varied in previous studies, ranging from an increase in the serum creatinine level of 25%–50% from the baseline level to an absolute increase of 0.3 or 0.5 mg/dL.10⇓⇓⇓⇓–15 In the current study, we chose a >25% increase in the serum creatinine level as the threshold for an AKI diagnosis, which was more sensitive than the criterion of a >50% increase or a >0.5-mg/dL increase, and it may have led to a higher incidence of AKI (7.4% in the DSA group) compared with the rate of AKI reported in previous studies (0%–9%) with varying standards.10⇓⇓⇓⇓–15

    Conclusions

    This prospective study showed that consecutive, multidose use of contrast for CTA and DSA did not significantly increase the rate of AKI in patients with AIS compared with the 1-time use of contrast for CTA. The trend toward an increased AKI incidence after using more contrast should be further investigated.

    Footnotes

    • Zhen Yu Jia and Shao Xian Wang contributed equally to this work.
    • This work was supported by the Construction Program of Jiangsu Provincial Clinical Research Center Support System (BL 2014084). Clinical Trial Registration: http://www.clinicaltrials.gov; NCT03132558.
    Indicates open access to non-subscribers at www.ajnr.org

    REFERENCES

    1. 1.↵
    2. 2.↵
    3. 3.↵
    4. 4.↵
    5. 5.↵
    6. 6.↵
    7. 7.↵
    8. 8.↵
    9. 9.↵
    10. 10.↵
    11. 11.↵
    12. 12.↵
    13. 13.↵
    14. 14.↵
    15. 15.↵
    • Received September 17, 2018.
    • Accepted after revision November 18, 2018.
    View Abstract

    Wednesday, March 20, 2019

    Bridging deadly regional divide telestroke set to save and improve lives - Australia

    But they say nothing about getting to 100% recovery. That is the goal of all stroke survivors.  Unless survivors step up and take this over, there will never be the correct goal. Having a 'fair go' is not good enough.  YOU need to write the National Heart and Stroke Action Plan to have a goal of 100% recovery.  The stroke medical 'professionals' can't be allowed to write the goals in it.

    Bridging deadly regional divide telestroke set to save and improve lives - Australia

    March 19, 2019
    The Stroke Foundation has welcomed the Australian Labor Party commitment to establish, if elected, an $11.9 million National Telestroke Network.

    The network will harness the latest in telehealth technology to ensure all Australians have a fair go at surviving and living well after stroke.

    Stroke Foundation Clinical Council Chair Professor Bruce Campbell said the network would transform emergency stroke treatment for regional and rural Australians.

    “Advancements in stroke treatments mean, for many Australians, stroke no longer inevitably leads to death and disability. However, regional and rural Australians have been missing out on these treatments as most of our stroke specialists are located in cities,’’ Professor Campbell said.

    “A national telestroke network will remove geographical barriers to these stroke treatments, it will save lives and boost the capacity of our regional doctors to treat stroke.

    “Surviving and living well after stroke will no longer be determined by your postcode.’’

    Under the network, neurologists would provide around the clock support to regional clinicians. Specialists will be available to review a patient’s brain scan via computer software remotely, then provide diagnosis, timely treatment advice and assist with rapid transfer to city hospitals for more advanced treatments where appropriate.

    Stroke Foundation Chief Executive Officer Sharon McGowan said time was critical when treating stroke.

    “Time saved in treating stroke is brain saved,’’ Ms McGowan said.

    “When a stroke strikes, it attacks up to 1.9 million brain cells a minute. Treatments can stop the damage, but they require specialist diagnosis and must be given quickly.”

    Regional Australians are 19 percent more likely to suffer a stroke than people in metropolitan areas. Currently, regional Australians are also more likely to die or have a significant disability as a result of stroke because of limited access to specialist stroke treatment and care(NOT RECOVERY!).

    The establishment of a National Telestroke Network will strengthen, connect and build on the well-established Victorian telestroke network, as well as pilot projects underway in New South Wales, South Australia and Western Australia. It will deliver all Australians access to emergency stroke treatment when and where they need it.

    Ms McGowan also welcomed the inclusion of F.A.S.T. community education and clinical registry funding to support the roll out of the telestroke network, ensuring its benefits were maximised.

    In response to the Australian Labor Party announcement, Stroke Foundation has called for cross-party support for a National Telestroke Network to ensure all Australians have the best opportunity to survive and live well after stroke.

    “Stroke is one of this country’s biggest killers and a leading cause of disability. Yet, it can be prevented, and it can be treated,’’ Ms McGowan said.

    “The establishment of a National Telestroke Network is a vital step towards changing the state of stroke in this country.”

    The development of a National Telestroke Network was a key action highlighted in the development and draft of the National Heart and Stroke Action Plan. Work is underway to finalise the Action Plan, identifying gaps in the current health system and prioritise actions that can be taken to reduce the toll of stroke and heart disease in our communities.

    Labor’s plan:
    $11.9 million to build a Telestroke Network including:
    $3 million for the Australian Stroke Clinical Registry to ensure the Network’s data is captured
    $600,000 for education programs to teach the community about the F.A.S.T signs of stroke
    For more on the state of stroke in regional Australia.

    Stroke facts 
    One stroke every nine minutes.
    56,000 strokes in Australia this year.
    475,000 stroke survivors living in the community.
    Regional Australians 19 percent more likely to suffer a stroke, and are also more likely to die or be left with a significant disability as a result of stroke.
    It is estimated 20 strokes a day are impacting Australians of working age.
    By 2050, it is estimated the number of strokes experienced by Australians will double to 132,500 and there will be around one million stroke survivors living in our community.

    Sunday, November 18, 2018

    eTICI reperfusion: defining success in endovascular stroke therapy

    Shit, they are measuring the wrong thing. The correct measurement is 100% recovery, NOT this intermediate stage. No wonder no one ever solves anything in stroke. They aren't even trying for the right endpoint.  Reperfusion was a success, but the patient is still disabled. Not my definition of success or any stroke survivors.  And no measurement of reperfusion injury? Does anyone even know how to do research?

    eTICI reperfusion: defining success in endovascular stroke therapy


    Abstract

    BACKGROUND:

    Revascularization after endovascular therapy for acute ischemic stroke is measured by the Thrombolysis In Cerebral Infarction (TICI) scale, yet variability exists in scale definitions. We examined the degree of reperfusion with the expanded TICI (eTICI) scale and association with outcomes in the HERMES collaboration of recent endovascular trials.

    METHODS:

    The HERMES Imaging Core, blind to all other data, evaluated angiography after endovascular therapy in HERMES. A battery of TICI scores (mTICI, TICI, TICI2C) was used to define reperfusion of the initial target occlusion defined by non-invasive imaging and conventional angiography.

    RESULTS:

    Angiography of 801 subjects was available, including 797 defined by non-invasive imaging (154 internal carotid artery (ICA), 583 M1, 60 M2) and 748 by conventional angiography (195 ICA, 459 M1, 94 M2). Among 729 subjects in whom the reperfusion grade could be established, using eTICI (3=100%, 2C=90-99%, 2b67=67-89%, 2b50=50-66%) of the conventional angiography target occlusion, there were 63 eTICI 3 (9%), 166 eTICI 2c (23%), 218 eTICI 2b67 (30%), 103 eTICI 2b50 (14%), 100 eTICI 2a (14%), 19 eTICI 1 (3%), and 60 eTICI 0 (8%). Modified Rankin Scale shift analyses from baseline to 90 days showed that increasing TICI grades were linked with better outcomes, with significant distinctions between TICI 0/1 versus 2a (p=0.028), 2a versus 2b50 (p=0.017), and 2b50 versus 2b67 (p=0.014).

    CONCLUSIONS:

    The benefit of endovascular therapy in HERMES was strongly associated with increasing degrees of reperfusion defined by eTICI. The eTICI metric identified meaningful distinctions in clinical outcomes and may be used in future studies and routine practice.

    KEYWORDS:

    angiography; stroke
    PMID:
    30194109
    DOI:
    10.1136/neurintsurg-2018-014127

    Thursday, June 14, 2018

    New stroke drug melts brain clots faster, costs less and improves recovery

    Do you really think your stroke hospital is innovative enough to read and implement ANY research that might help stroke patients? Up to you, you can demand your hospital create a process to update stroke protocols OR you can hope like hell that it will be there when you need it.  I know I shouldn't be telling the stroke medical world what to do  since I'm not medically trained. You need no medical training to know that current stroke hospital results are a disaster.

    New stroke drug melts brain clots faster, costs less and improves recovery

    A breakthrough in stroke medical research found a drug, traditionally used for heart attacks, dissolves blood clots in the brain faster and more effectively than standard stroke drugs.
    The EXTEND-IA TNK randomised clinical trial, led by The Royal Melbourne Hospital (RMH) and the University of Melbourne, compared the effectiveness of two drugs, Tenecteplase and Alteplase, in dissolving stroke-causing blood clots in the brain, before patients went on to have clot retrieval surgery.
    RMH neurologist, Head of Stroke and study co-principal investigator Bruce Campbell said the study, published in the New England Journal of Medicine, found the drug Tenecteplase was life changing in treatment of ischemic stroke.
    “Our study showed that the use of Tenecteplase restored blood flow to the brain before clot retrieval surgery in double the number of patients compared to Alteplase (22 per cent compared with 10 per cent of patients),” Associate Professor Campbell said.
    “For one in five patients treated with Tenecteplase, clot retrieval surgery was not required and the earlier restoration of blood flow was associated with improved functional recovery in Tenecteplase-treated patients.
    “Tenecteplase can be given over 10 seconds compared to the one-hour infusion of Alteplase, which has practical advantages when transferring patients between hospitals for clot retrieval surgery and is also less expensive,” Associate Professor Campbell said.
    EXTEND-IA TNK involved 202 participants, across 13 hospitals in Australia and New Zealand, who either received Tenecteplase or Alteplase.
    Peter Mitchell, Director Neurointervention Service and study co-principal investigator at the RMH, said the study results were likely to change stroke treatment guidelines and clinical practice.
    “In treating stroke, it is critically important to restore blood flow to the brain as soon as possible,” said Professor Mitchell, head of the Statewide Endovascular Clot Retrieval Service at the RMH.
    “This is achieved most effectively with clot retrieval surgery, but when the surgery is delayed for patients transferred from hospital to hospital, Tenecteplase is more likely to help restore blood flow than Alteplase.
    “Tenecteplase is now likely to become the preferred medication for clot dissolving in stroke patients who need clot retrieval surgery,” Professor Mitchell said.
    The EXTEND-IA TNK study was supported by grants from the National Health and Medical Research Council of Australia, the Australasian College of Physicians, The Royal Melbourne Hospital Foundation, the National Heart Foundation of Australia and the Stroke Foundation of Australia. Trial infrastructure was supported by an unrestricted grant from Medtronic who had no role in study design, conduct or analysis.
    (Source: University of Melbourne, New England Journal of Medicine)