Changing stroke rehab and research worldwide now.Time is Brain! trillions and trillions of neurons that DIE each day because there are NO effective hyperacute therapies besides tPA(only 12% effective). I have 523 posts on hyperacute therapy, enough for researchers to spend decades proving them out. These are my personal ideas and blog on stroke rehabilitation and stroke research. Do not attempt any of these without checking with your medical provider. Unless you join me in agitating, when you need these therapies they won't be there.

What this blog is for:

My blog is not to help survivors recover, it is to have the 10 million yearly stroke survivors light fires underneath their doctors, stroke hospitals and stroke researchers to get stroke solved. 100% recovery. The stroke medical world is completely failing at that goal, they don't even have it as a goal. Shortly after getting out of the hospital and getting NO information on the process or protocols of stroke rehabilitation and recovery I started searching on the internet and found that no other survivor received useful information. This is an attempt to cover all stroke rehabilitation information that should be readily available to survivors so they can talk with informed knowledge to their medical staff. It lays out what needs to be done to get stroke survivors closer to 100% recovery. It's quite disgusting that this information is not available from every stroke association and doctors group.

Wednesday, September 30, 2026

Your voice may reveal how fast and how well you're aging

 You'll not want to allow this testing until you are 100% recovered.

Your voice may reveal how fast and how well you're aging

A large study shows that machine-learning clocks based on speech can estimate chronological age and may also offer a window into brain aging, biological aging, cognitive health, cumulative burden and dementia.

The study, published in the journal Science Advances, describes a "speech clock" that estimates a person's chronological age from hundreds of acoustic and linguistic characteristics of their speech. The difference between a person's actual age and their speech-predicted age (called the speech age gap) was also associated with multiple independent markers of biological aging, brain health, cognition, social adversity and dementia.

The study analyzed 2,928 Spanish-speaking participants from Argentina, Chile, Colombia, Mexico and Peru, including healthy adults and people with mild cognitive impairment, Alzheimer's disease and different forms of frontotemporal dementia.

Rather than looking at a single property of the voice, the researchers used machine learning to analyze hundreds of features capturing how people speak and what they say. These included speech rate and pauses, pitch, emotional content, vocabulary, semantic precision, and the amount and organization of verbal output. Machine-learning models combined these features to estimate chronological age and generate an individual speech age gap.

Speech age tracks biology and cognition

People whose speech appeared older than expected for their chronological age also showed signs of accelerated aging across several biological and clinical systems. The speech age gap was associated with brain age measured using structural and functional neuroimaging. It was also related to epigenetic aging, measured through three independent DNA-methylation clocks that estimate how biologically "old" the body appears based on age-related chemical changes in DNA.

Greater speech-age acceleration was associated with poorer global cognition, executive function, functional abilities and several forms of memory. Importantly, these relationships were not restricted to language tests: Speech age was also related to performance on nonlinguistic cognitive measures.

Wider gaps in dementia groups

The speech clock also differentiated healthy individuals from people with dementia. Healthy participants showed the lowest speech age gaps, while progressively larger gaps were observed across Alzheimer's disease and forms of frontotemporal dementia.

The complete speech-age measure discriminated clinical groups better than individual acoustic or linguistic features considered separately. In Alzheimer's disease, it was associated with higher levels of plasma p-tau217, one of the most important blood biomarkers of Alzheimer's pathology. The same speech-derived measure also tracked cognitive and clinical functioning.

Social adversity leaves a speech signal

Speech also carried a social signal. Among healthy individuals and people with Alzheimer's disease and other dementia, accelerated speech aging was associated with a more adverse social exposome: a combination of lifelong factors such as education, financial conditions, food insecurity, health care access and early-life experiences.

"Our voice appears to contain much more information about aging than we previously recognized," said Agustin Ibanez, professor of brain health at the Global Brain Health Institute and School of Medicine at Trinity College Dublin and senior author of the study.

"It captures both the passage of chronological time and signals coming from cognition, the brain, systemic biology and even our accumulated social environment. This raises the possibility that something as simple and accessible as speech clocks, maybe combined with biomarkers, could eventually complement much more expensive measures of aging."

A lower-cost window into aging

The implications are substantial. Many current measures of biological aging require MRI scanners, blood samples, molecular assays or specialized clinical assessments. Speech, in contrast, can be recorded remotely, repeatedly, noninvasively and at very low cost. This could be particularly important in countries and communities where advanced diagnostic technologies are difficult to access.

Because the study was conducted across five Latin American countries (a region historically underrepresented in dementia research), it also provides evidence that sophisticated biomarkers of aging do not necessarily need to depend exclusively on expensive technologies developed in high-resource settings.

Clinical use requires further validation

The researchers emphasize, however, that the speech clock is not yet a diagnostic test for dementia. The study was primarily cross-sectional, meaning it cannot establish whether an older-appearing speech profile predicts who will subsequently develop cognitive decline or dementia. Longitudinal studies, validation in additional languages and cultures, and testing in more naturalistic speech settings will be required before clinical implementation.

"The broader finding is nevertheless striking: A person's voice may provide a remarkably compact readout of multiple dimensions of aging," Ibanez added.

"From chronological age to brain aging, epigenetic aging, cognition, Alzheimer's-related pathology, social exposures and dementia phenotypes, information traditionally obtained through very different and often expensive measurements appears to converge, at least partly, in the way we speak.

"If confirmed longitudinally and across populations, speech could ultimately become one of the most scalable tools for monitoring healthy and accelerated aging—potentially transforming an everyday human behavior into a window onto the biology of aging."

Publication details

Hernan Hernandez et al, Speech clocks decode dementia phenotypes, social exposome, and biological aging, Science Advances (2026). DOI: 10.1126/sciadv.aef9864. www.science.org/doi/10.1126/sciadv.aef9864

Journal information: Science Advances 

The question doctors could ask to estimate death risk in old patients

 Your competent? doctor is responsible for getting you walking properly so you don't have a higher mortality risk! Is your doctor up to that task? 

NO? So, you will get him/her fired then, right?

My doctor knew nothing about recovery and did nothing. Which is why my gait is still screwed up; 15 degree leftward angle of left foot, no push-off, no free swinging lower leg, hyperextension of left knee.

The question doctors could ask to estimate death risk in old patients

“Do you have trouble walking?” could be one of the most important questions doctors could ask older patients to evaluate their mortality risk, according to a new large-scale research review.

Healthcare systems worldwide seek to find simple ways to identify older adults with a high need for hospitalisation.

Hospitals also need to assess whether their healthcare response is distributed according to need rather than social position.

Previous studies have established that grip strength, gait, and balance can predict the risk of chronic diseases in older people.

Now, a new study reveals that walking difficulty can also be a practical sign of higher mortality risk and health need.

In the research, scientists assessed data from six of the world’s largest ageing studies, including health information from older adults living in China, England, the United States, South Korea, Mexico, and continental Europe.

The studies collectively followed hundreds of thousands of older adults using comparable questionnaires, which included questions about walking difficulty.

By analysing this data, scientists could probe whether walking difficulty indeed determined health status in older people across economies, cultures, and health systems.

“Walking difficulty is inexpensive to ascertain and widely harmonisable across ageing cohorts, but its value as a denominator for healthcare equity assessment has been less well characterised,” researchers wrote.

They found that walking difficulty could be used to identify populations with substantially greater measured health need.

Scientists found that older adults who reported walking difficulty faced nearly double the death risk during follow-up than those who walked comfortably.

“Walking difficulty was associated with morbidity, falls, depressive symptoms, disability, and hospitalisation,” they wrote in the study published in the journal BMC Medicine.


“In clinical and community-facing settings, the value of a walking-difficulty question lies in its simplicity rather than in technological precision. It can be asked quickly, requires no equipment, and identifies a group in which multi-morbidity, depressive symptoms, falls, disability, and hospitalisation are more common,” researchers explained.

However, they caution that the study does not estimate a causal effect of walking difficulty.

“Taken within these boundaries, walking difficulty offers a practical way to move from risk recognition to health-system auditing in older populations,” researchers said.

“It identifies a high-need group using a low-cost functional question and makes it possible to ask whether response among those with evident need remains socially patterned,” they explained.

The Independent is the world’s most free-thinking news brand, providing global news, commentary and analysis for the independently-minded. We have grown a huge, global readership of independently minded individuals, who value our trusted voice and commitment to positive change. Our mission, making change happen, has never been as important as it is today.

Robotic Hip Exoskeleton Shows Promise for Helping Stroke Patients Regain Their Stride

 Have your competent? doctor compare all these earlier ones brought in for testing to this new one!


Oh! NOTHING HAS BEEN TESTED? PURE INCOMPETENCE!

Video at link.

Robotic Hip Exoskeleton Shows Promise for Helping Stroke Patients Regain Their Stride

More than 80% of stroke survivors experience walking difficulty, significantly impacting their daily lives, independence, and overall quality of life. Now, new research from the University of Massachusetts Amherst pushes forward the bounds of stroke recovery with a unique robotic hip exoskeleton, designed as a training tool to improve walking function. This invites the possibility of new therapies that are more accessible and easier to translate from practice to daily life compared to current rehabilitation methods. Following stroke, people often experience walking asymmetry, where one step is shorter than the other. The study, published in IEEE Transactions on Neural Systems and Rehabilitation Engineering, reveals that the robotic hip exoskeleton has the potential to effectively train individuals to modify their walking asymmetry, presenting a promising avenue for stroke rehabilitation.The approach employed by the robotic exoskeleton is inspired by split-belt treadmills, which are specialized machines with two side-by-side belts moving at different speeds. Prior research has shown that repeated training on a split-belt treadmill can reduce walking asymmetry in stroke patients.Wouter Hoogkamer, assistant professor of kinesiology and author on the paper, has spent the last decade studying split-belt treadmills. “Split-belt treadmill training is designed to exaggerate a stroke patient’s walking asymmetry by running the belts under each foot at different speeds. Over time, the nervous system adapts, such that when the belts are set to the same speed, they walk more symmetrically.”Unfortunately, there are limits to the benefits gained from treadmill-based training methods. “What is learned on a treadmill does not completely transfer to overground contexts,” says Banu Abdikadirova, mechanical and industrial engineering doctoral candidate and lead study author. “This is because walking on a treadmill is not exactly the same as walking overground.”“The ultimate goal of gait rehabilitation is not to improve walking on a treadmill – it is to improve locomotor function overground,” says Meghan Huber, assistant professor of mechanical and industrial engineering and senior author on the paper. “With this in mind, our focus is to develop methods of gait rehabilitation that translate to functional improvements in real-world contexts.”With this motivation, the UMass team sought a novel way to exaggerate walking asymmetry without a treadmill. This proof-of-concept study showed that applying resistive forces about one hip joint and assistive forces about the other with their exoskeleton mimicked the effects of split-belt treadmill training in neurologically intact individuals. Now that the research team has proven that the exoskeleton can alter gait asymmetry, they are eager to move their research into overground contexts that are more akin to the real world.“Because our exoskeleton is portable, it can be used during overground walking,” says Mark Price, a postdoctoral researcher in mechanical and industrial engineering and kinesiology and author on the paper. “We can build upon the successes of split-belt treadmill training with this device to enhance the accessibility of gait training and enhance the transfer of training benefits into everyday walking contexts.”The researchers also plan to expand their work by measuring the neural changes caused by walking with the exoskeleton and testing this new method on stroke survivors. “A portable exoskeleton offers numerous clinical benefits,” says Abdikadirova. “Such a device can be seamlessly integrated into the daily lives of chronic stroke survivors, offering an accessible way to increase training time, which is critical for improving walking. It can also be used during early intervention in hospitals for improved functional outcomes.”The robotic hip exoskeleton is just one of the innovative devices designed to study and enhance gait function developed by the collaborative team of undergraduate students, graduate students, and postdoctoral researchers from the Human Robot Systems Lab, led by Huber, and the Integrative Locomotion Lab, led by Hoogkamer. “It is inspiring to witness the innovations that emerge when individuals from diverse backgrounds unite under a shared mission,” says Huber. “Only through this type of cross-disciplinary research can we engineer technologies that can have a meaningful impact on people's lives.”

Low-cost, Sensor-equipped Insole Developed to Monitor Gait of Patients with Mobility Impairments

 Ask your competent? doctor if this is better than all these earlier ones! And when monitoring is done are THERE EXACT PROTOCOLS TO FIX THE PROBLEMS?

Or this:

Low-cost, Sensor-equipped Insole Developed to Monitor Gait of Patients with Mobility Impairments

AMHERST, Mass. – An interdisciplinary team of University of Massachusetts Amherst researchers has developed a low-cost shoe insole, equipped with force-sensitive resistors (FSR), that aims to improve the management of health conditions that impair mobility, such as stroke, Parkinson’s disease and osteoarthritis.

The insole “measures two important kinetic parameters that are relevant to how people walk; that is, the ground reaction force (GRF) and center of pressure (CoP),” says lead investigator Sunghoon Ivan Lee, assistant professor in the Manning College of Information and Computer Sciences. “Those parameters contain very important information, especially for people who have gait problems.”

Image
brandon oubre
UMass Amherst lead author Brandon Oubre

Lee’s 2018 National Institutes of Health Trailblazer Award for Young Investigators helped fund the research, published recently in the journal IEEE Transactions on Biomedical Engineering and selected as a Featured Article. In addition to lead author Brandon Oubre, an information and computer sciences Ph.D. candidate, Lee collaborated with kinesiologist Katherine Boyer, a gait expert, and Ph.D. candidate Skylar Holmes, both from the School of Public Health and Health Sciences.

Information from the insole sensors could help clinicians conveniently monitor disease progression over time and make earlier interventions for people with neurological, musculoskeletal and other conditions that affect mobility.       

Image
banner illustration

Currently these gait parameters can only be measured in a lab with expensive scales and specialized cameras that track reflective “dots” attached to the body. “It’s not easily accessible for people, especially those living in rural or underserved areas, so it’s difficult to monitor how these parameters evolve throughout the course of their therapy or rehabilitation,” Lee says. “And the lab environment does not really represent how they walk naturally outside of the laboratory.”

The researchers’ challenge was to come up with an inexpensive, wearable solution to accurately measure where the pressure is centered on the sole when a person walks.

Image
highlight illustration

“For healthy individuals, there’s a normal way to put the pressure on the ground when you walk: You hit with the heel and then you will roll around the outer edge of your sole, then your toes will be in contact with the ground and then finally you take off,” Lee says. “But these inexpensive sensors are not very accurate, that’s the caveat.”

So the research team built an artificial-intelligence algorithm to process the sensors’ data, resulting in accurate information about the kinetic parameters. “That’s the key contribution of our paper,” Lee says.

The research found that the insole devices accurately estimated GRF and CoP based on models, despite the deficiencies in force sensitive resistor data.

One day, the researchers hope that insoles with sensors could be used in clinics and patients’ home environments to provide real-time data about their walking gait, sent wirelessly to health care providers.

“There will be many hurdles to enable this vision, but that’s the ultimate thing that we’re aiming for,” Lee says.

Wearable Stroke Rehabilitation Device Gives Patients the Upper Hand

 Your mentors have told you that monitoring is useless unless you have EXACT RECOVERY  PROTOCOLS mapped to the deficits shown! NO? Find better mentors that know something about stroke recovery, not just fairly useless monitoring! And did your mentors show you all the wearables out there? Or were they incompetent in not knowing of them?

Wearable Stroke Rehabilitation Device Gives Patients the Upper Hand

A team led by University of Massachusetts Amherst researchers has developed a wearable wrist device powered by a machine-learning algorithm that can continually track changes in arm movement impairment caused by strokes. Monitoring changes throughout the entire rehabilitation process will allow clinicians to make real-time adjustments to therapy programs for tailored interventions and personalized care instead of the one-size-fits-all current standard. 

Image
Ivan Lee points at a computer monitor while in discussion with Ryan Wang
Ivan Lee (left) and Ryan Wang

“We are the first group to actually show that, using wearable data, we can extract information about patients’ motor severity, which clinicians can actually use to determine whether their intervention is effective or not,” says Sunghoon Ivan Lee, associate professor in the Manning College of Information and Computer Sciences at UMass Amherst and corresponding author on the paper describing this new technology. The research was completed alongside colleagues from Washington University in St. Louis, Shirley Ryan AbilityLab and Harvard Medical School/Mass General Brigham.

Annually, more than 795,000 Americans experience strokes, with upper-limb mobility issues affecting up to 77% of patients immediately following the event. About 40% of patients continue to have chronic issues, posing a major limitation to independent living.

While physical therapy improves these mobility issues, it is not without its limitations. Currently, progress is measured by a clinician’s observational assessment, which takes about 30 minutes. Because this is a time-consuming process, assessment typically occurs only pre- and post-rehabilitation.

“That means during that therapy process, neither the patient nor the therapist has a clear idea of how patients are responding to the treatments that they’re receiving,” says Lee. “Currently, clinicians aren’t able to see if patients are responding to the prescribed exercises, and patients have no way of knowing how they are progressing.”

With a wearable monitor, recovery data collection can be ongoing and occur outside of therapy sessions, allowing the therapist to make timely adjustments to treatment strategies for truly personalized rehabilitation.

Also, tracking movement in a patient’s real-life environment may be more indicative of true performance, as opposed to movement that is artificially produced in a clinic. The wrist-wearable also captures movement at all times of day, versus at just one snapshot of time. And finally, patients may find that tracking their own recovery progress increases their engagement in the therapy practices and keeps them motivated.

Lee is optimistic that this increased transparency will translate to improved therapy outcomes.

An accelerometer sensor in the device captures upper-limb movement, which is then interpreted by a machine-learning algorithm developed by Lee and his graduate student and the lead author on the paper, Ryan Wang.

“[Movement and impairment severity] are related because the less severe you are, the more likely you’re going to move a lot, but they’re not exactly the same,” says Lee. “Increasing the use of the limbs—yes, we can encourage the person to make use of the limb more. But patients cannot make instant changes to motor severity through short-term behavior change.”

Their model, described in Science Translational Medicine, was trained on accelerometer data and clinician assessment scores of subacute (one week to six months after a stroke) stroke patients and healthy individuals. They found that their algorithm was 40-50% more accurate—meaning a better reflection of the patient’s true condition—compared to clinician evaluation.

In addition to the clinical application of using the device to inform personalized interventions, Lee’s work demonstrated that the device has a strong research application. In recreating a previous study using their own digital biomarker instead of clinician observations, the researchers found that they generated statistically significant results with 50% fewer participants.

“We can get a clear idea of the effectiveness of the intervention using a lower sample size and far fewer resources,” says Lee. This can expedite the research process and reduce costs.”

This work was supported by the National Institutes of Health. With a provisional patent filed, Lee is pursuing commercialization through the startup Lumid Health with support from UMass Amherst Institute for Applied Life Sciences’ Translational Seed Award, the UMass Office of Technology Commercialization & Ventures’ (OTCV) Technology Development Fund and participation in the NSF I-Corps Training Program.

To further develop the technology, Lee’s research partners are currently recruiting stroke patients for a study held at the Spaulding Rehabilitation Hospital in Boston. Those interested in participating can see the inclusion criteria and apply here.

Ethics in Neurology: Preserving Patient Autonomy in Stroke Care

 I'll ask a better question. Is it ethical to not tell your patient you KNOW NOTHING ABOUT 100% RECOVERY!

And that their treatment with tPA only fully works 12% of the time 

Ethics in Neurology: Preserving Patient Autonomy in Stroke Care

Neurologists are first introduced to the ethical principle of informed consent during medical school. They learn that informed consent is central to high-quality patient care, whether a patient is signing a consent form before surgery or discussing the risks and benefits of a treatment with their physician. This principle promotes respect for patient autonomy and ensures that physicians do not violate patients’ right to participate in decisions about their care. During medical school, neurologists may begin to see these principles as part of their emerging professional identity and recognize that, like their patients, they would not want to be excluded from important decisions about their own lives and well-being.

These principles can become harder to apply during residency, when increasing workloads leave less time for patient discussions. For some treatment decisions, it may seem easier to leave clinical uncertainty unacknowledged than to explain its complexities and nuances. A cognitively impaired patient may have limited ability to understand the information, while another patient may simply want the physician to decide. During an emergency, clinicians may have to make decisions before a full discussion is possible. With experience, informed consent becomes easier and more efficient, but some clinical situations remain challenging.

Consent for thrombolytics in acute ischemic stroke is one such situation. First, there is the time pressure. Thrombolytics are typically delivered in emergency settings, when neurons die with every passing minute. Second, physicians must quickly assess whether the patient has decision-making capacity. If not, they must identify and speak with an authorized surrogate decision-maker. The discussion requires balancing the potential benefits of treatment, including a reduction in significant disability, against the known risks for fatal or severe intracranial hemorrhage and the likelihood of no appreciable treatment effect for most patients.

The ethical challenge is balancing time-sensitive medical care with respect for patients’ values and preferences.

Although these decisions can be difficult for patients and surrogates, they remain subject to informed consent. Yet there is continued disagreement about whether informed consent is required before administering thrombolytics in these situations. Physicians have cited that tissue plasminogen activator (tPA) is FDA-approved, is the standard of care, is a medication rather than a procedure, or is an emergency treatment as justification for not obtaining consent.1 With the exception of the last example, none provides sufficient justification for bypassing informed consent.

When Can Treatment Proceed Without Consent?

The concept of “implied consent” in a medical emergency is well known, but an emergency alone does not justify excluding patients from decisions about their care. In general, foregoing informed consent is ethically justified when a patient cannot consent, no surrogate is available, and waiting for consent would cause significant harm. How long clinicians should attempt to reach a surrogate before treating without consent requires professional judgment and should be individualized to the patient’s clinical needs.

Supporting Time-Sensitive Decisions

The ethical challenge is balancing time-sensitive medical care with respect for patients’ values and preferences. Decision aids can help by incorporating shared decision-making into the informed consent process. Shared decision-making involves informing patients about medically appropriate options and their potential benefits and harms, eliciting their values and preferences, and collaborating on a treatment decision.2 For tPA in acute ischemic stroke, decision aids can help clinicians communicate absolute benefits, risks, and the possibility of no treatment effect while potentially minimizing individual clinician bias.

Despite the availability of decision tools for emergency tPA use, patients and surrogates continue to struggle with these decisions, and up to 34% of otherwise ideal candidates for reperfusion are not treated.3 Racial disparities in treatment and tPA refusal rates also contribute to worse outcomes in some populations.4 The reasons for treatment refusal are not completely understood.

One possible explanation is omission bias, in which patients and physicians overestimate the risks of providing a treatment and favor withholding it. Because risk reflects both probability and magnitude, the severity of a potential outcome such as death may carry disproportionate weight even when its probability is low.

Avoiding informed consent because of time pressure or clinical uncertainty is generally not ethically justifiable. Clinicians can instead simplify the decision-making process to accommodate time constraints and, when clinically appropriate, emphasize treatment as the default when its benefits are clear.5,6 Better decision aids may further support this process. 

Respecting patients’ choices while helping them and their surrogates navigate these decisions can uphold patient autonomy while potentially facilitating better clinical outcomes.

Pomegranate Compound Shows Potential to Improve Heart Function by 80 Percent: Study

 I bet your incompetent? doctor can't figure out that better heart function delivers more oxygenated blood to the brain and that will save more neurons in the first week. NOT DOING ANYTHING WITH THIS IS PURE INCOMPETENCE!

Your doctor does have protocols on walnuts and pomegranates already, right?


Pomegranate Compound Shows Potential to Improve Heart Function by 80 Percent: Study


Scientists Uncover Hidden Link Between Coffee, Gut and Brain Health

 If your incompetent? doctor hasn't created a 24 hour coffee station based on all this earlier research, then s/he IS NOT TRAINABLE!

How coffee protects against Parkinson’s Aug. 2014 

Coffee May Lower Your Risk of Dementia Feb. 2013

Coffee drinkers rejoice! Drinking coffee could lower the risk of Alzheimer’s disease 

And this: Coffee's Phenylindanes Fight Alzheimer's Plaque December 2018

New research suggests drinking coffee may reduce the risk of frailty May 2025

I think I'm in this category:  I never get the jitters or flushed skin.

Genetics determine how much coffee you can drink before it goes wrong

I'm doing a 12 cup pot of coffee a day with full fat milk to lessen my chances of dementia and Parkinsons. Tell me EXACTLY how much coffee to drink for that and I'll change. Yep, that is a lot more than the 400mg. suggested limit, I don't care! Preventing dementia and Parkinsons is vastly more important than whatever problems it can cause! 

Of course, your fuckingly incompetent? doctor did nothing with this from 3+ years ago! And still hasn't created a 24 hour coffee station

Dementia risk could drop by drinking just one shot daily of common beverage  August 2023 

The latest here:

Scientists Uncover Hidden Link Between Coffee, Gut and Brain Health

Popular Supplement Shows Potential to Improve Muscle Strength Without Training: Study

 What is your competent? doctor's EXACT PROTCOL  to prevent muscle loss? Doesn't have any? PURE INCOMPETENCE! 

And you haven't gotten the staff fired yet?

And doesn't know about these either?

Popular Supplement Shows Potential to Improve Muscle Strength Without Training: Study

Lower cognitive test scores among adults in their 60s may signal higher future stroke risk

 Luckily my cognition was not affected at all by my stroke at age 50.

Lower cognitive test scores among adults in their 60s may signal higher future stroke risk


Adults ages 60 to 69 who scored lower on overall thinking ability, memory and mental processing speed tests were more likely to have a future stroke, finds a study in Sweden, published in the Journal of the American Heart Association Research Highlights: People in their 60s without dementia or a previous stroke were at a higher risk of having a stroke in the future if they scored lower on overall thinking ability, memory and information-processing speed tests when compared to their peers who had better scores on the same cognitive tests. The results of a study in Sweden suggest that simple cognitive testing among sexagenarians may offer clues about future stroke risk. Embargoed until 4 a.m. CT/5 a.m. ET Wednesday, Sept. 30, 2026 DALLAS, Sept. 30, 2026 — Adults in their 60s who scored lower on tests of overall thinking ability, memory and how quickly they processed information were more likely to have a stroke years later, according to new research conducted in Sweden, published today in the Journal of the American Heart Association, an open-access, peer-reviewed journal of the American Heart Association. tudy examined the risk of first-time stroke among nearly 5,000 older adults, ages 60 to 80+, and reviewed scores of cognitive function in relation to later stroke incidence. tudy participants, all of whom had no history of dementia, stroke or transient ischemic attack (often known as a mini-stroke), completed several tests that measured overall thinking ability, memory, processing speed, verbal skills and select problem-solving skills. During an average 12 years of follow-up, more than 10% of participants had a first-time stroke. Researchers then estimated the risk of stroke for those with the lowest cognitive function scores compared to people with the highest scores.

The study found that among adults ages 60-69:

  • lower overall thinking ability was linked to an 86% higher risk of stroke;
  • lower memory scores were linked to a 68% higher stroke risk; and
  • lower information-processing speed scores were linked to a 66% higher risk of stroke.

The same cognitive-stroke risk pattern was not seen among adults ages 70-79 or age 80 and older after researchers accounted for other health and lifestyle factors.

“We chose to investigate different age spans because the older population is very diverse. For instance, while many people in their 60s may have only a few medical conditions, people in their 80s often suffer from multiple medical conditions and take numerous medications,” said lead study author Alice Askemyr, M.D., a geriatrics researcher at Lund University and Skåne University Hospital in Malmö, Sweden. “Furthermore, what serves as a risk factor in early life might not serve as one if it is acquired later in life and vice versa.“

She also noted that poor cognitive performance among the younger study participants could indicate that they may have already had an undetected brain injury. “So-called ‘silent’ brain injuries can affect both cognitive functioning and the future risk of stroke,” Askemyr said. “They affect roughly 70% of adults over age 70, so their effects may be easier to detect among people in their 60s, when such injuries and other factors that can affect cognition, including medical conditions and medications, are less common.”

Elisabeth Breese Marsh, M.D., FAHA, chair of the 2026 American Heart Association Scientific Statement, Brain Health Across the Life Span: A Framework for Future Studies, was not involved in the study and noted that, “while it is certainly important for people in their 60s, my advice would be that even people in their 40s and 50s need to be focusing on risk factor modification and habits for good overall brain health.”

Marsh is a professor of neurology and director of the Bayview Stroke Center at The Johns Hopkins University School of Medicine in Baltimore.

“This study, in conjunction with others, supports how important it is to be aggressive in managing vascular risk factors and focusing on brain health in midlife, before many people typically begin to think about it. This would improve both cognitive performance and stroke risk in older age,” she added. “However, because we don’t know for sure if there is something about the cognitive impairment itself that further increases risk of stroke, the study also provides a new potential screening factor to identify those with higher stroke risk.”

According to the American Stroke Association, a division of the American Heart Association, overall health, lifestyle and environment can affect brain health and cognition over time.

Study details, background, design and limitations:

  • The study included 4,912 adults, ages 60-80+, who enrolled in the Good Aging in Skåne project and included health data from the Swedish Board of Health and Welfare.
  • Participants were ages 60 and older (46% men) at enrollment. Data was collected from 2001 to 2023.
  • During an average follow-up period of 12.3 years, 572 participants had a stroke. Data on first-time stroke events were extracted from the Swedish National Patient Register of specialized in- and outpatient care.
  • Cognitive function was assessed using standardized tests of memory, processing speed, verbal fluency and executive function. Scores were combined and grouped by age into low, middle and high cognitive performance. Overall thinking ability was estimated as a composite of all available tests.
  • Study limitations include that the study was observational, meaning it found a link between lower cognitive test scores and stroke risk but cannot prove cause and effect.

The findings may not be generalizable to people living in other countries due to differences in healthcare, socioeconomics and lifestyle habits among countries, Askemyr noted.

Co-authors, disclosures and funding sources are listed in the manuscript.

Studies published in the American Heart Association’s scientific journals are peer-reviewed. The statements and conclusions in each manuscript are solely those of the study authors and do not necessarily reflect the Association’s policy or position. The Association makes no representation or guarantee as to their accuracy or reliability. The Association receives more than 85% of its revenue from sources other than corporations. These sources include contributions from individuals, foundations and estates, as well as investment earnings and revenue from the sale of our educational materials. Corporations (including pharmaceutical, device manufacturers and other companies) also make donations to the Association. The Association has strict policies to prevent any donations from influencing its science content and policy positions. Overall financial information is available here.

The Healthiest Carbs for Longevity, Backed by a 30-Year Study by Super Age

 Does your competent? doctor even have a diet protocol for you? Protocol NOT a guideline!

NO? So, COMPLETELY FUCKING INCOMPETENT THEN?  

And you haven't gotten them fired yet?

The Healthiest Carbs for Longevity, Backed by a 30-Year Study

14 million views of this blog


I must still be interesting to some people. I have never received any direct communications from any stroke medical 'professionals'. Are they scared to talk to me?

First million took from Aug. 2010  to Sept. 2014

Second million from Sept. 2014 to May 2016

Third million from May 2016 to March 2017

Fourth million from March 2017 to November 2018

Fifth million from November 2018 to September 2021

Sixth million from September 2021 to June 2024

Seventh million was from June 2024 to January 2025. 

Eighth million was from January 2025 to June 2025

Ninth million was from June 2025 to September 2025;

Tenth million was from September 2025 to January 2026

Eleventh million was from January 2026 to April 2026

Twelfth million from April 2026 to June 2026

Thirteen million from June 2026 to July 2026

Fourteen million from July 2026 to September 2026

The first post was:


What my doctor should have told me about stroke recovery

Still has the same relevance today. And I'm still as arrogant and opinionated as ever. Arrogance is only true if you don't know what you're talking about! I do know what I'm talking about! 

Your doctor really knows nothing SPECIFIC AND EXACT to get you recovered. Ask him/her; you'll get dissembling rather than specifics! Or you'll get the craptastic saying: 'All strokes are different, all stroke recoveries are different'. In my opinion, that is the comment of a totally incompetent doctor!

Rapamycin Boosts Brain Blood Flow in Alzheimer’s Gene Carriers


Does your competent? doctor have enough brains to see this need and provide cerebral blood flow protocols to prevent loss of neurons during the neuronal cascade of death in the first week? Would this help that goal?

Let's see how long your doctor has been incompetent in rapamycin use.

Rapamycin Boosts Brain Blood Flow in Alzheimer’s Gene Carriers

Summary:

A pilot clinical trial from the University of Missouri reveals that low-dose rapamycin significantly boosts cerebral blood flow in healthy, middle-aged carriers of the APOE4 gene, the strongest genetic risk factor for late-onset Alzheimer’s disease. Female carriers demonstrated the most pronounced vascular improvements, highlighting the anti-aging compound’s potential as a targeted, precision preventative therapy years before cognitive decline begins.

Key Facts:

  • Selective Hemodynamic Boost: Following a four-week regimen of low-dose daily rapamycin, significant increases in cerebral blood flow were detected exclusively in APOE4 carriers, with no equivalent vascular shift observed in non-carrier controls.
  • Pronounced Response in Women: Female APOE4 carriers exhibited the greatest gains in cerebral perfusion—a critical outcome given that women account for nearly two-thirds of all diagnosed Alzheimer’s cases.
  • Early Preventative Window: The intervention targeted asymptomatic adults aged 45 to 65, establishing that vascular deficits associated with genetic Alzheimer’s risk can be therapeutically modified decades before clinical dementia symptoms appear.

Source: University of Missouri

The apolipoprotein E epsilon 4 (APOE4) allele stands as the most potent known genetic risk factor for developing sporadic, late-onset Alzheimer’s disease. Carrying a single copy triples the lifetime risk, while carrying two copies can increase that risk twelvefold.

Long before extracellular amyloid plaques or neurofibrillary tau tangles materialize, people carrying the APOE4 variant frequently exhibit subtle, insidious physiological defects—most notably, chronic hypoperfusion, or restricted cerebral blood flow to vital memory hubs.

Because healthy neurons depend on steady microvascular perfusion for oxygenation and metabolic clearance, this early vascular shortfall accelerates neural aging and lowers the threshold for neurodegenerative cascades.

Now, a clinical study led by investigators at the University of Missouri (Mizzou) suggests that this early circulatory breakdown is not an unchangeable fate. Published in the Journal of Cerebral Blood Flow & Metabolism, the findings demonstrate that the mTOR-inhibiting drug rapamycin can directly boost cerebral perfusion in cognitively healthy middle-aged APOE4 carriers.

From Preclinical Longevity to Human Precision Medicine

The research was spearheaded by Ai-Ling Lin, Ph.D., a professor in Mizzou’s School of Medicine and College of Arts and Science, and an investigator at the Roy Blunt NextGen Precision Health building.

Prior to joining Mizzou, Dr. Lin’s laboratory performed pioneering animal work showing that rapamycin—an FDA-approved immunosuppressant primarily prescribed to prevent organ transplant rejection and treat rare lung conditions—slows neurological aging and restores cerebral blood flow in transgenic APOE4 mice.

To determine whether these neuroprotective effects translate to human biology, Lin designed a clinical trial involving healthy adults aged 45 to 65 who were genetically screened for APOE4 status. Crucially, none of the participants exhibited clinical memory impairment or dementia symptoms.

Participants received a daily low dose of rapamycin over a four-week trial period. Neuroimaging assessments revealed a striking, genotype-dependent effect: only APOE4 carriers experienced significant gains in cerebral blood flow. Non-carriers taking the same regimen did not exhibit comparable vascular shifts, demonstrating that the drug acts directly upon the specific microvascular vulnerability induced by the variant.

“Alzheimer’s tends to happen more in older people, especially for those with APOE4,” said Dr. Lin. “If we can slow down aging in the brain for those people most at risk, maybe we can reduce the risk of them developing Alzheimer’s disease.”

High-Impact Protection for Women at Risk

The trial revealed another crucial clinical pattern: female APOE4 carriers derived the most dramatic improvements in brain blood flow.

This sexual dimorphism holds major clinical weight. Women represent nearly two-thirds of the global population living with Alzheimer’s disease, and female APOE4 carriers consistently exhibit more rapid cognitive deterioration and neurodegeneration than male counterparts with the same genotype.

“We also found that females with APOE4 saw the greatest improvement in brain blood flow, which is significant given that nearly two-thirds of people with Alzheimer’s are women,” Lin noted. “This research is an example of precision medicine, as we work to identify who can benefit from this drug the most.”

In addition to enhancing cerebral perfusion, the study examined systemic impacts across downstream metabolic, inflammatory, and gut microbiome pathways, suggesting that systemic longevity therapeutics can remodel whole-body physiology to support intracranial health.

Operating out of Mizzou’s Roy Blunt NextGen Precision Health facility, Lin and her colleagues plan to expand these preliminary findings into larger, longitudinal clinical trials. The overarching goal is to determine whether sustained, long-term restoration of cerebral blood flow through targeted anti-aging therapeutics can permanently delay, or even prevent, the clinical onset of Alzheimer’s disease in high-risk populations.

Editorial Notes:

  • This article was edited by a Neuroscience News editor.
  • Journal paper reviewed in full.
  • Additional context added by our staff.

About this Alzheimer’s and neuropharmacology Research:

  • Media Contact: Brian Consiglio
  • Source: University of Missouri-Columbia
  • Image Credit: Image credited to Neuroscience News
  • Original Research is Open Access: Journal of Cerebral Blood Flow & Metabolism (Sept 22, 2026). “Rapamycin increases cerebral blood flow and modulates metabolic, inflammatory, and microbiome profiles in healthy middle-aged APOE4 carriers: a pilot single-arm trial.” Authors: Chetan Aware, Caitlin Maria Neher, Carter Woods, Oleksandr Khegai, Alok Kumar Dwivedi, Maalavika Govindarajan, Kira Ivanich, Mehmet Kurt, David Beversdorf, Jianlin Cheng, Nathan Bresette, Taixing Cui, Priti Balchandani, Mitzi M. Gonzales, Aaron C. Ericsson, Talissa Altes, and Ai-Ling Lin.
  • DOI: 10.1177/0271678X261490342

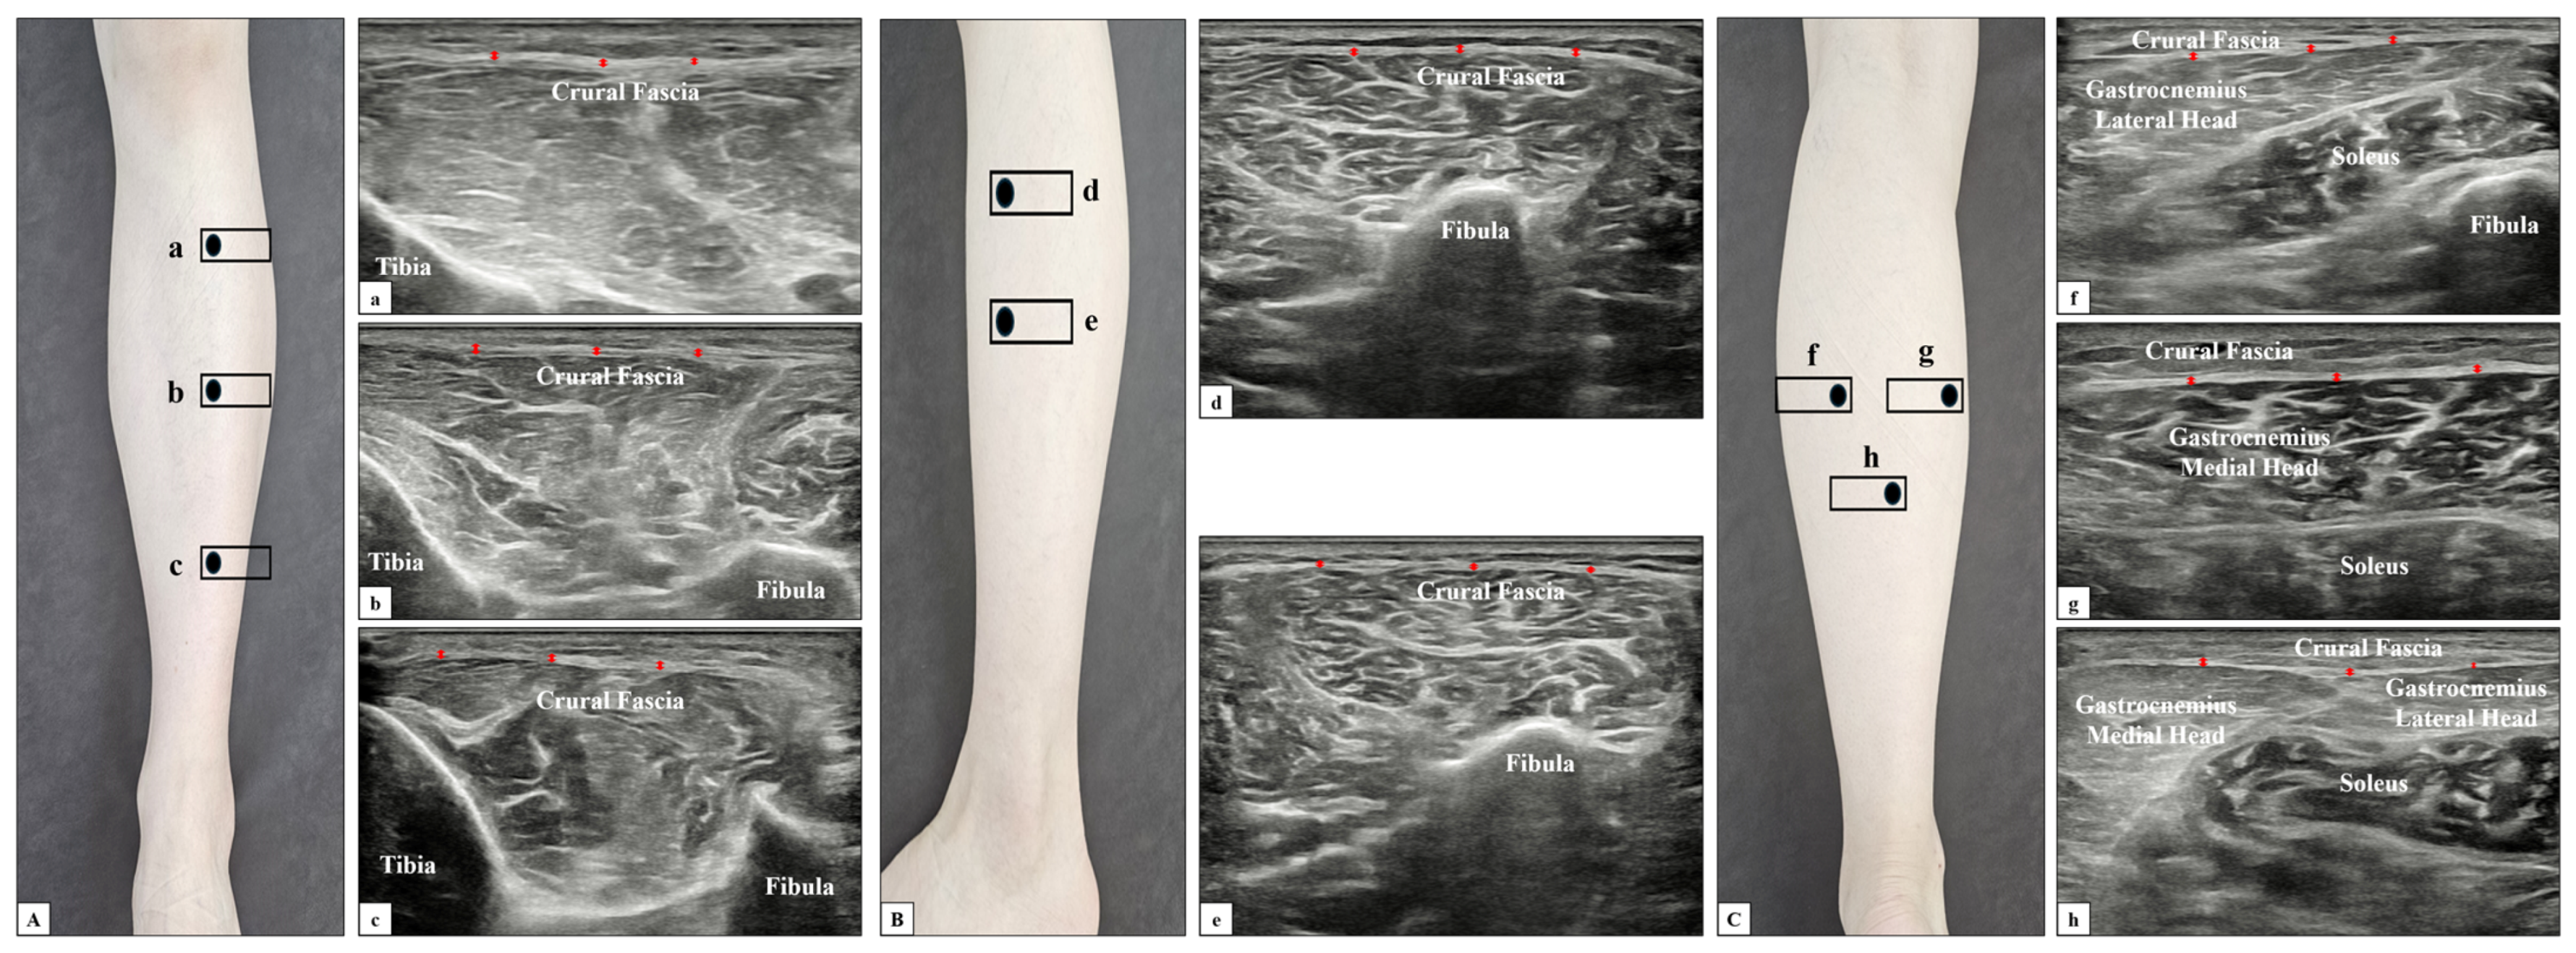
Ultrasound Imaging Comparison of Crural Fascia Thickness and Muscle Stiffness in Stroke Patients with Spasticity

 Based on this, what will your competent? doctor do to cure spasticity? 

Nothing like usual? PURE INCOMPETENCE THEN! 

A fireable offence for the past two years!

Ultrasound Imaging Comparison of Crural Fascia Thickness and Muscle Stiffness in Stroke Patients with Spasticity

                                 by 1,2, 3 and 2,4,*
1
Fascia Research Institute, Myofascial Release Korea, Seoul 06136, Republic of Korea
2
Department of Physical Therapy, The Graduate School, Gachon University, Incheon 21936, Republic of Korea
3
Department and Research Institute of Rehabilitation Medicine, College of Medicine, Yonsei University, Seoul 03722, Republic of Korea
4
Department of Physical Therapy, College of Medical Science, Gachon University, Incheon 21936, Republic of Korea
*
Author to whom correspondence should be addressed.
Diagnostics 2024, 14(22), 2606; https://doi.org/10.3390/diagnostics14222606
Submission received: 13 October 2024 / Revised: 14 November 2024 / Accepted: 17 November 2024 / Published: 20 November 2024
(This article belongs to the Special Issue Advances in Ultrasound Imaging for Musculoskeletal Diseases)

Abstract

Background/Objective: 

Spasticity following stroke causes structural changes in the muscles and fascia, affecting the mobility and functional recovery of patients. Understanding these structural changes is critical to optimizing the rehabilitation strategies for patients. Therefore, in this study, we aimed to investigate the differences in crural and epimysial fascia thickness and muscle stiffness in the affected and unaffected lower limbs of chronic stroke patients with spasticity. 

Methods: 

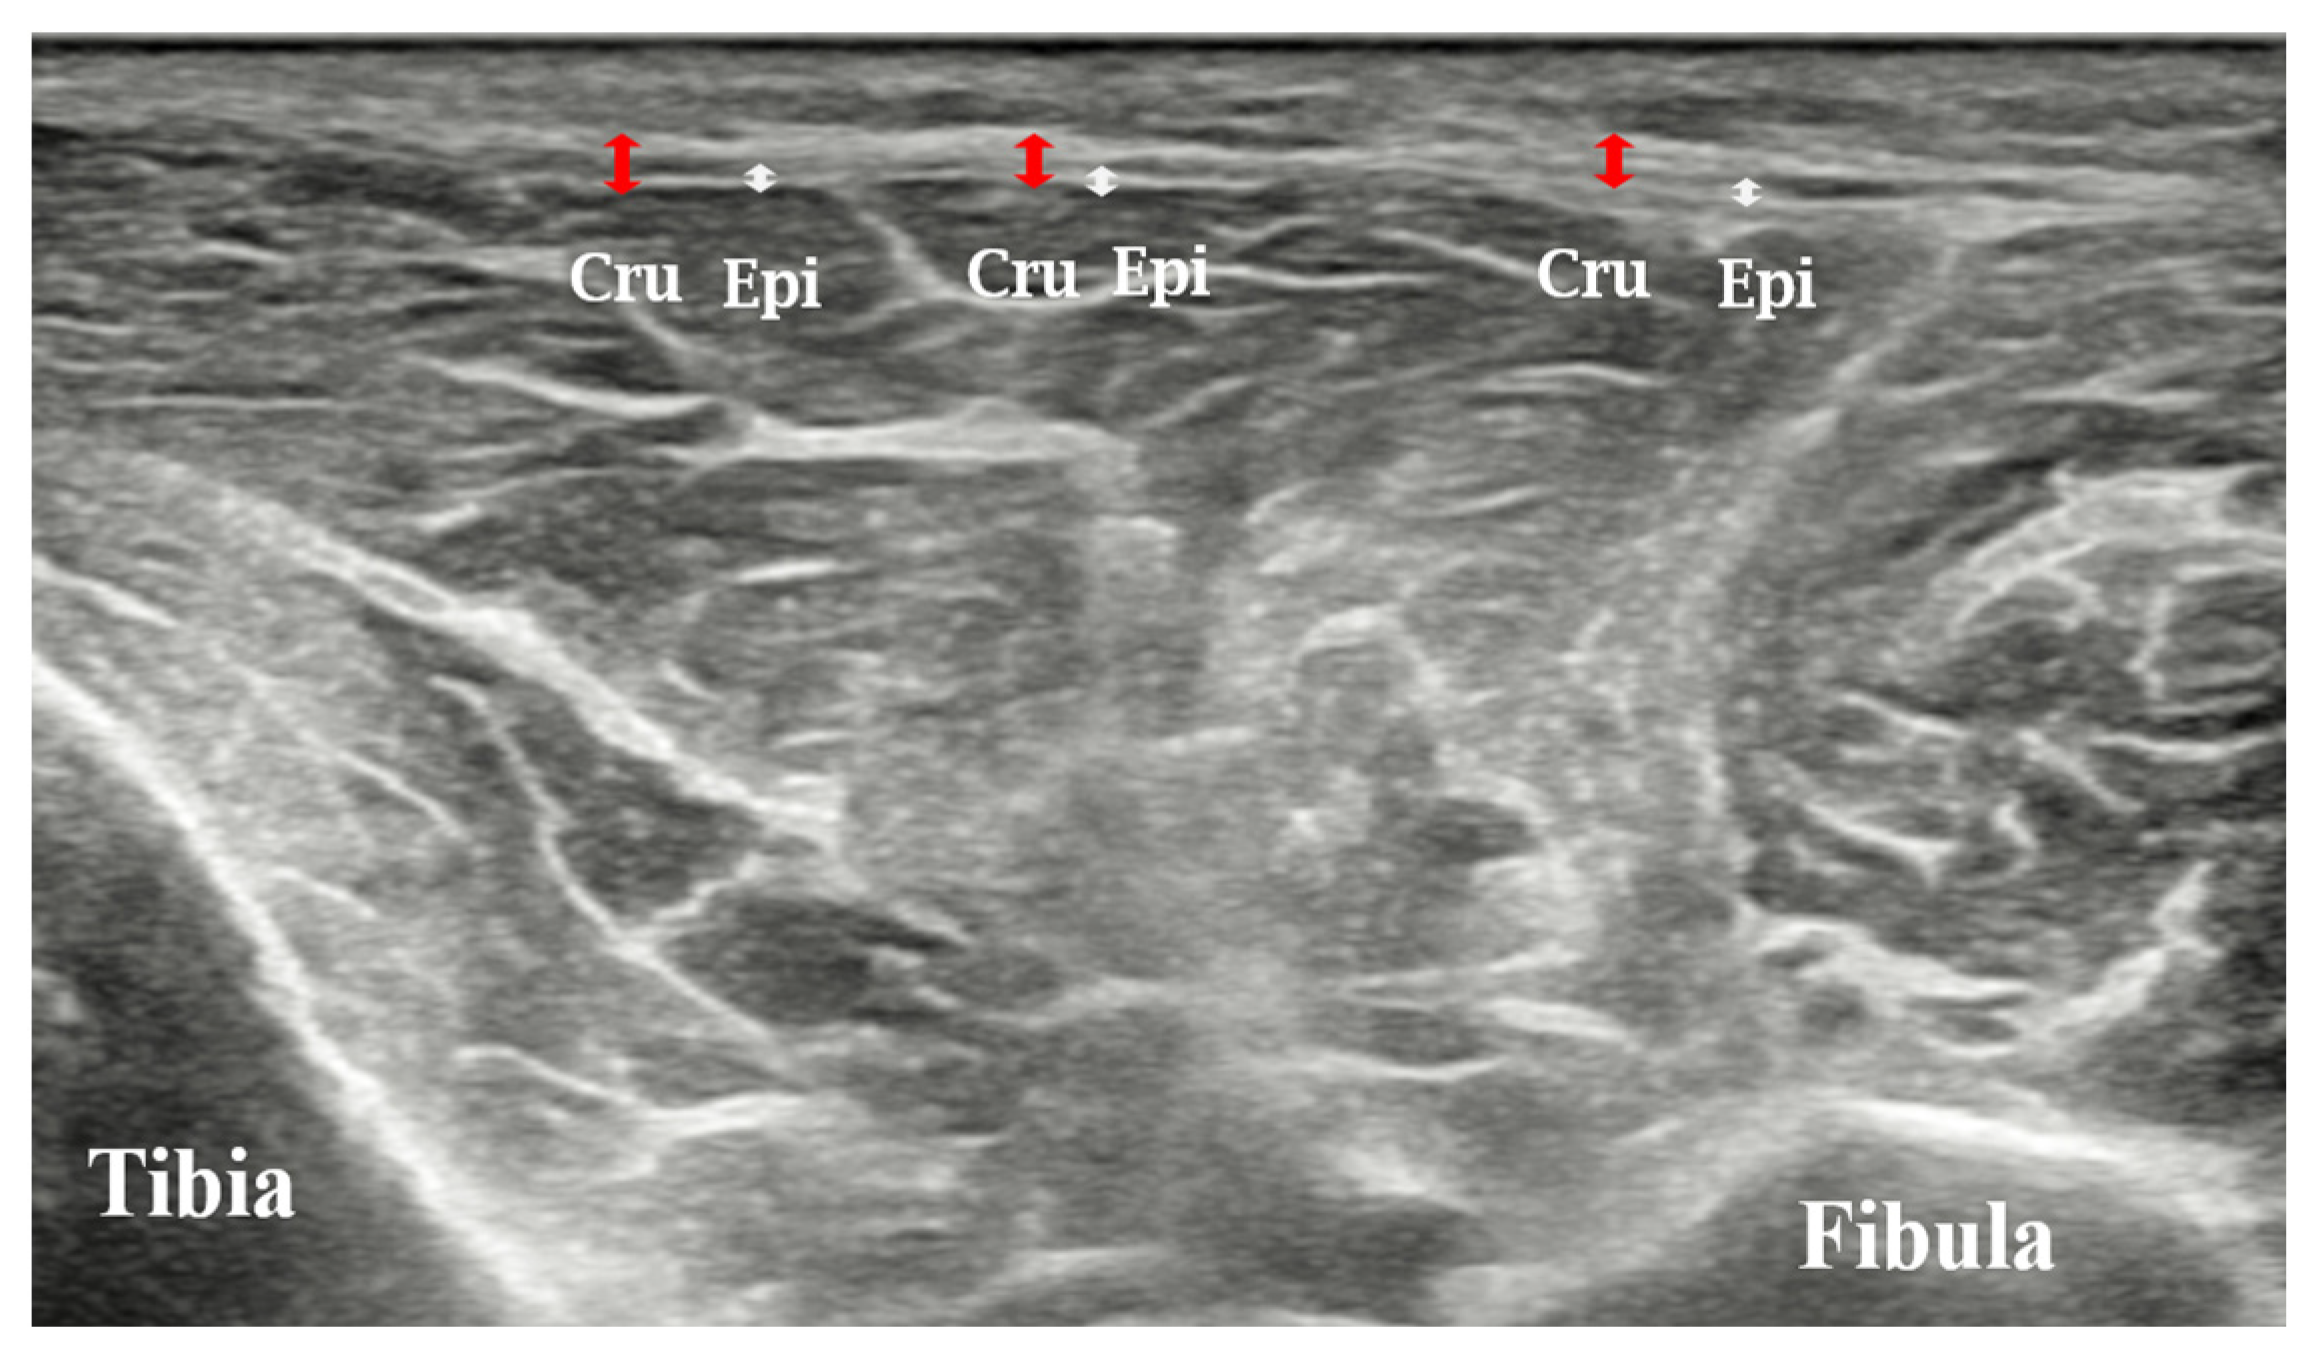
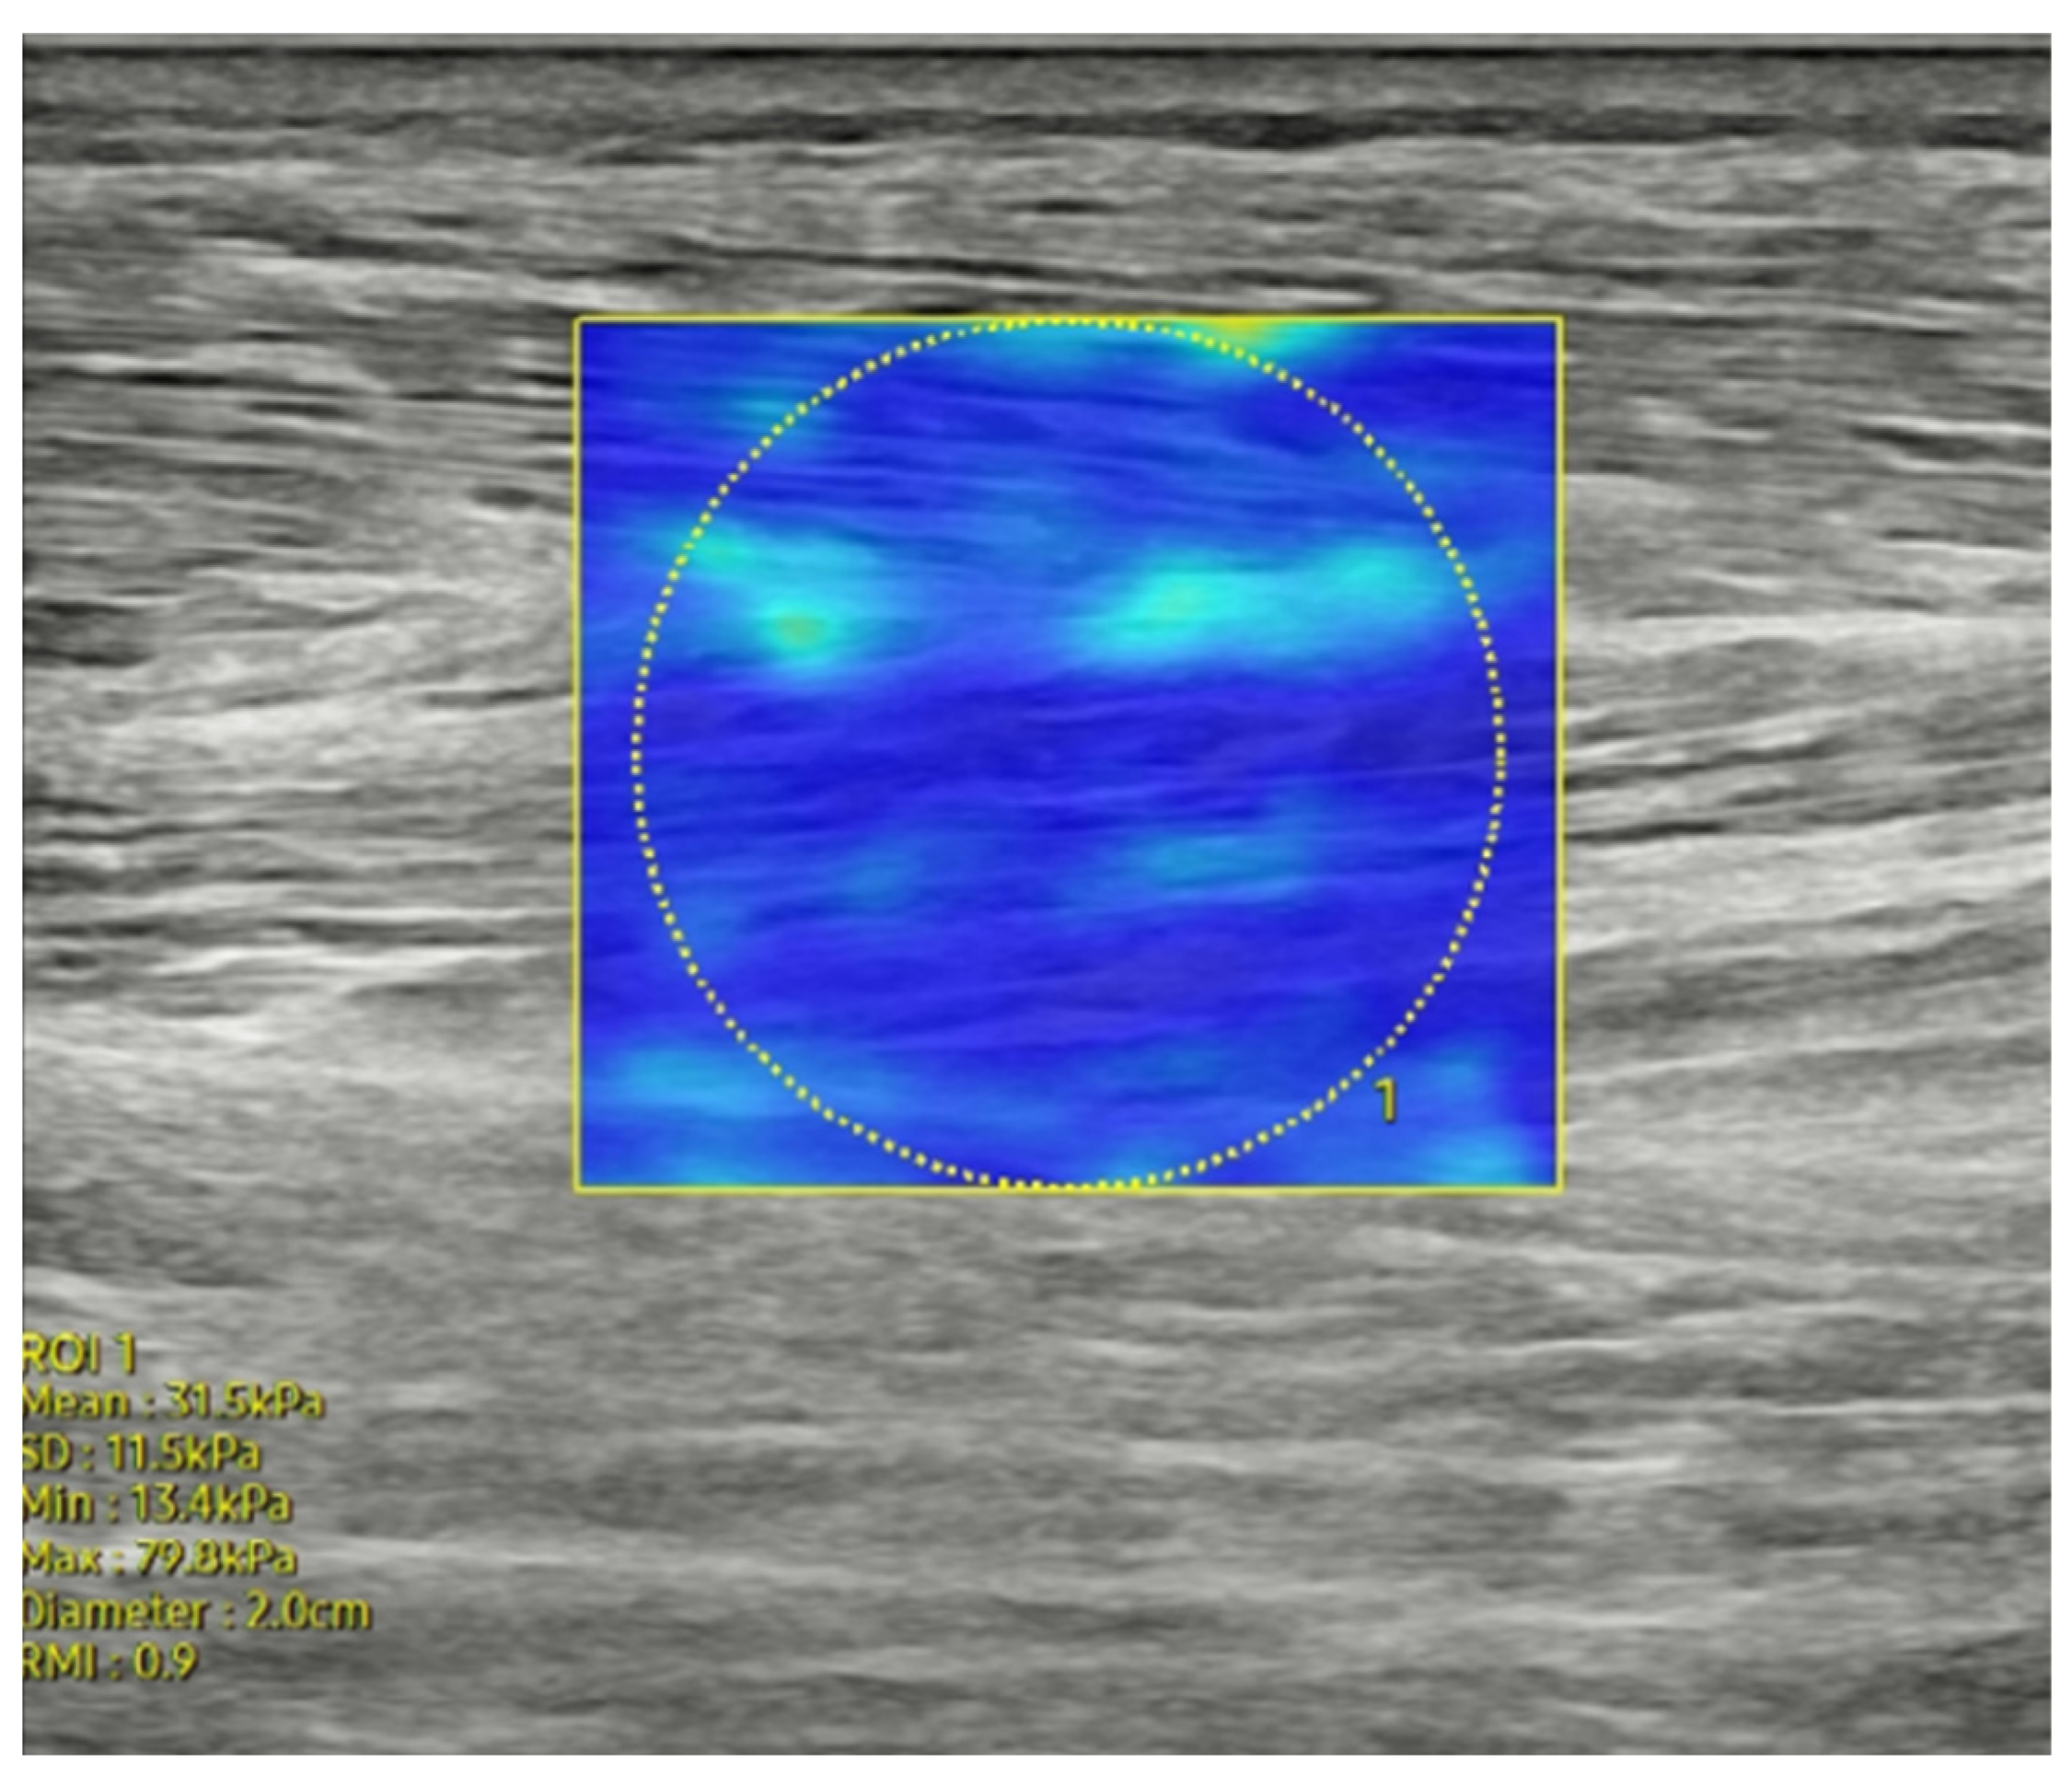
A total of 88 patients with chronic stroke (mean age: 62.7 ± 10.2 years) were included in this study. Ankle range of motion, crural fascial thickness, and muscle stiffness in affected and unaffected lower limbs were assessed using ultrasound. Results: For the affected lower limbs, 59 patients (67.1%) exhibited a modified Ashworth scale score of 2, whereas 29 patients (32.9%) exhibited a score of 3. Ankle range of motion, fascia thickness, and muscle stiffness were also measured. The range of motion in ankle dorsiflexion and plantar flexion was significantly reduced on the affected side (p < 0.05). Crural fascia thickness was significantly greater in all regions of the affected side (anterior: 0.96 ± 0.14 vs. 0.72 ± 0.08 mm [p < 0.001]; lateral: 1.01 ± 0.14 vs. 0.75 ± 0.14 mm [p < 0.001]), and the epimysial fascia of the tibialis anterior muscle was similarly greater in the affected side (0.46 ± 0.07 vs. 0.34 ± 0.03 mm [p < 0.001]). However, no significant differences in muscle stiffness were observed between the affected and unaffected sides (p > 0.05). 

Conclusions: 

Overall, these findings revealed significant fascial thickening with only minimal changes in muscle stiffness on the affected side, highlighting the importance of controlling fascial changes for post-stroke spasticity management.

The generous act that can slow brain ageing

 Did your competent? doctor get you recovered enough to help others?

Well, I'm not really a volunteer. I have much more likely things to do to prevent dementia. 

The generous act that can slow brain ageing

We all know that we could and should be doing more to help others but with busy work lives, busy home lives and attempting to make time for self-care, there often just aren’t enough hours in the day.

However, new research from the University of Texas at Austin has revealed that, well, a bit selfishly, helping others could also be the secret to helping our own long-term brain health.

This is essential as according to Alzheimer’s Research UK, 982,000 people are estimated to be living with dementia in the UK and this number is predicted to rise to 1.4 million by 2040.

Helping others could slow down brain ageing

The study, which followed more than 300,000 adults in the US over two decades found that people who consistently helped others outside of the home showed a slower rate of age-related decline. 

This decline was reduced by 15-20% among those who either volunteered formally or helped in informal ways by doing things like helping neighbours, family or friends.

Notably, the most consistent benefit was found when people spent around two to four hours per week helping others. So, even a few hours one evening or an hour here or there could make a significant difference.

Wild.

How to get started in volunteering

Reach Volunteering offers the following advice to those that have never volunteered before: “If you’ve never volunteered before, start with a time limited project, or a short-term commitment. This will give you a chance to try out volunteering and experiment with what works for you.

 Related video:  5 daily habits doctors say can help protect your brain (KHOU-TV Houston)

 “Think carefully about what you can reasonably offer. Consider how much time you can spare, whether you can travel or if remote working would be best for you, and what sort of commitment you’re willing to make. Don’t overstretch: work out what you can confidently commit to and start there – you can always build on it later.