Changing stroke rehab and research worldwide now.Time is Brain! trillions and trillions of neurons that DIE each day because there are NO effective hyperacute therapies besides tPA(only 12% effective). I have 523 posts on hyperacute therapy, enough for researchers to spend decades proving them out. These are my personal ideas and blog on stroke rehabilitation and stroke research. Do not attempt any of these without checking with your medical provider. Unless you join me in agitating, when you need these therapies they won't be there.

What this blog is for:

My blog is not to help survivors recover, it is to have the 10 million yearly stroke survivors light fires underneath their doctors, stroke hospitals and stroke researchers to get stroke solved. 100% recovery. The stroke medical world is completely failing at that goal, they don't even have it as a goal. Shortly after getting out of the hospital and getting NO information on the process or protocols of stroke rehabilitation and recovery I started searching on the internet and found that no other survivor received useful information. This is an attempt to cover all stroke rehabilitation information that should be readily available to survivors so they can talk with informed knowledge to their medical staff. It lays out what needs to be done to get stroke survivors closer to 100% recovery. It's quite disgusting that this information is not available from every stroke association and doctors group.

Showing posts with label edaravone. Show all posts

Tuesday, September 8, 2026

Adjuvant neuroprotective therapies for acute ischemic stroke in the reperfusion era: a comparative narrative review of clinical evidence for edaravone, edaravone-dexborneol, and butylphthalide


You'll have to ask your competent? doctor why the hell edaravone is approved in Japan since 2001 but not the US. If your doctor doesn't know this off the top of the head; you DON'T have a functioning stroke doctor!

Has your stroke hospital done anything with edaravone in the last decade?


Or Butylphthalide (4 posts to December 2021)

Or dexborneol (4 posts to February 2024)

The latest here:

Adjuvant neuroprotective therapies for acute ischemic stroke in the reperfusion era: a comparative narrative review of clinical evidence for edaravone, edaravone-dexborneol, and butylphthalide


  • 1. Department of Neurology, First People's Hospital of Jiande City, Hangzhou, Zhejiang, China

  • 2. Department of Scientific Research, First People's Hospital of Jiande City, Hangzhou, Zhejiang, China

Abstract

Reperfusion therapies, including intravenous thrombolysis and endovascular treatment (EVT), are central to acute ischemic stroke (AIS) management; however, ischemia–reperfusion injury may limit recovery despite successful recanalization. This structured narrative review compares the clinical evidence, safety signals, and mechanistic literature for edaravone, butylphthalide (NBP), and the fixed-dose combination edaravone-dexborneol (EDB) as adjunctive neuroprotective approaches. The evidence base is heterogeneous with respect to population, background reperfusion treatment, outcome timing, and geographical setting. In TASTE-2, EDB administered before EVT was associated with a modest increase in 90-day functional independence versus placebo (55.0% vs. 49.6%, p = 0.05), without an apparent safety signal; bridging alteplase was permitted in a subset of participants. In the BAST trial, NBP improved the prespecified 90-day functional outcome versus placebo among patients receiving intravenous thrombolysis and/or EVT (56.7% vs. 44.0%). Observational studies and meta-analyses provide supportive but non-confirmatory evidence for edaravone. Network meta-analyses generate relative rankings at individual endpoints, but indirect comparisons and differing outcome networks preclude definitive between-agent selection. Mechanistic studies indicate overlapping antioxidant, anti-inflammatory, mitochondrial, and neurovascular effects rather than exclusive pathway regulation. Biomarker and imaging approaches, including exploratory GFAP and UCH-L1 measurements, are promising research tools but are not yet validated for treatment selection in AIS. Accordingly, these agents should be regarded as candidates for further evidence-informed adjunctive use; future trials are needed to define reproducible patient-selection and treatment-timing strategies.

Monday, October 6, 2025

Efficacy and safety of edaravone dexborneol in acute ischemic stroke: systematic review and meta-analysis

You'll have to ask your competent? doctor why the hell edaravone is approved in Japan since 2001 but not the US. If your doctor doesn't know this off the top of the head; you DON'T have a functioning stroke doctor!

Has your stroke hospital done anything with edaravone in the last decade?


edaravone (20 posts to November 2011)

The latest here:

 Efficacy and safety of edaravone dexborneol in acute ischemic stroke: systematic review and meta-analysis


Khaled Moghib,Khaled Moghib1,2Mahmoud Tarek HefnawyMahmoud Tarek Hefnawy3Shehab M. MoawadShehab M. Moawad1Izere Salomon
&#x;Izere Salomon4*Ahmed HamdiAhmed Hamdi1Olivier UwishemaOlivier Uwishema5Mostafa MeshrefMostafa Meshref6
  • 1Faculty of Medicine, Kasr Al-Ainy Cairo University, Cairo, Egypt
  • 2Medical Research Group of Egypt, Negida Academy, Arlington, MA, United States
  • 3Faculty of Medicine, Zagazig University, Zagazig, Egypt
  • 4University of Rwanda College of Medicine and Health Sciences, Kigali, Rwanda
  • 5Department of Research and Education, Oli Health Magazine Organization, Kigali, Rwanda
  • 6Department of Neurology, Faculty of Medicine, Al-Azhar University, Cairo, Egypt

Background: Edaravone dexborneol represents a novel neuroprotective agent utilized in the treatment of acute ischemic stroke (AIS). Preliminary studies indicate that this combination exhibits enhanced therapeutic effects when compared to the use of edaravone alone. The objective of this study was to assess the efficacy and safety of edaravone dexborneol in the management of AIS.

Method: This systematic review and meta-analysis were conducted following the Preferred Reporting Items for Systematic Reviews and Meta-analyses (PRISMA) statement guidelines. A comprehensive search of the PubMed, Cochrane Central, Scopus, and Web of Science databases was performed on December 30, 2024. Subsequently, we screened articles for eligibility, relevant data were extracted, and the risk of bias was assessed utilizing the Cochrane Collaboration Tool 2. The primary outcome evaluated was the efficacy of edaravone dexborneol in the management of AIS, as measured by the National Institutes of Health Stroke Scale (NIHSS) and the modified Rankin Scale (mRS). Secondary outcomes encompassed improvements in activities of daily living (ADL), reductions in post-stroke depression, inflammation, and hemorrhagic transformation, as well as enhancements in cognitive function, as indicated by Montreal Cognitive Assessment (MoCA) scores. Extracted data from pertinent Randomized Controlled Trials (RCTs) were analyzed using R programming for Windows. All procedures outlined in this study were pre-specified, and the protocol has been registered with PROSPERO under the unique identifier CRD42024626320.

Results: A total of six randomized controlled trials (RCTs) and one cohort study, all conducted in China and involving 2,942 patients with ischemic stroke (65.6% male), were included. Treatment regimens consisted of intravenous or sublingual edaravone dexborneol administered for 10–14 days. The pooled analysis of functional outcomes at 90 days, based on five studies, demonstrated a significant benefit, with a 39.5% higher likelihood of achieving favorable mRS scores (OR = 1.40, 95% CI: 1.18–1.65, p = 0.0001), without evidence of heterogeneity (I2 = 0%). In contrast, pooled analysis of NIHSS outcomes across seven studies using a random-effects model was not significant (SMD = −0.113, 95% CI: −0.333 to 0.107, p = 0.314), with substantial heterogeneity (I2 = 72.7%). However, under the common-effect model, a small but statistically significant benefit was observed (SMD = −0.083, 95% CI: −0.159 to −0.008, p = 0.030). Sensitivity analyses indicated that several studies (Fu 2024, Hu 2023, Xu 2019, Xu 2024) attenuated the pooled effect, while exclusion of Li 2024 and Hu 2023 reduced heterogeneity to 40.7% but resulted in only borderline significance. Secondary endpoints consistently demonstrated favorable effects, including improved activities of daily living, enhanced cognitive function (MoCA scores), and reduced rates of post-stroke depression, inflammation, and hemorrhagic transformation. Safety analyses revealed that adverse events were generally mild and comparable to controls, with some evidence suggesting a reduction in serious complications such as hemorrhagic transformation.

Conclusion: Edaravone dexborneol exhibits considerable potential as a neuroprotective agent in the context of AIS, providing both functional and cognitive advantages, alongside a favorable safety profile. The promising efficacy of this compound underscores the necessity for further comprehensive global studies aimed at optimizing its application and enhancing its relevance across diverse populations.

Systematic review registration: https://www.crd.york.ac.uk/prospero/, identifier CRD42024626320.

Monday, September 1, 2025

Clinical efficacy of edaravone dexborneol in the treatment of acute ischemic stroke: meta-analysis

You'll have to ask your competent? doctor why the hell edaravone is approved in Japan since 2001 but not the US. If your doctor doesn't know this off the top of the head; you DON'T have a functioning stroke doctor!

Has your stroke hospital done anything with edaravone in the last decade?


edaravone (12 posts to November 2011)

The latest here:

 Clinical efficacy of edaravone dexborneol in the treatment of acute ischemic stroke: meta-analysis


Haobo Gao&#x;Haobo GaoHongtu Tan&#x;Hongtu TanJiabin WangJiabin WangDongyi YangDongyi YangYangyang LiuYangyang LiuTao Wu
Tao Wu*
  • Department of Intervention, The First Affiliated Hospital of Henan University of Chinese Medicine, Zhengzhou, China

Background: In China, edaravone dexborneol (ED) is often used to treat acute ischemic stroke (AIS), but internationally, ED is not commonly used. This study aimed to conduct a meta-analysis on the application of ED in AIS, so as to provide reference and guidance for clinical use in the future.

Methods: Pubmed and Web of Science databases were searched for articles on ED in the treatment of AIS. Two researchers independently searched the articles based on pre-specified inclusion (randomized controlled trial, complete data, correct logic, English literature, etc.) and exclusion criteria (studies lacking objective reference standards, studies with follow-up success rates below 80%, etc.), and duplicate articles were excluded using Endnote. The search was set for the build time to December 2024. Then, the initially enrolled articles were subjected to information and data extraction and crosschecking, followed by meta analysis using the RevMan 5.3 software after screening. Primary outcome measures included clinical efficacy, safety, and NIHSS.

Results: A total of 5 articles were included after screening, totaling 2,651 study participants. Subjects in the 5 articles were divided into an experimental group (ED treatment, n = 1,465) and a control group (other treatment regimen(s), n = 1,226). All the articles were of high quality and high reference value. According to Meta-analysis, no statistically significant difference was observed in the incidence of adverse reactions between the ED and control groups (95%CI = 0.67 ~ 1.04, p = 0.11), but the clinical efficacy in the experimental group exhibited significantly better outcomes compared to the control group (95%CI = 0.03 ~ 0.09, p = 0.0002). In addition, NIHSS (95%CI = −4.67 ~ −0.13, p = 0.04) and hs-CRP (95%CI = −1.90 ~ −0.23, p = 0.01) were lower in the experimental group than in the control group. Funnel plots were drawn for outcome measures with heterogeneity. The results showed that the funnel plot of the NIHSS scores and hs-CRP were basically symmetrical.

Conclusion: While ED demonstrates short-term efficacy in improving neurological outcomes, its clinical applicability remains uncertain due to unresolved questions about drug diffusion and delivery in human brain tissue, which may fundamentally limit its long-term benefits.

Wednesday, December 4, 2024

China NMPA approves Simcere’s Sanbexin® sublingual tablets for the treatment of Acute Ischemic Stroke


You'll have to ask your competent? doctor why the hell edaravone is approved in Japan since 2001 but not the US.

Has your stroke hospital done anything with edaravone in the last decade?


The latest here:

China NMPA approves Simcere’s Sanbexin® sublingual tablets for the treatment of Acute Ischemic Stroke

NANJING, China, Dec. 4, 2024 /PRNewswire/ -- On November 2, 2024, Simcere Pharmaceutical announced that Sanbexin® sublingual tablets (generic name: edaravone and dexborneol sublingual tablets), an innovative drug for stroke, has been approved for marketing by the National Medical Products Administration. This product is indicated for the improvement of neurological symptoms, daily activities, and functional impairment due to acute ischemic stroke.

Sanbexin® sublingual tablets is a dual-target brain cytoprotective agent composed of edaravone and dexborneol. These two active ingredients exert synergistic anti-oxidant and anti-inflammatory effects, which can significantly reduce brain cell damage caused by acute ischemic stroke.

The sublingual tablets are designed for quick disintegration once in contact with saliva under the tongue. This facilitates the active ingredients’ rapid absorption into the blood and brain through the sublingual venous plexus. Compared to conventional oral formulations, sublingual tablets bypass the first-pass hepatic metabolism, which is conducive to higher drug bioavailability and faster onset of action.

Packaging of Sanbexin® sublingual tablets

Previously, Sanbexin® injection was approved for marketing in China in 2020. As the world’s only innovative drug approved for stroke since 2015, it has helped over 3 million patients in the past 4 years.

The phase III clinical trial led by Professor Fan Dongsheng of Peking University Third Hospital showed that the patients in the Sanbexin® sublingual tablets group after 14 consecutive days of drug administration, obtained a significantly higher proportion of functional independence outcome at 90 days post-treatment than those in the placebo group (64.4% vs. 54.7%,). The latest data was published in JAMA Neurology on February 19, 2024.

Professor Fan Dongsheng, Principal Investigator of TASTE-SL and Professor at Peking University Third Hospital mentioned:“Sanbexin® sublingual tablets has shown significant effects and good safety in improving recovery of cerebral cells and independent living ability during the acute phase in patients with acute ischemic stroke. The more convenient administration allows for sequential therapy with Sanbexin® injection, facilitating stroke patients to receive a complete course of brain cytoprotection in and outside of the hospital during the acute phase of stroke.”

Professor Wang Yongjun, Director of Beijing Tiantan Hospital, Capital Medical University “The average length of hospital stay for stroke patients in China is about one week, while clinical studies suggest that brain cytoprotective drugs need to be used for 14 consecutive days. Sanbexin® sublingual tablets is easy to take, allowing patients to receive treatment at home. This can better reduce disability among patients and is also expected to lower medical costs.”

In August 2024, Sanbexin® sublingual tablets was granted Breakthrough Therapy Designation by the U.S. Food and Drug Administration (FDA) for AIS, making it the world’s first innovative drug in the field of stroke treatment to have received such acknowledgment. Currently, a global multi-centered clinical trial of Sanbexin® sublingual tablets is under preparation.

“The approval of Sanbexin® sublingual tablets in China is believed to significantly reduce the number of stroke-related disabilities in China.”

Professor Gregory W. Albers, Director of the Stroke Center and the Medical Center at Stanford University commented, ” We are planning to conduct a large-scale Phase III clinical trial of Sanbexin® sublingual tablets in the United States, hoping to replicate the success of the trial in China and help reduce the global burden of stroke-related disabilities.”

Dr. Marc Fisher, former President of the World Stroke Organization and Professor at Harvard Medical School, commented on this new approval:“Sanbexin® has gradually gained popularity in China and is now available in a sublingual tablets formulation, with clinical data confirming its safety and efficacy. We are hoping to see trials of Sanbexin® sublingual tablets conducted outside China. If the trial results are positive and it receives approval in other countries, such as the U.S., it will have a huge impact globally on the treatment of acute ischemic stroke.”

The Sanbexin® sublingual tablets, with its convenient delivery method, will make stroke prevention and treatment more comprehensive and accessible. Its therapeutic area is expected to be expanded to pre-hospital emergency treatment for the acute phase of stroke, as well as to the treatment for the sub-acute and chronic phases of cerebrovascular diseases, to further promote the recovery of neurological functions and to improve the functional prognosis of stroke patients.

Cision View original content to download multimedia:https://www.prnewswire.com/news-releases/china-nmpa-approves-simceres-sanbexin-sublingual-tablets-for-the-treatment-of-acute-ischemic-stroke-302322300.html

SOURCE Simcere Pharmaceutical Group Limited

Tuesday, December 3, 2024

Synergistic effects of neuroprotective drugs with intravenous recombinant tissue plasminogen activator in acute ischemic stroke: A Bayesian network meta-analysis

Where is the protocol for this located so stroke survivors can inform their stroke medcal 'professionals' about using this?  Oh, you didn't create one, did you? YOU'RE FIRED!

You'll have to ask your competent? doctor why the hell edaravone is approved in Japan since 2001 but not the US.

Has your stroke hospital done anything with edaravone in the last decade?


The latest here:

 Synergistic effects of neuroprotective drugs with intravenous recombinant tissue
plasminogen activator in acute ischemic stroke: A Bayesian network meta-analysis

RESEARCH ARTICLE
Synergistic effects of neuroprotective drugs
with intravenous recombinant tissue
plasminogen activator in acute ischemic
stroke: A Bayesian network meta-analysis
Chun DangID1, Qinxuan Wang2, Yijia Zhuang2, Qian Li3, Yaoheng LuID4*,
Ying XiongID1*, Li Feng5*
1 Department of Periodical Press/Chinese Evidence-Based Medicine Center, West China Hospital, Sichuan
University, Chengdu, China, 2 West China Hospital, West China School of Medicine, Sichuan University,
Chengdu, China, 3 Department of Neurology, The Second Affiliated Hospital of Harbin Medical University,
Harbin, China, 4 Department of General Surgery, Chengdu Integrated Traditional Chinese Medicine and
Western Medicine Hospital, Chengdu, China, 5 Department of General Surgery and Regenerative Medicine
Research Center, West China Hospital, Sichuan University, Chengdu, China
These authors contributed equally to this work.
* fengli@scu.edu.cn (LF); 61711445@qq.com (YX); lyh93@cdutcm.edu.cn (YL)

Abstract

Neuroprotective drugs as adjunctive therapy for adults with acute ischemic stroke (AIS)
remains contentious. This study summarizes the latest evidence regarding the benefits of
neuroprotective agents combined with intravenous recombinant tissue plasminogen activa-
tor (rt-PA) intravenous thrombolysis. This study conducted a structured search of PubMed,
the Cochrane Library, EMBASE, Wanfang Data, and CNKI databases from their inception
to March 2024. Grey literature was also searched. The outcomes included efficacy (National
Institutes of Health Stroke Scale (NIHSS) score and Barthel Index (BI) score) and safety
(rate of adverse reactions). A total of 70 randomized controlled trials were selected for this
network meta-analysis (NMA), encompassing 4,140 patients with AIS treated using different
neuroprotective agents plus RT-PA, while 4,012 patients with AIS were in control groups.
The top three treatments for NIHSS scores at the 2-week follow-up were Edaravone Dex-
borneo with 0.9 mg/kg rt-PA, Edaravone with 0.9 mg/kg rt-PA, and HUK with 0.9 mg/kg rt-
PA. HUK with 0.9 mg/kg rt-PA, Dl-3n-butylphthalide with 0.9 mg/kg rt-PA, and Edaravone
Dexborneo with 0.9 mg/kg rt-PA were ranked the top three for BI scores at the 2-week fol-
low-up. The top three treatments with the lowest adverse effect rates were 0.6 mg/kg rt-PA,
HUK with 0.9 mg/kg rt-PA, and Edaravone Dexborneo with 0.9 mg/kg rt-PA due to their
excellent safety profiles. Compared to rt-PA alone, the combination treatments of Edara-
vone+rt-PA, Edaravone Dexborneol+rt-PA, HUK+rt-PA, Dl-3n-butylphthalide+rt-PA, and
Ganglioside GM1+rt-PA have shown superior efficacy. This NMA suggest that combination
therapies of neuroprotective agents and rt-PA can offer better outcomes for patients with
AIS. The results support the potential integration of these combination therapies into stan-
dard AIS treatment, aiming for improved patient outcomes and personalized therapeutic
approaches.

Monday, December 2, 2024

Drug Combo Tied to Functional Improvement After Stroke

 Ask your competent doctor to evaluate this previous trial to this new one.

FYI, make sure you read the caveats.

Sublingual Acute Stroke Neuroprotectant Dazzles in Phase III Trial

You'll have to ask your competent? doctor why the hell edaravone is approved in Japan since 2001 but not the US.

Has your stroke hospital done anything with edaravone in the last decade?


The latest here:

Drug Combo Tied to Functional Improvement After Stroke

Abu Dhabi, UAE — In the latest multicenter randomized trial testing a combination of edaravone and dexborneol for the treatment of acute stroke, the proportion of patients with complete or near complete function at 90 days was improved significantly relative to placebo. 

The third in a series, this trial, like the previous two, showed that participants who received the experimental treatment “were more likely to achieve functional independence at 90 days without increased safety concerns,” said study investigator Chun-Juan Wang, MD, PhD, Department of Neurology, Beijing Tiantan Hospital, Capital Medical University, Beijing, China.

The results of TASTE-2 were presented in a late-breaking session on October 24 at the 16th World Stroke Congress (WSC) 2024

Data From Three Key Trials

For the study, 1362 patients were randomly assigned to receive edaravone dexborneol or placebo within 24 hours of an acute stroke at 106 participating centers. The primary outcome assessed at 90 days was functional independence as defined by a modified Rankin Scale (mRS) score of 0 to 2.

Unlike in the previous two trials, all patients underwent endovascular thrombectomy (EVT). All three multicenter studies were conducted in China.

The primary endpoint was reached by 55.0% of participants in active treatment arm vs 49.6% of those in the placebo group, producing a 24% improvement in the odds ratio (OR) of achieving a functional recovery (OR, 1.24; P < .047). 

Edaravone, which is an antioxidant but might have other neuroprotective activity, is currently approved for the treatment of amyotrophic lateral sclerosis. Borneol, the active ingredient of dexborneol, has been shown to downregulate anti-inflammatory factors in the experimental setting and might also have other neuroprotective properties. 

The combination of these active drugs in a single infusion was first evaluated in the TASTE-1 trial, which was published in 2021. In that phase 3 double-blind study, 1165 acute stroke patients were randomly assigned to receive edaravone dexborneol or edaravone alone within 48 hours of an acute stroke. The primary endpoint of mRS score ≤ 1 was achieved by 67.18% of those in the combination therapy arm vs 58.9% of those receiving dexborneol alone (OR, 1.42; P < .001). 

A second large randomized trial, called TASTE-SL, was published in JAMA Neurology earlier this year. In this multicenter study, 914 acute stroke patients were assigned in a 1:1 fashion to sublingual edaravone dexborneol or matching placebo within 48 hours of symptom onset. The primary endpoint of mRS score ≤ 1 was achieved by 64.4% of those assigned to receive the combination therapy vs 54.7% of those receiving placebo (OR, 1.50; P = .003). 

TASTE-1 enrolled acute stroke patients with a median baseline National Institutes of Health Stroke Scale (NIHSS) score of 6. They did not receive reperfusion therapy. TASTE-SL enrolled patients with a median NIHSS score of 7 who did not undergo EVT. In TASTE-2, the median NIHSS score was 15, and EVT was an inclusion criterion.

When patients were stratified by specific functional mRS scores, there was a numerically higher proportion of patients achieving mRS score of 0 (22.1% vs 20.9%) and 1 (18.1% vs 17.4%) but the greatest between-group difference was seen for an mRS score of 2 (14.8% vs 11.3%). 

The advantage of edaravone dexborneol moved in the same direction across almost all subgroups evaluated. There were trends for greater benefit among those treated within 6 hours relative to later and in those who had hypertension, coronary artery disease, or a high NIHSS score (≥ 15) relative to those who did not.

The proportion of patients with adverse events (33.0% vs 32.3%) or serious adverse events (27.2% vs 25.7%) was slightly higher in the active treatment arm, but none of these adverse events were considered to be treatment related. 

The proportion of patients with intracranial hemorrhage within 36 hours was numerically lower in the active treatment arm (5.3% vs 6.5%). The all-cause mortality at 90 days was the same in both groups (16.5%). 

The effect size of edaravone dexborneol was smaller than that anticipated in the design of the trial, but Chun-Juan Wang, who presented these data along with the senior investigator, Yongjun Wang, MD, chief physician at her institution, said that the positive results from three randomized trials are mutually reinforcing. Conducted in a population with a higher NIHSS score, TASTE-2 supports broader application.

On the basis of these data, “edaravone dexborneol may serve as a concomitant agent with EVT or with intravenous thrombolysis,” Chun-Juan Wang said.

Additional Therapeutic Evidence 

By itself, edaravone has demonstrated a therapeutic effect in acute stroke in numerous trials, according to Mariana Fidalgo, MD, Centro Hospitalar de Vila Nova de Gaia/Espinho, Vila Nova De Gaia, Portugal. In a systemic review and meta-analysis that she published 2 years ago, based on 19 randomized controlled trials, the likelihood of a good (OR, 1.31; 95% CI, 1.06-1.67) or excellent (OR, 1.26, 95% CI, 1.04-1.54) outcome at 90 days was increased significantly.

“Edaravone was also associated with a lower risk of death compared to placebo or no therapy,” Fidalgo said, noting that these studies, like the TASTE trials, did not associate edaravone with an increased risk for intracranial hemorrhage or other serious adverse events.

Despite these data, edaravone with or without dexborneol has not received regulatory approval for the treatment of acute stroke, but Fidalgo, who was not involved in the TASTE trials, called an edaravone-based therapy given shortly after the onset of stroke “promising” for increasing the odds of functional recovery.

Marc Fisher, MD, professor of neurology at Beth Israel Deaconess Medical Center, Harvard Medical School, Boston, noted that edaravone dexborneol has now demonstrated a statistically significant benefit for acute stroke in three large blinded multicenter trials. 

Fisher, who was the senior author on a review article published 2 years ago that suggested cytoprotective therapies are showing promise as adjuncts to acute stroke reperfusion therapies, acknowledged that the relative benefit of edaravone dexborneol has been modest across the three trials in which it was studied, but these data are “clinically meaningful for a drug that is safe.”

The study received funding from Simcere Pharmaceutical Group Limited. Chun-Juan Wang, Yongjun Wang, and Fidalgo report no relevant financial relationships. Fisher reports that he has been a consultant for Simcere.

Friday, March 8, 2024

Update on Antioxidant Therapy with Edaravone: Expanding Applications in Neurodegenerative Diseases


You'll have to ask your competent? doctor why the hell edaravone is approved in Japan since 2001 but not the US.

Has your stroke hospital done anything with edaravone in the last decade?


Update on Antioxidant Therapy with Edaravone: Expanding Applications in Neurodegenerative Diseases

by 1 and 2,*
1
Department of Neurology, Okayama University Graduate School of Medicine, Dentistry and Pharmaceutical Sciences, 2-5-1 Shikata-cho, Okayama 700-8558, Japan
2
Department of Neurology, National Center of Neurology and Psychiatry, Tokyo 187-8551, Japan
*
Author to whom correspondence should be addressed.
Int. J. Mol. Sci. 2024, 25(5), 2945; https://doi.org/10.3390/ijms25052945
Submission received: 26 January 2024 / Revised: 19 February 2024 / Accepted: 29 February 2024 / Published: 3 March 2024
(This article belongs to the Special Issue Antioxidants in Health and Diseases)

Abstract

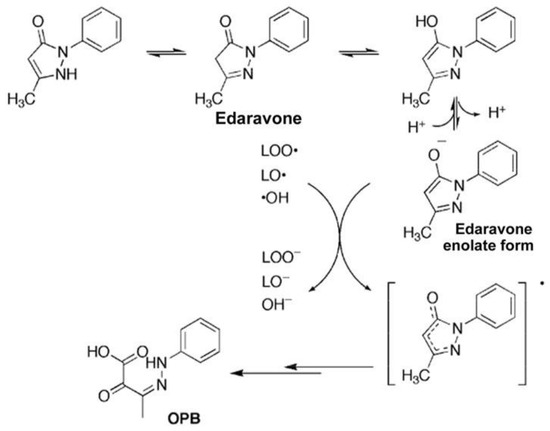
The brain is susceptible to oxidative stress, which is associated with various neurological diseases. Edaravone (MCI-186, 3-methyl-1 pheny-2-pyrazolin-5-one), a free radical scavenger, has promising effects by quenching hydroxyl radicals (∙OH) and inhibiting both ∙OH-dependent and ∙OH-independent lipid peroxidation. Edaravone was initially developed in Japan as a neuroprotective agent for acute cerebral infarction and was later applied clinically to treat amyotrophic lateral sclerosis (ALS), a neurodegenerative disease. There is accumulating evidence for the therapeutic effects of edaravone in a wide range of diseases related to oxidative stress, including ischemic stroke, ALS, Alzheimer’s disease, and placental ischemia. These neuroprotective effects have expanded the potential applications of edaravone. Data from experimental animal models support its safety for long-term use, implying broader applications in various neurodegenerative diseases. In this review, we explain the unique characteristics of edaravone, summarize recent findings for specific diseases, and discuss its prospects for future therapeutic applications.

1. Introduction

The brain, which is rich in lipids and exhibits high oxygen consumption, is susceptible to damage via oxidative stress. Briefly, oxidative stress is caused by an imbalance between the production and accumulation of reactive oxygen species (ROS) in cells and tissues and the ability of a biological system to detoxify these reactive products [1]. ROS contribute to several physiological processes (e.g., cell signaling) [2] and are generated as byproducts of oxygen metabolism under normal conditions. Nevertheless, environmental stressors and xenobiotics can contribute to a significant increase in ROS production, resulting in cellular and tissue damage. Oxidative stress has been implicated in neurodegenerative diseases, including amyotrophic lateral sclerosis (ALS), Parkinson’s disease, Alzheimer’s disease (AD), Huntington’s disease, depression, and multiple sclerosis. Furthermore, it plays an important role in the pathogenesis of acute ischemic stroke [3,4]. Free radical formation and subsequent oxidative damage may be a factor in stroke severity [5]. Therefore, several antioxidants with demonstrated or predicted beneficial effects against oxidative stress and stroke have recently been reported [6,7,8,9].
Edaravone (MCI-186, 3-methyl-1 pheny-2-pyrazolin-5-one) was first established in Japan as a free radical scavenger (Figure 1). It was initially approved for the treatment of acute ischemic stroke in Japan, where it is manufactured under the brand name Radicut. It has been used in clinical practice for the treatment of acute cerebral ischemia and ALS owing to its antioxidative and anti-inflammatory effects. Edaravone has also been approved for use in Japan, South Korea, and the United States for the treatment of ALS. It has been approved in the United States under the brand name Radicava by the U.S. Food and Drug Administration (FDA).
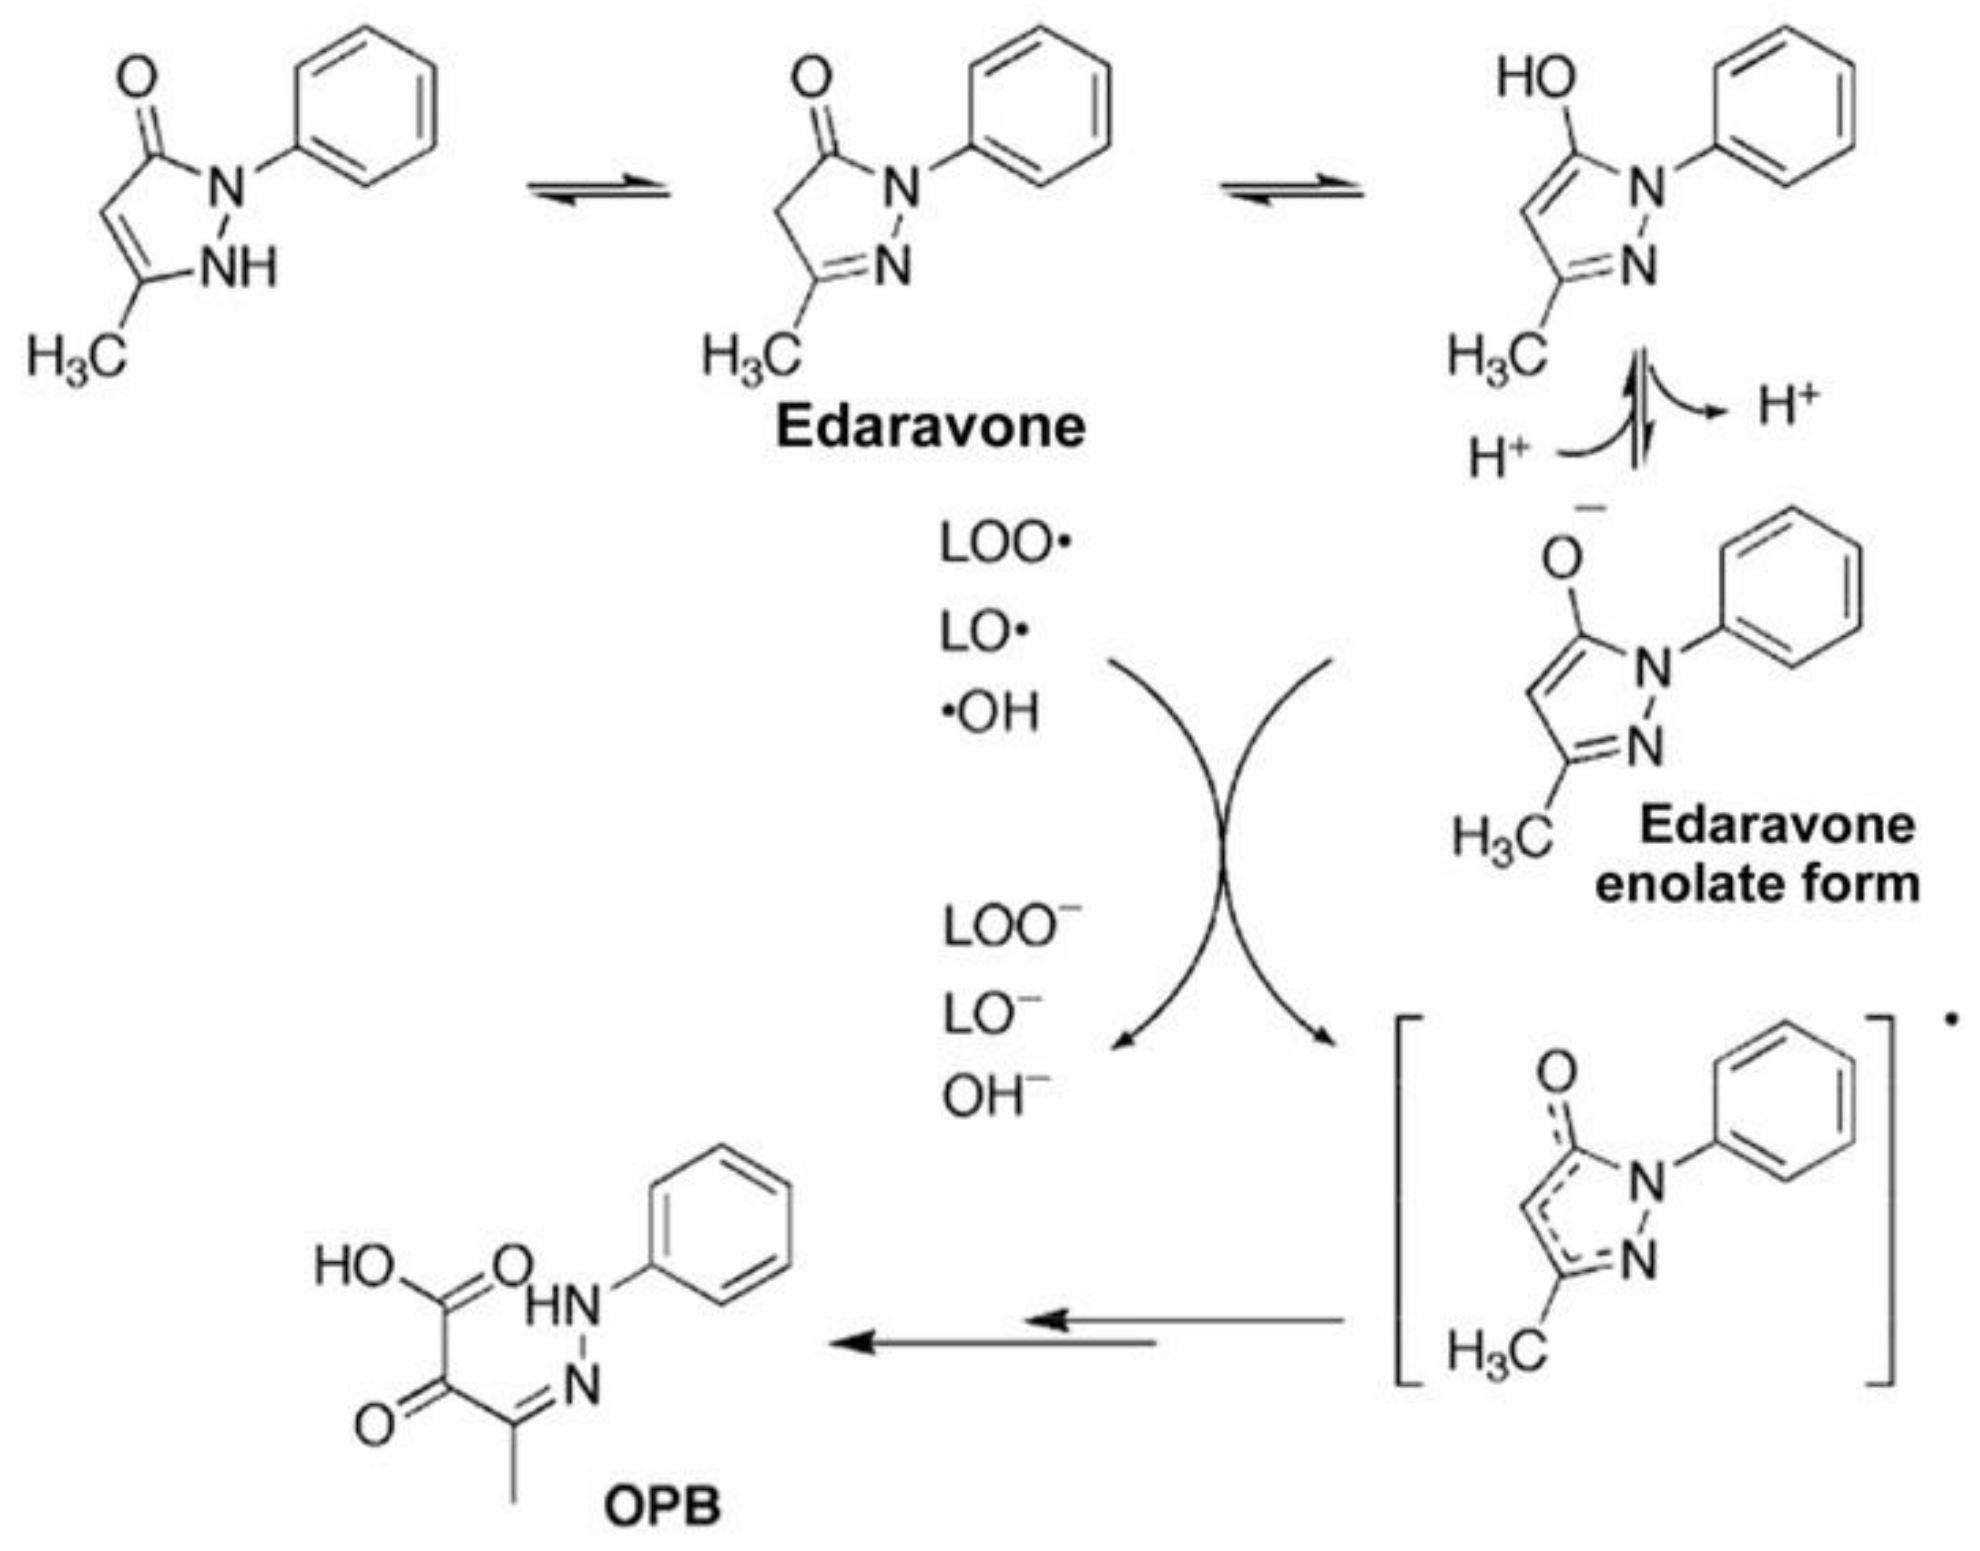
Figure 1. Reaction mechanism of edaravone with free radicals (revised from Nakagawa et al. 2006 [10]). The enolate form of edaravone interacts with both peroxyl radicals (LOO·) and hydroxy radicals (·OH) to form stable oxidation products (2-oxo-3-(phenylhydrazono)-butanoic acid; OPB).
In this study, using PubMed, we searched the literature for studies related to edaravone for a comprehensive review of its development and applications to various diseases. We introduce the unique characteristics of edaravone, summarize recent findings for various diseases (Table 1 and Table 2), and discuss prospects for future therapeutic applications.

Wednesday, February 21, 2024

Sublingual Acute Stroke Neuroprotectant Dazzles in Phase III Trial

 FYI, make sure you read the caveats.

Sublingual Acute Stroke Neuroprotectant Dazzles in Phase III Trial

Experts raise concerns about analysis and reporting in Chinese study

 A computer rendering of a brain with a dark spot on the side

For acute ischemic stroke within 48 hours of onset, the novel sublingual combination of edaravone (Radicava) with dexborneol appeared to dramatically improve functional outcomes in the phase III TASTE-SL trial from China.

The chance of a good functional outcome as marked by a modified Rankin Scale (mRS) score of 0-1 on day 90 was 50% improved with the neuroprotectant compared with placebo (64.4% vs 54.7%, OR 1.50, 95% CI 1.15-1.95, P=0.003), reported Dongsheng Fan, MD, of Peking University Third Hospital in Beijing, and colleagues in JAMA Neurologyopens in a new tab or window.

Adverse events (AEs) occurred in most patients in both groups; serious AEs were uncommon and balanced between the two.

"This is a remarkable result, and given that edaravone dexborneol is low cost, simple to administer (even in patients who are unconscious, disabled, or dysphagic), and readily available in China, it has major potential practice implications," said Craig S. Anderson, PhD, and Lili Song, MD, PhD, both of the George Institute for Global Health in Sydney.

In an accompanying editorial, they acknowledged the "litany of failed neuroprotection trials in acute ischemic stroke" over after several decades of considerable investment but noted a "clear rationale" for adjuvant stroke treatment in the endovascular treatment era.

"Many patients have poor access to reperfusion therapy and, even when they do have it, do not have a satisfactory recovery despite achieving a good technical result of recanalization of an occluded vessel. Moreover, in showing the benefits of endovascular therapy within a 6- to 24-hour onset-to-treatment time window in patients with a large ischemic lesion, recent trials have also challenged understanding about how viable vs dead neuronal tissue is defined on brain imaging," they wrote.

Edaravone is a low-molecular-weight drug that appears to protect neurons, glia, and vascular endothelial cells against oxidative stress and inflammation. It is FDA approved for amyotrophic lateral sclerosis. The combination with dexborneol, a component of proprietary Chinese medicine, "is believed to offer a synergistic action," the editorialists noted.

However, they pointed out some serious concerns with the results: "To begin with, the size of the observed treatment effect ... is much higher than would be expected of a neuroprotective agent. Because approximately half of the patients commenced the treatment at 24 hours or longer after symptom onset, this size of benefit is equivalent to that seen with intravenous thrombolysis initiated within the first few hours of an acute ischemic stroke. Therefore, the results challenge our understanding of the 'time is brain' concept of the evolving ischemic penumbra and are contrary to the neutral results of the ESCAPE-NA1 trial, and most recently ESCAPE-NEXT ... which evaluated nerinetide, a highly promising drug that attenuates excitotoxic cell death."

The editorialists suggested chance could be at play in TASTE-SL, which was powered at 80% rather than a more conventional 90% and did not show benefits of edaravone dexborneol in any secondary endpoints, including early neurological impairment in NIH Stroke Scale (NIHSS) scores between baseline and 14 and 30 days.

"It is unfortunate that no ancillary measures of health-related quality of life were collected during follow-up to allow a broader appraisal of the recovery of patients," Anderson and Song lamented.

The researchers, though, chalked the nonsignificant secondary endpoint results up to the substantial number of mild strokes in the trial, with an average NIHSS score of 7.

The trial included 914 patients, ages 18-80 years, who had an NIHSS score of 6-20; a total motor deficit score of the upper and lower limbs of 2 or greater; clinically diagnosed acute ischemic stroke symptoms within 48 hours; and a pre-stroke mRS score of 1 or less.

They were randomly assigned to sublingual edaravone dexborneol (30 and 6 mg, respectively) or placebo comprised of inert dexborneol (60 μg, to simulate the taste of the active drug) twice daily for 14 days.

Limitations included exclusion of a patient who got endovascular thrombectomy and enrollment of only persons of Chinese ethnicity.

The editorialists also pointed to another limitation: "Just before being unblinded to the data toward the end of the study, the steering committee made the decision to use a complex approach to addressing missing primary outcome data in the primary analysis rather than a more conventional complete case analysis of the primary outcome. This included using the last observation carried forward or assigning a worse-case variable (6 for death) in patients with a missing outcome. Given that missingness (loss to follow-up) is invariably not lost at random, this could have influenced the result. Inevitably, this did not occur as they were readily confirmed in secondary imputation, covariate-adjusted, and subsequent complete case analyses."

They also raised the specter of conflicts of interest, as the study authors included employees of three pharmaceutical companies, "including the one that sponsored the study and would naturally have an interest in the trial outcome."

Furthermore, Anderson and Song added to the call for replication of the results in other regions of the world.

"Because maximizing access to reperfusion treatment is at the forefront of modern stroke services, and disease and social reasons for delayed presentation after symptom onset differ across regions, the TASTE-SL results are promising but less relevant to contemporary clinical practice outside of China," they wrote. "However, they provide a clear justification for further evaluations of edaravone dexborneol in other populations, and for individual patient data meta-analysis to be undertaken to determine the totality of the evidence."

"The performance bar is set high, but the benefits offered by safe treatments with only modest effects in reducing the burden of acute ischemic stroke worldwide are considerable," Anderson and Song stated.

Disclosures

The trial was sponsored and funded by grants from Simcere Pharmaceutical and the National Key R&D Program of China.

Fan dislcosed no relationships with industry. Four co-authors are employees of Simcere Pharmaceutical Group. Two co-authors are employees of Neurodawn Pharmaceutical.

Anderson disclosed being principal investigator for the INTERACT3 trial, which was funded by research grants from the Medical Research Council of the U.K., Takeda China, and Hasten Pharma, and receiving fellowship grant support from the National Health and Medical Research Council of Australia.

Song disclosed no relationships with industry.

Primary Source

JAMA Neurology

Source Reference: Fu Y, et al "Sublingual edaravone dexborneol for the treatment of acute ischemic stroke: The TASTE-SL randomized clinical trial" JAMA Neurol 2024; DOI: 10.1001/jamaneurol.2023.5716.

Secondary Source

JAMA Neurology

Source Reference: Anderson CS and Song L "Promising efforts to define a novel approach to neuroprotection for acute ischemic stroke" JAMA Neurol 2024; DOI: 10.1001/jamaneurol.2023.5727.