Changing stroke rehab and research worldwide now.Time is Brain! trillions and trillions of neurons that DIE each day because there are NO effective hyperacute therapies besides tPA(only 12% effective). I have 523 posts on hyperacute therapy, enough for researchers to spend decades proving them out. These are my personal ideas and blog on stroke rehabilitation and stroke research. Do not attempt any of these without checking with your medical provider. Unless you join me in agitating, when you need these therapies they won't be there.

What this blog is for:

My blog is not to help survivors recover, it is to have the 10 million yearly stroke survivors light fires underneath their doctors, stroke hospitals and stroke researchers to get stroke solved. 100% recovery. The stroke medical world is completely failing at that goal, they don't even have it as a goal. Shortly after getting out of the hospital and getting NO information on the process or protocols of stroke rehabilitation and recovery I started searching on the internet and found that no other survivor received useful information. This is an attempt to cover all stroke rehabilitation information that should be readily available to survivors so they can talk with informed knowledge to their medical staff. It lays out what needs to be done to get stroke survivors closer to 100% recovery. It's quite disgusting that this information is not available from every stroke association and doctors group.

Showing posts with label research analysis employee. Show all posts

Tuesday, February 7, 2023

Scientific statement provides guidance on staffing, resource requirements for stroke centers

And I bet there is nothing in there that requires a full time research analyst whose only job is to evaluate stroke research and implement new and updated protocols based on that research. In other words a person who keeps the whole hospital up-to-date.

Scientific statement provides guidance on staffing, resource requirements for stroke centers

Statement Highlights:

  • A new American Heart Association statement suggests guidance for workforce and operations needs for hospital stroke centers in the U.S.
  • The statement proposes stroke center certification requirements that will help reduce variability across hospital stroke programs and encourage quality improvement efforts to better support communities and care for patients with stroke.

Embargoed until 4 a.m. CT/5 a.m. ET Tuesday, Feb. 7, 2023

DALLAS, February 7, 2023 — A new American Heart Association scientific statement provides guidance on staffing, leadership and resource requirements for hospital stroke centers to reduce variability and improve quality of care at stroke centers across the U.S. The new statement is published today in the American Heart Association’s peer-reviewed journal, Stroke, and will be presented at 2:00 p.m. CT tomorrow, Wednesday, Feb. 8, 2023, in an Invited Symposium Session, “Cerebrovascular Nursing,” at the International Stroke Conference 2023 in Dallas.

Stroke centers are certified by several different agencies at four levels: acute stroke–ready hospitals, primary stroke centers (PSCs), thrombectomy-capable stroke centers (TSCs) and comprehensive stroke centers (CSCs). Since certification began in the U.S. in 2003, there have been considerable advancements in diagnostic, prevention and treatment strategies that have increased demand for stroke center recognition via certification.

While certification requirements and some state agencies provide general standards and designate scope of practice dependent on the level of stroke services, there is a lack of detail regarding important structural components for stroke centers. Differences in these areas mean that stroke centers credentialed at the same level may function very differently.

The statement should be viewed as a call to action that proposes ideal foundational requirements for stroke centers that may help minimize inconsistencies and improve the services provided by certified stroke centers at all levels. These include suggestions for stroke program leadership, personnel resources, neuroimaging capabilities, procedural capabilities, hospital bed resources, quality improvement and clinical research, and stroke system accountability. Guidance is based on the level of certification. For example, while performance improvement plans are suggested for all four levels of stroke centers, clinical stroke research is recommended as a foundational requirement only for TSCs and CSCs. Also, a dedicated stroke unit is required for all but the acute-stroke ready level of certification, and a neurocritical care unit is required for a comprehensive stroke center.

This scientific statement, “Ideal Foundational Requirements for Stroke Program Development and Growth,” was prepared by the volunteer writing group on behalf of the American Heart Association’s Council on Cardiovascular and Stroke Nursing and the Stroke Council. American Heart Association scientific statements promote greater awareness about cardiovascular diseases and stroke issues and help facilitate informed health care decisions. Scientific statements outline what is currently known about a topic and what areas need additional research. While scientific statements inform the development of guidelines, they do not make treatment recommendations. American Heart Association guidelines provide the Association’s official clinical practice recommendations. 

Co-authors are Chair Wendy Dusenbury, Ph.D., D.N.P., FAHA; Vice-Chair Claranne Mathiesen, M.S.N., FAHA; Michelle Whaley, M.S.N.; Opeolu Adeoye, M.D., M.S., FAHA; Thabele Leslie-Mazwi, M.D.; Shavonne Williams, M.N.; Cesar Velasco, B.S.N.; Samarth Shah, Pharm.D.; Nicole Gonzales, M.D.; and Anne W. Alexandrov, Ph.D. Authors’ disclosures are listed in the manuscript.

The Association receives funding primarily from individuals. Foundations and corporations (including pharmaceutical, device manufacturers and other companies) also make donations and fund specific Association programs and events. The Association has strict policies to prevent these relationships from influencing the science content. Revenues from pharmaceutical and biotech companies, device manufacturers and health insurance providers, and the Association’s overall financial information are available here. 

Additional Resources:

About the American Heart Association

The American Heart Association is a relentless force for a world of longer, healthier lives. We are dedicated to ensuring equitable health in all communities. Through collaboration with numerous organizations, and powered by millions of volunteers, we fund innovative research, advocate for the public's health and share lifesaving resources. The Dallas-based organization has been a leading source of health information for nearly a century. Connect with us on heart.org, Facebook, Twitter or by calling 1-800-AHA-USA1.  

###

For Media Inquiries and AHA/ASA Expert Perspective: 214-706-1173

Maggie Francis: 214-706-1382; Maggie.Francis@heart.org

For Public Inquiries: 1-800-AHA-USA1 (242-8721)

Friday, October 7, 2022

First Adaptive Hemorrhagic Stroke Trial Completes Enrollment

 Does your hospital have someone assigned to follow this and create protocols from it if successful? If not, you don't have a functioning stroke hospital. How did they ever get past bloodletting as a stroke intervention if they don't have such a person?

We may as well go back to blood letting as a stroke prescription as discussed in the 1843 book, 'An Essay On The Nature and Treatment of Apoplexy'.

First Adaptive Hemorrhagic Stroke Trial Completes Enrollment

Trial sponsor, NICO Corporation, hopes to show functional recovery for the most deadly, costly stroke

INDIANAPOLIS, Oct. 6, 2022 /PRNewswire/ -- NICO Corporation announced today that enrollment is now complete for the ENRICH (Early MiNimally-invasive Removal of ICH) randomized controlled trial. The trial compares medical and economic outcomes between early surgical intervention of intracerebral hemorrhage (ICH) with minimally invasive parafascicular surgery (MIPS) to current guideline-directed medical management. ENRICH is the first ICH trial using the natural folds of the brain (trans-sulcal) to access and surgically address hemorrhages within 24 hours of onset. It is also the first trial to adaptively enroll patients based on ICH location to maximize the likelihood of patient benefit.

(PRNewsfoto/NICO Corporation)

ENRICH is the first ICH trial using natural folds of brain to access & surgically address hemorrhages within 24 hrs.

ENRICH utilizes a MIPS approach that uniquely integrates advanced imaging technologies with the NICO BrainPath® for non-disruptive navigable access using a parafascicular route to the ICH and the automated Myriad® to pursue the goal of maximum clot evacuation. The goal of the trans-sulcal MIPS approach is to allow surgeons to access and remove the hemorrhage more quickly – providing an opportunity for improved recovery.

"Historically, supratentorial intracerebral hemorrhage is a disease where all earlier surgical trials have failed to meet their primary endpoints, these studies, however, paved the way for future successes by providing specific metrics needed to impact functional outcomes," said Dr. Gustavo Pradilla of Emory University, co-principal investigator of the ENRICH trial.

Intracerebral hemorrhage, or hemorrhagic stroke, is the deadliest, most costly, and most debilitating form of stroke. As many as half of ICH patients die within 30 days, and there is no current proven therapy to treat the disease. ICH costs the U.S. more than $12 billion annually. More than 120,000 people are diagnosed with an ICH annually in the U.S. and 2.1 million people worldwide. The incidence of ICH is expected to rise due to the aging population and increased use of anticoagulants.

The ENRICH multi-center trial is led by the Emory Stroke Center of Emory University hospitals and Marcus Stroke & Neuroscience Center of Grady Memorial Hospital in Atlanta. The trial leverages multi-disciplinary teams, including stroke neurology, neurosurgery, and neuro-critical care at 33 sites that include major medical and academic centers, as well as large community hospitals. NICO has invested $10 million and more than five years in the trial, initiated in January 2017. Results are expected to be announced in Q1 2023 after the final 180-day patient follow-up period concludes.

In May, the American Heart Association-American Stroke Association announced changes to the stroke guidelines to include minimally invasive surgery approaches like MIPS when treating ICH. "We are thrilled that ENRICH is now fully enrolled and want to express our sincere gratitude to all patients and healthcare providers involved in this groundbreaking adaptive trial," said Jim Pearson, president and CEO of NICO Corporation, sponsor of the ENRICH trial. "We are hopeful the trial results will reinforce the recent changes to ICH guidelines and further define the role of MIPS in treating patients who suffer from ICH."

NICO currently holds over 250 issued or pending patents, with 60 focusing solely on safe and repeatable non-disruptive trans-sulcal access through eloquent areas of the brain with BrainPath. NICO's patents also cover efficient removal of clots formed by brain bleeds down a small corridor using the automated Myriad. It is the first and only company in the world to develop and patent technologies to create an entirely new minimally invasive surgical market in neurosurgery for subcortical and skull base lesions, including ICH. Its technologies have been featured in more than 180 peer-reviewed published papers with over 550 unique authors from major academic centers. For more information, visit NICOneuro.com, and follow the latest news on LinkedIn and Twitter.

For more information about the ENRICH trial or patient selection criteria, visit ClinicalTrials.gov or EnrichTrial.com.

Contact: Sue Goin
sue.goin@sapphire-com.com
317.402.869

Cision
Cision

View original content to download multimedia:https://www.prnewswire.com/news-releases/first-adaptive-hemorrhagic-stroke-trial-completes-enrollment-301643074.html


Sunday, July 24, 2022

Researchers study wearable technology as part of national stroke recovery clinical trial

WHOM at your hospital is tasked with evaluating this research fir possibly bringing it into the hospital for use?  NO ONE?  Then you don't have a functioning stroke hospital.

Researchers study wearable technology as part of national stroke recovery clinical trial

KU Medical Center experts are testing the effectiveness of a wearable device at reducing disability after stroke

Image of older man in wheelchair exercising with help from a physical therapist
KU Medical Center is participating in the EMAGINE study, a multisite national clincial trial that's studying if stimulating neurons in the brain while performing therapeutic exercise improves recovery after moderately severe ischemic stroke.

A clinical trial at the University of Kansas Medical Center is testing whether a wearable device that stimulates the brain and spinal cord with electromagnetic energy might one day help decrease disability after a stroke.

As part of the EMAGINE™ clinical trial, researchers are investigating if stimulating neurons in the brain while performing therapeutic exercise improves recovery after moderately severe ischemic stroke. KU Medical Center is one of 20 sites nationally expected to participate in this randomized, double-blind study that pairs frequency-tuned electromagnetic field therapy with therapeutic exercise.

Frequency-tuned electromagnetic field therapy delivers a low level of electromagnetic stimulation to the brain and spinal cord through a portable wearable device that fits over the head and torso. The trial is studying the effectiveness of the noninvasive wearable device at reducing disability after stroke and helping stroke survivors recover function of their upper and lower body extremities. It is funded by BrainQ, the technology company that developed the investigational device which received FDA Breakthrough Device Designation.

“There’s a theoretical window after stroke when the brain is plastic, or it can change, grow and recover, and we know from other research that the window is a great opportunity for rehabilitation,” said Sarah Eickmeyer, M.D., associate professor of physical medicine and rehabilitation at KU Medical Center and site co-primary investigator. “With this study, we’re hoping to accelerate that neuroplasticity with the electromagnetic stimulation.”

Eligible study participants will be issued either an investigational device or a placebo device (known as a sham device) between four and 21 days after a stroke. The device is designed to allow participants to perform therapy whether in the hospital, in a rehabilitation facility, or at home with the assistance of a trained caregiver, joined periodically by a member of the study team through a remote platform. While receiving poststroke standard of care including physical therapy and occupational therapy, participants will wear the device as they perform intensive exercise five times a week over nine weeks for a total of 45 sessions. Each exercise session will last 60 minutes.

KU plans to enroll up to 12 participants in the study. Eligible participants will be identified through The University of Kansas Health System, which partners with KU Medical Center and provides patient care. 

A unique study

Beyond testing the novel approach to stroke recovery, Sandra Billinger, Ph.D., professor and vice chair for stroke translational research in the Department of Neurology and the site co-primary investigator, called the EMAGINE™ study unique because it follows participants through a range of transitions of care.

“In this study, we’re starting the therapy while participants are still hospitalized in the acute phase, then to inpatient stroke rehabilitation and extending it through nine weeks post-stroke while at home. We hope we find that it optimizes recovery, reduces disability and eventually gives us a better map for stroke rehabilitation and recovery in the future,” Billinger said.

The other unusual aspect of the study, Eickmeyer said, is its recognition that stroke recovery and rehabilitation takes time.

“I think this study is so unique because it acknowledges this is a process that takes weeks, not days, and provides continuity of care across the spectrum, which is what people need and what we struggle to provide in our society’s fragmented healthcare system,” she said. “This study could point us toward a model of what stroke recovery should look like in the future, where it continues for months because that’s when the brain recovers and that’s how long the brain needs stimulation and exercise.” 

Advancing stroke research

According to the U.S. Centers for Disease Control, in addition to being a leading cause of death in the United States, stroke is a leading cause of long-term disability and reduced mobility in more than half of survivors 65 and over. These stark facts highlight the importance of stroke recovery studies like the EMAGINE™ trial.

“There is a recognition that advances in stroke recovery are the next frontier in stroke research. This is where we really need to be, and KU Medical Center has an opportunity to be a part of that,” Billinger said. “We’re proud to partner with The University of Kansas Health System to provide elite patient care and bring truly groundbreaking research opportunities to people after stroke in the Kansas City area.”

Friday, November 26, 2021

Harnessing Neuroplasticity to Promote Brain Health in Aging Adults: Protocol for the MOVE-Cog Intervention Study

 Since your hospital doesn't have a research analyst the results of this study will never get distributed to doctors and then down to patients. So useless research since nothing will occur because of it.

Harnessing Neuroplasticity to Promote Brain Health in Aging Adults: Protocol for the MOVE-Cog Intervention Study

Background:  

Extensive evidence supports a link between aerobic exercise and cognitive improvements in aging adults. A major limitation with existing research is the high variability in cognitive response to exercise. Our incomplete understanding of the mechanisms that influence this variability and the low adherence to exercise are critical knowledge gaps and major barriers for the systematic implementation of exercise for promoting cognitive health in aging.

Objective:  

We aimed to provide an in-person and remotely delivered intervention study protocol with the main goal of informing the knowledge gap on the mechanistic action of exercise on the brain by characterizing important mechanisms of neuroplasticity, cardiorespiratory fitness response, and genetics proposed to underlie cognitive response to exercise.

Methods:  

This is an open-label, 2-month, interventional study protocol in neurologically healthy sedentary adults. This study was delivered fully in-person and in remote options. Participants underwent a total of 30 sessions, including the screening session, 3 pretest (baseline) assessments, 24 moderate-to-vigorous aerobic exercise sessions, and 3 posttest assessments. We recruited participants aged 55 years and above, sedentary, and cognitively healthy. Primary outcomes were neuroplasticity, cognitive function, and cardiorespiratory fitness. Secondary outcomes included genetic factors, endothelium function, functional mobility and postural control, exercise questionnaires, depression, and sleep. We also explored study feasibility, exercise adherence, technology adaptability, and compliance of both in-person and remote protocols.

Results:  

The recruitment phase and data collection of this study have concluded. Results are expected to be published by the end of 2021 or in early 2022.

Conclusions:  

The data generated in these studies will introduce tangible parameters to guide the development of personalized exercise prescription models for maximal cognitive benefit in aging adults. Successful completion of the specific aims will enable researchers to acquire the appropriate expertise to design and conduct studies by testing personalized exercise interventions in person and remotely delivered, likely to be more effective at promoting cognitive health in aging adults.

Trial Registration: ClinicalTrials.gov NCT03804528; http://clinicaltrials.gov/ct2/show/NCT03804528

International Registered Report Identifier (IRRID): RR1-10.2196/33589

JMIR Res Protoc 2021;10(11):e33589

doi:10.2196/33589
 

Monday, November 15, 2021

Reprogramming brain cells to restore vision after a stroke

You might want this for your next stroke but if your hospital has no research analyst whose only job is to follow stroke research and get it implemented in the hospital, then you will be completely screwed. Your doctor and hospital will face no consequences for failure to keep up with stroke research but you sure will. How long will YOU let your stroke hospital be incompetent?

Reprogramming brain cells to restore vision after a stroke


THIS BLOG IS ALSO AVAILABLE AS AN AUDIO CAST

About one third of stroke survivors experience vision loss. It can be a devastating side effect as most patients will not fully recover their vision and there are currently no reliable treatments available. But thanks to a collaborative effort by two teams of researchers from Purdue University and Jinan University in China, there may be a way to use gene therapy to recover lost vision after a stroke.

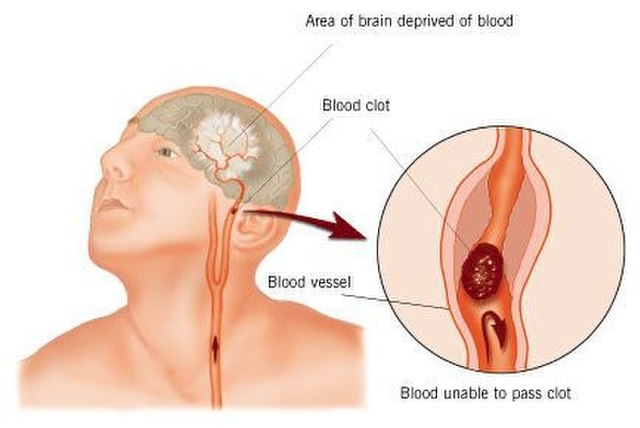
A stroke happens when part of the brain is starved of oxygen which can result in death of brain cells or neurons. Oftentimes this is caused by a blockage in an artery in the brain. Given the location of these vital arteries, most strokes lead to loss of motor function and in some cases, permanent vision loss.

The brain is an incredible machine and capable of remapping its neural pathways enough to restore some visual function, but this isn’t always the case. The neurons that are destroyed in the process of experiencing a stroke do not regenerate and lose their ability to communicate/transmit information between different areas of the brain, and between the brain and the rest of the nervous system.

Two research teams, one led by Alexander Chubykin at Purdue University’s and the other led by Gong Chen at Jinan University, have taken a different approach to neural regeneration by reprogramming local glial cells into neurons, therefore restoring connections between the old neurons and the newly reprogrammed neurons.

In a news release, Dr. Chubykin says the results in the lab look promising. “We can watch the mice get their vision back. We don’t have to implant new cells, so there’s no immunogenic rejection. This process is easier to do than stem cell therapy, and there’s less damage.”

The collaborative research, published in the journal Frontiers in Cell and Developmental Biology, is promising not only in aiding with vision restoration after a stroke but could also lead to similar treatment for reestablishing motor function. Visual function is easier than motor skills to measure accurately and the scientists are looking into the effectiveness of this procedure in live mice using advanced optical imaging tools. If the study continues to provide positive results, it might not be long before human trials are started. 

CIRM is also funding clinical trials to help repair vision loss and to help people recovering from a stroke.

FDA OKs trial to test stroke treatment in distal brain regions

 WHOM in your stroke hospital is specifically following and implementing research results into stroke protocols? NO SUCH PERSON, YOU DON'T HAVE A STROKE HOSPITAL, FIRE THEM ALL.

FDA OKs trial to test stroke treatment in distal brain regions

The FDA has granted investigational device exemption approval to Rapid Medical for a trial to expand stroke treatment to distal brain regions, according to a press release.

The DISTALS study, a randomized controlled trial seeking to examine the safety and effectiveness of distal thrombectomy, will involve Rapid Medical’s Tigertriever 13, the smallest thrombectomy device available.

“We're especially pleased to receive unprecedented FDA IDE approval for a study with DISTALS’ focus," principal investigator Jeffrey Saver, MD, FAHA, professor of neurology and director of the Comprehensive Stroke and Vascular Neurology Program at UCLA, said in the release. "With the ever-growing benefits of mechanical thrombectomy, we hope to offer better recoveries to a much broader patient population.”

At present, less than 10% of patients who had ischemic stroke received mechanical thrombectomy, which has been shown to significantly improve outcomes, according to the release. Tigertriever 13 has been used in approximately 1,500 patients in Europe and the Middle East. With data from the DISTALS Study, Rapid Medical aims to reach an additional 25% to 40% of stroke patients with this treatment form. The intervention targets far areas of the brain, including M3 blood vessels and allows intervention within 24 hours from onset of symptoms.

"The DISTALS trial is critical for the field of interventional stroke therapy,” co-coordinating investigator David Fiorella, MD, PhD, director of the Cerebrovascular Center at Stony Brook University Medical Center in New York, said in the release. "It potentially allows us to offer thrombectomy to an additional large group of stroke patients who may benefit substantially.”

Aspiration Versus Stent Retriever Thrombectomy for Posterior Circulation Stroke

 Will your emergency room doctor have this updated information in their stroke procedures when you next present to the hospital with a stroke? 

I have zero confidence level in any stroke hospital keeping up and implementing stroke research.  All you ever get from hospitals are that they are following 'Get With the Guidelines'; these are way too static to be of any use. With thousands on pieces of stroke research yearly it would take a Ph.D. level research analyst to keep up, create protocols, and train the doctors and therapists in their use. 

If your stroke hospital doesn't have that, you don't have a well functioning stroke hospital, you have a dinosaur.

Aspiration Versus Stent Retriever Thrombectomy for Posterior Circulation Stroke

and on behalf of the MR CLEAN Registry investigators
Originally publishedhttps://doi.org/10.1161/STROKEAHA.121.034926Stroke. 2021;0:STROKEAHA.121.034926

Background and Purpose:

Whereas a clear benefit of endovascular treatment for anterior circulation stroke has been established, randomized trials assessing the posterior circulation have failed to show efficacy. Previous studies in anterior circulation stroke suggest that advanced thrombectomy devices were of great importance in achieving clinical benefit. Little is known about the effect of thrombectomy techniques on outcomes in posterior circulation stroke. In this study, we compare first-line strategy of direct aspiration to stent retriever thrombectomy for posterior circulation stroke.

Methods:

We analyzed data of patients with a posterior circulation stroke who were included in the Multicentre Randomized Clinical Trial of Endovascular Treatment for Acute Ischemic Stroke in the Netherlands Registry between March 2014 and December 2018, a prospective, nationwide study, in which data were collected from consecutive patients who underwent endovascular treatment for ischemic stroke in the Netherlands. We compared patients who underwent first-line aspiration versus stent retriever thrombectomy. Primary outcome was functional outcome according to the modified Rankin Scale. Secondary outcomes were reperfusion grade, complication rate, and procedure duration. Associations between thrombectomy technique and outcome measures were estimated with multivariable ordinal logistic regression analyses.

Results:

Overall, 71 of 205 patients (35%) were treated with aspiration, and 134 (65%) with stent retriever thrombectomy. Patients in the aspiration group had a lower pc-ASPECTS on baseline computed tomography, and general anesthesia was more often applied in this group. First-line aspiration was associated with better functional outcome compared with stent retriever thrombectomy (adjusted common odds ratio for a 1-point improvement on the modified Rankin Scale 1.94 [95% CI, 1.03–3.65]). Successful reperfusion (extended Thrombolysis in Cerebral Infarction ≥2B) was achieved more often with aspiration (87% versus 73%, P=0.03). Symptomatic hemorrhage rates were comparable (3% versus 4%). Procedure times were shorter in the aspiration group (49 versus 69 minutes P<0.001).

Conclusions:

In this retrospective nonrandomized cohort study, our findings suggest that first-line aspiration is associated with a shorter procedure time, better reperfusion, and better clinical outcome than stent retriever thrombectomy in patients with ischemic stroke based on large vessel occlusion in the posterior circulation.


Saturday, September 11, 2021

Sheffield medics developing 'groundbreaking' treatment that could change stroke victims' lives

Interesting. Whom is the person in the hospital following research and getting good stuff into intervention? Nobody? Then the whole hospital needs to be reconstituted, starting with the board of directors.

Sheffield medics developing 'groundbreaking' treatment that could change stroke victims' lives

Sheffield medics are in the process of developing a device that stroke survivors can wear on their arm, which will help them overcome stiffness and recover more easily.

Wednesday, 4th August 2021, 3:00 pm
Researchers at Sheffield Teaching Hospitals NHS Foundation Trust will be leading the trial to develop a new lightweight wearable device delivering tiny electrical pulses to the arm.

Around a third of stroke survivors experience excessive muscle stiffness affecting an arm - a tiring, painful and disabling consequence of their condition which limits their ability to do usual day-to-day tasks and can lead to permanent rigidity as muscles become resistant to stretching.

The new Sheffield Adaptative Patterned Electrical Stimulation (SHAPES) device, which works like a TENS machine but is far more advanced, is to be built and tested thanks to £1.2m grant award from the National Institute for Health Research’s ‘Invention for Innovation’ programme.

The team behind the SHAPES technology.

Dr Siva Nair, Consultant Neurologist at Sheffield Teaching Hospitals NHS Foundation Trust and lead for the clinical trial, said: “Our device is a significant technological advancement in the field of therapeutic electrical stimulators.


"Muscle stiffness in the arm is a major barrier to rehabilitation after stroke, so we are really pleased that we have received funding to test this innovative form of treatment. If our study is successful it will lead to a novel therapy for the rehabilitation of muscle stiffness after stroke.

"The technology also has the potential to be useful in the treatment of muscle stiffness in several other diseases of the brain and spinal cord, such as head injury and multiple sclerosis which could offer renewed hope to thousands of patients living with the consequences of debilitating neurological conditions.”

The band would fit on the arm as shown in the diagram.

Through a unique combination of electronic design and programming, the SHAPES technology is able to deliver continuous moving patterns of tiny electrical pulses to the arm to multiple areas at any given time.

Previous research suggests that this variability in sensations is important in improving recovery from the muscle stiffness caused by stroke.


The SHAPES technology will be tested on patients, recruited between two to sixteen weeks post-stroke, in a clinical trial later in the year. It is hoped that the technology will improve rehabilitative outcomes for stroke patients at an optimal point in their recovery and will be cost-effective for the NHS to use.

Professor Adewale O Adebajo, 63, who lives in Whirlow and suffered with a life-threatening bleed on his brain in 2015 while working at Barnsley Hospital, said the new technology was important in addressing an unmet need in stroke survivors.

“Excessive muscle stiffness in an arm is a really unpleasant and painful consequence of having a stroke,” he said.

“I was mainly wheelchair dependent following my stroke and I suffered a lot of weakness in my left side, but one of the things I wanted to do during my recovery was to use my left arm.

“I love playing table tennis, but I couldn’t do that, and when I would lift my arm up and let it go it was just like dead wood. It was very unpleasant. In my opinion Sheffield is a world leader in stroke research, so this new technology, if successful, could really help in reducing pain and symptoms and in restoring arm function.”


Friday, December 4, 2020

Case Western Reserve University School of Medicine researchers say newly found protein is bio-marker for disease; suggest suppression of ‘aggregatin’ could lead to future treatments to slow Alzheimer’s progression

Do you really think your stroke hospital has an employee whose only job is to follow research and create protocols to treat their patients? Or to get further research done in humans?  Then you are in la-la land.

CaseWestern Reserve University School of Medicine researchers say newly foundprotein is bio-marker for disease; suggest suppression of ‘aggregatin’ could lead to future treatments to slow Alzheimer’s progression

Researchers at Case Western Reserve University School of Medicine say they have identified a previously unknown gene and associated protein that could potentially be suppressed to slow the advance of Alzheimer’s disease.

 “Based on the data we have, this protein can be an unrecognized new risk factor for Alzheimer’s disease (AD),” said Xinglong Wang, an associate professor of pathology at the School of Medicine. “We also see this as a potential novel therapeutic target for this devastating disease.”

Xinglong Wang

Wang said proving the latter assertion, which has not yet been tested in humans, would require additional research to corroborate the function of the protein they have dubbed “aggregatin.” Eventually, that would someday mean clinical trials with Alzheimer’s patients, he said.

“This protein characteristically accumulates, or aggregates, within the center of plaque in AD patients, like the yolk of an egg—which is part of the reason we named it ‘aggregatin,’” Wang said.

A research team led by Wang and Xiaofeng Zhu, a professor of population and quantitative health sciences at the School of Medicine, has filed for a patent through the university’s Office of Research and Technology Management for “novel Alzheimer’s disease treatments and diagnosis based on this and related study,” Wang said.

photograph of Xiaofeng Zhu
Xiaofeng Zhu

“We’re very excited about this because our study is likely the first systematic work combining the identification from a genome-wide association study of high dimensional brain-imaging data and experimental validation so perfectly in Alzheimer’s disease,” Zhu said.

Their research was published this month by the scientific journal Nature Communications and supported by grants from the National Institutes of Health (NIH) and the Alzheimer’s Association. Genomic and brain imaging data was obtained from the Alzheimer’s Disease Neuroimaging Initiative, which is supported by the NIH.

Alzheimer’s disease affects millions

More than 5.7 million Americans have Alzheimer’s disease, which is the primary cause of dementia and sixth-leading cause of death in the United States. That population is predicted to reach 14 million by the year 2050, according to the Alzheimer’s Association.

The relationship between Alzheimer’s (and subsequent brain atrophy) and amyloid plaques—the hard accumulations of beta amyloid proteins that clump together between the nerve cells (neurons) in the brains of Alzheimer’s patients—has been well-established among researchers.

Less understood is precisely how that amyloid-beta actually leads to plaque formation—and where this new work appears to have broken new ground, Wang said.

Further, while there has been much research into what genes might influence whether or not someone gets Alzheimer’s, there is less understanding of genes that might be linked to the progression of the disease, meaning the formation of plaque and subsequent atrophy in the brain.

The role of  ‘aggregatin’ protein

An image of the 'Aggregatin' protein from the paper published by Wang, Zhu and collaborators.
An image of the ‘Aggregatin’ protein from the paper published by Wang, Zhu and collaborators.

In the new work, the researchers began by correlating roughly a million genetic markers (called single-nucleotide polymorphisms, or SNPs) with brain images. They were able to identify a specific SNP in the FAM222, a gene linked to different patterns of regional brain atrophy.

Further experiments then suggested that the protein encoded by gene FAM222A is not only associated with AD patient-related beta-amyloid plaques and regional brain atrophy, but that “aggregatin” attaches to amyloid beta peptide—the major component of plaque and facilitates the plaque formation.

So when researchers injected mouse models with the “aggregatin” protein (made from the FAM222A gene), plaque (amyloid deposits) formation accelerated in the brain, resulting in more neuroinflammation and cognitive dysfunction. This happened, they report, because the protein was found to bind directly the amyloid beta peptide, thus facilitating the aggregation and placque formation, Wang said.

Conversely, when they suppressed the protein, the plaques were reduced and neuroinflammation and cognitive impairment alleviated.

Their findings indicate that reducing levels of this protein and inhibition of its interaction with amyloid beta peptide could potentially be therapeutic—not necessarily to prevent Alzheimer’s but to slow its progression. 


For more information, contact Mike Scott at mike.scott@case.edu


Friday, July 31, 2020

New Clues To ALS And Alzheimer's Disease From Physics

Interesting. Does your hospital have an employee assigned to keep up with research and distribute useful research to the staff? If not you have a COMPLETELY INCOMPETENT HOSPITAL.

New Clues To ALS And Alzheimer's Disease From Physics


This light micrograph from the brain of someone who died with Alzheimer's disease shows the plaques and neurofibrillary tangles that are typical of the disease. A glitch that prevents healthy cell structures from transitioning from one phase to the next might contribute to the tangles, researchers say.
Jose Luis Calvo/ Science Source
The same process that causes dew drops to form on a blade of grass appears to play an important role in Alzheimer's disease and other brain diseases.
The process, known as phase transition, is what allows water vapor to condense into liquid water, or even freeze into solid ice. That same sort of process allows brain cells to constantly reorganize their inner machinery.
But in degenerative diseases that include amyotrophic lateral sclerosis, frontotemporal dementia and Alzheimer's, the phase transitions inside neurons seem to go awry, says Dr. J. Paul Taylor, a neurogeneticist at St. Jude Children's Research Hospital in Memphis, and an investigator with the Howard Hughes Medical Institute.
This malfunctioning prompts the interior of the cell to become too viscous, Taylor says. "It's as if you took a jar of honey [and] left it in the refrigerator overnight."
In this sticky environment, structures that previously could nimbly disassemble and move around become "irreversibly glommed together," says Clifford Brangwynne, a professor of chemical and biological engineering at Princeton University and an investigator with the Howard Hughes Medical Institute. "And when they're irreversibly stuck like that, they can no longer leave to perform functions elsewhere in the cell."
That glitch seems to allow toxins to begin to build up in and around these dysfunctional cells, Taylor says — including the toxins associated with Alzheimer's and other neurodegenerative diseases.
The science behind this view of brain diseases has emerged only in the past decade.
In 2009, Brangwynne was part of a team that published a study showing that phase transitions are important inside cells — or at least inside the reproductive cells of worms.


"Originally, there was not a lot of traction for that idea," Brangwynne says. "Then — around about 2015 — people started to suddenly pay a lot of attention."
By that time, Taylor, too, had stumbled upon phase transition via a very different path.
As a practicing neurologist and geneticist at the University of Pennsylvania, he'd seen himself as a sort of medical detective.
"Typically the most oddball diseases that didn't fit into another category would wind up in my clinic, which I loved," he says.
One disease in particular caught Taylor's attention.
"We had been tracking a number of families that had an unusual degenerative illness," he says. "It was kind of a blend of a dementia and ALS."
Patients developed the mental problems of dementia as well as the muscle weakness of ALS, or Lou Gehrig's disease.
Taylor figured there must be a genetic explanation. But at the time — the late 2000s — he had no easy way to study his patients' DNA.
"So I collected those [DNA samples] and hung on to them for years," he says. "And then the world changed around me."
Seemingly overnight, it became feasible to sequence a person's entire genome. Taylor saw an opportunity.
"I dug those DNAs back out of the freezer," he says. "And we were fortunate enough to find the genetic basis for the disease in these families that I had known for, at that point, a decade."
What Taylor found was gene mutations that caused abnormal phase transitions in cells. And he found evidence of similar mutations in other neurodegenerative diseases.
This research earned Taylor the 2020 Potamkin Prize, a big deal in Alzheimer's research. And it got a lot of biotech companies thinking about ways to fix problems with phase transitions inside cells.
"I think it's probably safe to say that you'll see some of these types of therapies within the next couple of years," Taylor says.
Brangwynne says neurodegenerative diseases are an appealing target because the physics behind the problem is now clear, and because cells already contain mechanisms to regulate phase transition.
Inside a healthy nerve cell, he says, many molecules act a bit like people socializing.
"Something like at a party, where we've got little clusters of people hanging out and having nice conversations," he says. "They're free to come and go as they please."
That can change, though — at a party or inside a brain cell.
"What happens in neurodegenerative disease is that the 'people' are irreversibly stuck together — they can't leave," Brangwynne says. "This is the Hotel California of biomolecular interactions."
But Brangwynne says that doesn't have to be the case.
In the lab, at least, experimental drugs and genetic tweaks have been used to unstick these molecules.
That could lead to new treatments for neurodegenerative diseases, Brangwynne says. And the ability to correct aberrant phase transitions may also be useful for other illnesses, including certain cancers, he says.
"It's very clear that this principle is at play in many, many diseases," Brangwynne says.
The startup Dewpoint Therapeutics hopes to develop phase-transition treatments for both cancer and neurodegenerative diseases. Late last year, Dewpoint, which is based in Boston and Dresden, Germany, signed a $100 million deal with the pharmaceutical giant Bayer.

Sunday, April 12, 2020

Upper limb rehabilitation robotics after stroke: A perspective from the University of Padua, Italy

Did ANY OF THIS TURN INTO PROTOCOLS? Or did we just waste 11 years? 2.5 hours to read, 73 pages. Is that worthwhile to get your stroke patients better recovered?  Or can your hospital research analysis employee summarize this into bullet points? Assuming your board of directors has enough brains to require such an employee.

Upper limb rehabilitation robotics after stroke: A perspective from the University of Padua, Italy 2009 

 Articles from the workshop held in September 5–6, 2008 in Crotone, Italy

Saturday, April 11, 2020

Relation between improvement of glycemic control and reduction of major cardiovascular events in 15 cardiovascular outcome trials: a meta‐analysis with metaregression

Once again they missed the memo that WHO reclassified stroke in 2006, now a neurological disease not cardiovascular disease? 

If our researchers are out-of-date how do you think your stroke doctors are keeping up? Does your stroke hospital have a research analysis employee whose only job is to take stroke research and implement into interventions and train the staff in the latest? If not you don't have a stroke hospital.

The MACE definition is wrong.

Relation between improvement of glycemic control and reduction of major cardiovascular events in 15 cardiovascular outcome trials: a meta‐analysis with metaregression

Diabetes, Obesity and Metabolism — Giugliano D, Bellastella G, Longo M, et al. | April 08, 2020

A meta‐analysis with metaregression was conducted to disclose associations between reduction of HbA1c levels and risk of major cardiovascular events (MACE) in all cardiovascular outcome trials (CVOTs) so far published in patients with type 2 diabetes (T2D). Researchers carried out an electronic search up to February 10, 2020 to ascertain eligible trials. They evaluated pooled summary estimates and 95% confidence intervals according to random effects model applying the Paule‐Mandel method; restricted maximum likelihood estimators were applied to calculate model parameters in the metaregression. This study included 15 CVOTs involving a total of 138,250 patients. In CVOTs, the blood glucose reduction may play some role in lowering the risk of nonfatal stroke, at least during treatment with GLP‐1 RAs, without influencing the other two components of MACE.
Read the full article on Diabetes, Obesity and Metabolism