Changing stroke rehab and research worldwide now.Time is Brain! trillions and trillions of neurons that DIE each day because there are NO effective hyperacute therapies besides tPA(only 12% effective). I have 523 posts on hyperacute therapy, enough for researchers to spend decades proving them out. These are my personal ideas and blog on stroke rehabilitation and stroke research. Do not attempt any of these without checking with your medical provider. Unless you join me in agitating, when you need these therapies they won't be there.

What this blog is for:

My blog is not to help survivors recover, it is to have the 10 million yearly stroke survivors light fires underneath their doctors, stroke hospitals and stroke researchers to get stroke solved. 100% recovery. The stroke medical world is completely failing at that goal, they don't even have it as a goal. Shortly after getting out of the hospital and getting NO information on the process or protocols of stroke rehabilitation and recovery I started searching on the internet and found that no other survivor received useful information. This is an attempt to cover all stroke rehabilitation information that should be readily available to survivors so they can talk with informed knowledge to their medical staff. It lays out what needs to be done to get stroke survivors closer to 100% recovery. It's quite disgusting that this information is not available from every stroke association and doctors group.

Wednesday, March 8, 2017

Here's how much the US spends on Alzheimer's disease

Our stroke associations should have stroke statistics like this readily available and use them to get research funding from foundations to solve all the fucking problems in stroke. 

Costs to treat stroke in America may double by 2030

Costs to treat stroke may increase from $71.55 billion in 2010 to $183.13 billion


http://www.businessinsider.com/alzheimers-disease-spending-in-us-to-top-259-billion-2017-3
Alzheimer's disease is the only one of the top leading causes of death whose progression can't be slowed down or stopped. 
 The neurodegenerative disease affects about 5.5 million Americans, a number that's expected to balloon to 13.8 million by 2050
And the amount spent caring for people with Alzheimer's is expected to reach $259 billion in 2017, according to a report released Tuesday by the Alzheimer's Association.
"Everybody with a brain at risk and needs to care about this," Beth Kallmyer, vice president of constituent services for the Alzheimer’s Association told Business Insider.
The search for a treatment to Alzheimer's hasn't been going well. There are only four approved drugs that treat symptoms of the disease, and several hopeful treatments have failed key studies over the last few months. 
So while death rates for illnesses such as HIV and heart disease have dropped over the past 14 years, the Alzheimer's Association noted, Alzheimer's deaths are up 89% over that period. 

Complementary and alternative interventions for fatigue management after traumatic brain injury: a systematic review

None of these are complementary or alternative interventions, they are just normal medical interventions.
http://journals.sagepub.com/doi/abs/10.1177/1756285616682675
First Published February 1, 2017 research-article


We systematically reviewed randomized controlled trials (RCTs) of complementary and alternative interventions for fatigue after traumatic brain injury (TBI).

We searched multiple online sources including ClinicalTrials.gov, the Cochrane Library database, MEDLINE, CINAHL, Embase, the Web of Science, AMED, PsychINFO, Toxline, ProQuest Digital Dissertations, PEDro, PsycBite, and the World Health Organization (WHO) trial registry, in addition to hand searching of grey literature. The methodological quality of each included study was assessed using the Jadad scale, and the quality of evidence was evaluated using the Grading of Recommendations, Assessment, Development and Evaluation (GRADE) system. A descriptive review was performed.

Ten RCTs of interventions for post-TBI fatigue (PTBIF) that included 10 types of complementary and alternative interventions were assessed in our study. There were four types of physical interventions including aquatic physical activity, fitness-center-based exercise, Tai Chi, and aerobic training. The three types of cognitive and behavioral interventions (CBIs) were cognitive behavioral therapy (CBT), mindfulness-based stress reduction (MBSR), and computerized working-memory training. The Flexyx Neurotherapy System (FNS) and cranial electrotherapy were the two types of biofeedback therapy, and finally, one type of light therapy was included. Although the four types of intervention included aquatic physical activity, MBSR, computerized working-memory training and blue-light therapy showed unequivocally effective results, the quality of evidence was low/very low according to the GRADE system.

The present systematic review of existing RCTs suggests that aquatic physical activity, MBSR, computerized working-memory training, and blue-light therapy may be beneficial treatments for PTBIF. Due to the many flaws and limitations in these studies, further controlled trials using these interventions for PTBIF are necessary.

Bacon, soda & too few nuts tied to big portion of US deaths

I bet you'll have to figure out your own diet protocol because your doctor won't have the hospital nutritionist create one for you. Stroke prevention diet, stroke rehab diet, dementia prevention diet, blood pressure reduction diet.
https://www.yahoo.com/finance/news/bacon-soda-too-few-nuts-tied-big-portion-170115771.html
Lindsey Tanner, AP Medical Writer 5 hours ago

Tuesday, March 7, 2017

TeleHealth Medical Group Introduces World’s First Guaranteed Rehabilitation Program for Stroke Victims

That is one hell of a lot of money for exercise coaching. I have yet to see any positively proven clinical results for stem cells for the brain.
http://www.prweb.com/releases/2017/03/prweb14118904.htm
TeleHealth Medical Group is pleased to announce the formal introduction of their stroke recovery guarantee program. This unique rehabilitation program is the first of its kind across the globe, and promises to be a ground-breaking development for the future of stroke treatment. As per this guarantee, patients that do not clinically improve after the program will have the option to repeat the program or claim complete refund.
The therapeutic value of stem cells is now well established in the medical fraternity.(Really? Some proof?) Stem cell regenerative therapy has already helped thousands of patients around the world recover from a wide variety of degenerative disorders including stroke.
TeleHealth Medical Group has taken a holistic approach to stroke recovery utilizing a combination of stem cell replacement therapy and IV supplements to help the body heal and regenerate faster. Another important components of this program in addition to the stem cell replacement and nutritional supplementation is the comprehensive rehabilitation program. Instead of focusing only on the brain, it looks to treat the entire body after a thorough examination of the patient’s past and current health issues to improve connectivity and relearning of damaged pathways.
The comprehensive rehabilitation program from TeleHealth Medical Group is a three month long process that involves three visits to the clinic per week. In general, each of these sessions lasts between ninety minutes and two hours.
Some of the key components of the therapy include:
  • Brain mapping to measure future progress: The patient’s assessment starts by painless mapping of their brain. This is done using a cap with many electrodes that measure the brain wave activity.(Wow, lots of woo there)
  • Brain training to build new pathways: This is done to fortify the neural pathways in the brain like tiny roadways. When stroke damages these roadways, brain training helps the brain build new ones. Virtual reality games are implemented to help patients improve their brain function.
  • Personalized virtual and extended reality rehab program: Every patient is unique, and they can personalize their V.R. rehab program. Part of the rehabilitation uses Wii games to help reprogram the brain, and hand-eye coordination helping balance.
The on-site sessions have a duration of about an hour, and take place three times a week with a lot of homework targeted towards daily reinforcement of the lessons learned. Self-guided home therapy sessions are offered three times a day, each of approximately ten minutes. This therapy has become a patient-friendly cloud-based automated system that is less expensive and very mobile.
The program is currently priced at $32,500.00 payable upon initiation. Most importantly, regardless of the type of stroke, the extent of disability, or the other illnesses of the patient, TeleHealth Medical Group promises to honor the clinical improvement guarantee.
An extraordinarily high percentage of the patients of TeleHealth Medical Group have regained mobility, speech and their lives, after undergoing their therapy. One of the earliest beneficiaries of this cutting-edge stroke treatment technique, Robert F. stated, “ I found the services provided by the TeleHealth Medical Group to be on the highest professional level. My experiences with Dr. Seth Camhi and Dr. Bryn Henderson have far exceeded my experiences with any previous medical group. I found their knowledge of the medical field to be exceptional. I highly recommend the TeleHealth Medical Group.”

Brain training improves recovery after stroke but waiting list improves equally: A multicenter randomized controlled trial of a computer-based cognitive flexibility training

You'll want your doctor to get the protocols for this.Well maybe not, maybe this is all placebo.

Brain training improves recovery after stroke but waiting list improves equally: A multicenter randomized controlled trial of a computer-based cognitive flexibility training

Abstract

BACKGROUND:

Brain training is currently widely used in an attempt to improve cognitive functioning. Computer-based training can be performed at home and could therefore be an effective add-on to available rehabilitation programs aimed at improving cognitive functioning. Several studies have reported cognitive improvements after computer training, but most lacked proper active and passive control conditions.

OBJECTIVE:

Our aim was to investigate whether computer-based cognitive flexibility training improves executive functioning after stroke. We also conducted within-group analyses similar to those used in previous studies, to assess inferences about transfer effects when comparisons to proper control groups are missing.

METHODS:

We conducted a randomized controlled, double blind trial. Adults (30-80 years old) who had suffered a stroke within the last 5 years were assigned to either an intervention group (n = 38), active control group (i.e., mock training; n = 35), or waiting list control group (n = 24). The intervention and mock training consisted of 58 half-hour sessions within a 12-week period. Cognitive functioning was assessed using several paper-and-pencil and computerized neuropsychological tasks before the training, immediately after training, and 4 weeks after training completion.

RESULTS AND CONCLUSIONS:

Both training groups improved on training tasks, and all groups improved on several transfer tasks (three executive functioning tasks, attention, reasoning, and psychomotor speed). Improvements remained 4 weeks after training completion. However, the amount of improvement in executive and general cognitive functioning in the intervention group was similar to that of both control groups (active control and waiting list). Therefore, this improvement was likely due to training-unspecific effects. Our results stress the importance to include both active and passive control conditions in the study design and analyses. Results from studies without proper control conditions should be interpreted with care.
PMID:
28257436
DOI:
10.1371/journal.pone.0172993
[PubMed - in process]
Free full text

Transient Micro - needle Insertion into Hippocampus Triggers Neurogenesis and Decreases Amyloid Burden in a Mouse Model of Alzheimer’s Disease

What will your doctor do to followup this and see if useful for stroke recovery? ABSOLUTELY NOTHING I BET. No contacting researchers, no updating the stroke strategy, no talking to stroke leadership? You do want neurogenesis, don't you?

Transient Micro - needle Insertion into Hippocampus Triggers Neurogenesis and Decreases Amyloid Burden in a Mouse Model of Alzheimer’s Disease

High Versus Low Load Resistance Training: The Effect of 24 Weeks Detraining on Serum Brain Derived-Neurotrophic Factor (BDNF) in Older Adults

BDNF is very important for your recovery, hopefully your doctor knows that and has a protocol for delivering it for you. I have 106 posts on BDNF for your doctors perusal.
https://www.ncbi.nlm.nih.gov/pubmed/28244559

Abstract

BACKGROUND:

Previously we showed that 12 weeks of mixed-low resistance training (LOW+) significantly increased circulating BDNF in older male individuals.

OBJECTIVES:

To examine the impact of 24 weeks detraining on circulating BDNF.

DESIGN:

Randomized intervention study.

SETTING:

Community-dwelling older adults.

PARTICIPANTS AND METHODS:

Forty-seven out of 56 participants stopped training (detraining) after 12 weeks of resistance exercise (3x/week) at either HIGH-resistance (5 Males, 5 Females, 2x10-15 repetitions at 80%1RM), LOW-resistance (6 Males, 7 Females, 1x80-100 repetitions at 20%1RM), or mixed-low LOW+-resistance (6 Males, 8 Females, 1x60 repetitions at 20%1RM followed by 1x10-20 repetitions at 40%1RM), of whom 37 (aged 68±5 years) provided sufficient serum samples for BDNF analysis at baseline, 12 week and at 36 weeks (24 weeks detraining).

RESULTS:

BDNF had initially increased by 31% (from 33.4±10.9 ng/mL to 44.5±13.2 ng/mL, p=0.005) after 12 weeks in the LOW+ exercise group in males and decreased by 26% (from 44.5±13.2 ng/mL to 32.9±10.7 ng/mL) after detraining, though not statistically significant (p=0.082). In females, no significant change in BDNF was found in any of the intervention groups (p>0.05), neither after training, nor detraining. At 36 weeks all of the subgroups showed BDNF levels comparable (all p>0.10) to baseline (before the exercise intervention).

CONCLUSIONS:

Our results show that a 12-weeks LOW+ resistance exercise increases circulating BDNF in older male subjects but that this reduces back to baseline levels after 24 weeks of detraining. Continuous exercise adherence seems to be needed to sustain the training-induced effects on BDNF in older persons. Additional studies are needed to unravel the underlying mechanisms, as well as to confirm the observed sex difference.

KEYWORDS:

BDNF; detraining; muscle fatigue; older adults; resistance training; training loads
PMID:
28244559
DOI:
10.14283/jfa.2017.2
[PubMed - in process]

Arteriogenesis versus angiogenesis

Your doctor should know the difference and exactly what protocols are needed for both for various parts of your brain to accomplish 100% recovery.

Arteriogenesis versus angiogenesis

Chocolate consumption and risk of stroke among men and women: A large population-based, prospective cohort study

Was this earlier research not good enough to write up protocols? Do they even know about this earlier research? Still no protocols so you have idea of kinds, amounts or frequency.  Hire your own researchers, no one else is going to do a damn thing.


Flavanol-rich chocolate acutely improves arterial function and working memory performance counteracting the effects of sleep deprivation in healthy individuals June 2016


Cocoa Flavanols: Scientifically proven health benefits  Feb. 2016


Boosting Cocoa's Dementia-Fighting Benefits  Oct. 2015 


2 Cups of Hot Cocoa-a-Day Keeps the Neurologist Away  June 2015 


Sweet dreams: eating chocolate prevents heart disease  June 2015


 Cocoa flavanol consumption improves cognitive function, blood pressure control, and metabolic profile in elderly subjects: the Cocoa, Cognition, and Aging (CoCoA) Study—a randomized controlled trial  Jan. 2015 


Blueberries, Avocados and Cocoa Beans May Keep Cardiologists at Bay  Jan. 2015


This Common Beverage Reversed Normal Age-Related Memory Loss in Three Months - Cocoa  Oct. 2014 


Cocoa Extract May Counter Specific Mechanisms of Alzheimer’s Disease  June 2014 


Could Hot Cocoa Improve Brainpower in Seniors?  Aug. 2013


Chocolate-loving countries produce more Nobel laureates  Oct. 2012


Eating small bar of chocolate cuts risks of stroke in men  Sept. 2012


Hot Cocoa May Boost Seniors' Brain Power  Aug. 2012


Dark Chocolate: Sweet Prevention for CV Events  June 2012 


The latest here:


Chocolate consumption and risk of stroke among men and women: A large population-based, prospective cohort study

Atherosclerosis, 03/06/2017
Dong JY, et al. – Here, the clinicians intend to inquire the prospective correlations between chocolate consumption and risk of stroke among men and women in a large population–based cohort. The outcomes illustrated a significant inverse correlation between chocolate consumption and risk of developing stroke in women. Nevertheless, residual confounding could not be excluded as an alternative explanation for the findings.

Methods

  • A total of 38,182 men and 46,415 women aged 44–76 years, and free of cardiovascular disease, diabetes, and cancer at baseline in 1995 and 1998, were followed up until the end of 2009 and 2010, respectively.
  • They observed data on chocolate consumption for each participant using a self-administrated food frequency questionnaire that included 138 food and beverage items.
  • They applied cox proportional hazards regression models to evaluate hazard ratios (HRs) of stroke in relation to chocolate consumption.

Results

  • They distinguished 3558 incident strokes cases (2146 cerebral infarctions and 1396 hemorrhagic strokes) during a median follow-up of 12.9 years,.
  • They demonstrated that after adjustment for age, body mass index, life styles, dietary intakes, and other risk factors, chocolate consumption was correlated with a significant lower risk of stroke in women (HR = 0.84; 95% CI, 0.71–0.99).
  • Nevertheless, it was considered that the correlation in men was not significant (HR = 0.94; 95% CI, 0.80–1.10).
  • Lastly, the correlation did not vary by stroke subtypes in either men or women.
Go to Abstract Print Article Summary Cat 2 CME Report

Rob Benedict Announces New Clothing Campaign Benefiting National Stroke Association

Oh, oh,oh, wonderful conscience laundering. And since the NSA does nothing for stroke survivors the money raised will be wasted.

Rob Benedict Announces New Clothing Campaign Benefiting National Stroke Association

Scientists show cognitive enhancing drugs can improve chess play

Would this be useful for cognitive decline in stroke rehab? We'll never know since nothing seems to be ever followed up to help stroke survivors.

Scientists show cognitive enhancing drugs can improve chess play


The first study to both show and measure the effects of cognitive-enhancing drugs such as modafinil, methylphenidate (best known under the trade name Ritalin), and caffeine, on chess play is being published in the March edition of the peer-reviewed journal European Neuropsychopharmacology. This shows significant cognitive improvements for modafinil and methylphenidate, and may have influence how these drugs are used off-label in a range of activities.
The study shows how certain drugs can alter and even improve the way in which the brain processes complex information. As applied to chess (and other fields), this supports the possibility pharmaceutical enhancement giving a player a competitive advantage. The World Chess Federation, FIDE, recognised this by introducing an anti-doping code in 20141.
Now a new double-blind randomised controlled trial by scientists from German and Swedish universities has shown that the cognitive enhancing drugs, modafinil, methylphenidate, and caffeine can improve chess play. Previous research had shown that the drugs could improve cognitive performance when a subject was tired or was performing below his or her optimal performance, but this is the first work to show improvement of cognitive performance even if the subject is performing at a very high level.
The team, led by Professor Klaus Lieb (University of Mainz, Germany) gave 39 male chess players controlled doses of one of the drugs modafinil, methylphenidate, caffeine, or a placebo. They then played a series of rapid, time-limited (15 minutes) games against a chess programme (the popular Fritz 12 programme) which had been matched to the strength of each individual player. This was a 4-day “crossover” study, meaning that the player had who taken modafinil on day 1 would receive a different drug (or placebo) on each subsequent day, and so on. In total the researchers gathered data from over 3000 chess games.
“One of the strengths of this study is that the chess programme provides a reference point to measure the cognitive effect”, commented Professor Lieb, “
They found that all three substances tested caused the players to increase the time needed to decide on a move, meaning that more games were lost as the players ran out of time. However, when the analysis was corrected to take out games lost on time, the team found that both modafinil and methylphenidate significantly increased the players’ scores, whereas caffeine showed a more modest, but not statistically significant improvement.
“We were surprised to see that players on the drugs played more slowly than normal, indicating that their thought processes seemed to be deeper” said Professor Lieb.
He continued:
 “The key to this work is in understanding that players showed an improvement if under less time pressure. The results themselves would be pretty significant in chess terms. For example, both modafinil and methylphenidate gave an improvement coefficient of around 0.05.  If we correct for the slowest players, then the effect would be the equivalent of moving a player from say, number 5000 in the world ranking, to number 3500 in the world ranking. In a single game, the effect is the equivalent of having the white pieces, every time, which give around a 5% better chance of winning.
These differences can be pretty significant in a competitive sport or game. But this work also allows us to put a figure on the way that the use of these drugs can affect the way we think in a range of everyday intellectual activities, such as studying for an exam.”
The researchers stress that the use of these drugs as cognitive enhancers are ‘off-label’ uses, and may have significant side effects, especially with repeated use. As all pharmaceutical substances have risks and benefit, there is little data that compares the benefit of cognitive enhancement against any risk or side effect. They also note that this is a comparatively small study, and requires replication before firm conclusions can be drawn.
Trevor Robbins (Professor of Cognitive Neuroscience at the University of Cambridge), who was once ranked in the top 20 chess players in England, commented:
“Chess involves several higher brain processes including working memory, planning, cognitive flexibility and cognitive control. Drugs such as modafinil have previously been found to enhance performance of such cognitive functions in laboratory based studies of non-sleep deprived volunteers, although sometimes at the cost of prolonging response times.
This work, one of the first to study drug effects on chess, shows that these performance enhancements can translate into real-world activities in this study of chess players who improved their performance, though sometimes at the cost of losing on time. ".
Professor Robbins won the Brain Prize in 2014, which is considered the most important international neuroscience prize.
Professor David Nutt (Imperial College), ex-President of the European College of Neuropsychopharmacology, added:
“We have known for decades that stimulants improve sustained performance through reducing fatigue effects on attention and vigilance. So these current data provide new and controlled data in chess - a test of complex cognitive function.  It’s likely that other stimulants could do the same so this does raise interesting issues for regulators of these activities. Clearly more research is needed”
http://www.europeanneuropsychopharmacology.com/article/S0924-977X(17)30019-6/abstract

Monday, March 6, 2017

Microwave Imaging for Brain Stroke Detection and Monitoring using High Performance Computing

This would seem to be much better than putting CT scanners in ambulances. But I bet followup will take decades since we have NO stroke leadership pushing for useful research to get done.  In 94 seconds for a diagnosis we could get to negative door-to-needle time. Who is going to put that as a goal for their stroke department?
https://ercim-news.ercim.eu/en108/special/microwave-imaging-for-brain-stroke-detection-and-monitoring-using-high-performance-computing
by Pierre-Henri Tournier
Microwave tomography is a novel imaging modality holding great promise for medical applications and in particular for brain stroke diagnosis. We demonstrated on synthetic data the feasibility of a microwave imaging technique for the characterisation and monitoring of strokes. Using high performance computing, we are able to obtain a tomographic reconstruction of the brain in less than two minutes.
Stroke, or cerebrovascular accident (CVA), is classically characterised as a neurological deficit attributed to an acute focal injury of the central nervous system by a vascular cause, and is a major cause of disability and death worldwide. About 85% of CVAs are ischemic due to cerebral infarction, caused by an interruption of the blood supply to some part of the brain, and 15% are haemorrhagic. Differentiating between ischemic and haemorrhagic CVAs is an essential part of the initial workup of the patient, and rapid and accurate diagnosis is crucial for patient survival; here, neuroimaging plays a vital role. Computed Tomography (CT) and Magnetic Resonance Imaging (MRI) are the ‘gold’ standards, but their use is not well suited to efficient medical care of CVAS, as they are bulky diagnostic instruments and cannot be used in continuous brain monitoring. A non-invasive and transportable/portable device for the characterisation and monitoring of CVAs would have clear clinical applications, beginning with the very first instance of patient care in an ambulance and extending to continuous patient monitoring at the hospital.
Microwave tomography is a novel imaging modality with a large number of potential attractive medical applications, and is based on the difference between the dielectric properties of normal and diseased brain tissues. Microwave tomography features rapid data acquisition time, and together with rapid tomographic reconstructions allows detecting, identifying and monitoring CVA continuously (head tissues are exposed to low-level microwave incident field).
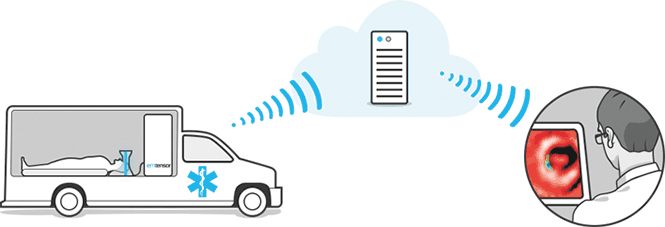
From a computational point of view, microwave imaging requires the solution of an inverse problem based on a minimisation algorithm. Reconstruction algorithms are computationally intensive with successive solutions of the forward problem needing efficient numerical modelling and high-performance parallel computing. The raw data acquired by the microwave imaging system can be wirelessly transferred to a remote computing center, where the tomographic images will be computed. The images can then be quickly transferred to the hospital (see Figure 1). This methodology involves distinct research fields: optimisation, inverse problems, approximation and solution methods for the simulation of the forward problem modelled by Maxwell’s equations. The latter is challenging in itself as the modelling must accurately take account of the high heterogeneity and complexity of the different head tissues.
Figure 1: Principle of microwave imaging. Image courtesy of EMTensor.
Our work demonstrates on synthetic data the feasibility of a microwave imaging technique for the characterisation of CVAs, and won our research team the Bull-Joseph Fourier Prize in 2015. The numerical framework is based on high-performance computing open-source tools developed by our research team: the HPDDM library [1] (L1) is an efficient parallel implementation of Domain Decomposition Methods (DDM) and is interfaced with the finite element software FreeFem++[2](L2). Our work was carried out in collaboration with EMTensor, an Austrian innovative SME dedicated to biomedical imaging and is based on their BRain IMaging Generation1 (BRIMG1) prototype [3]. EMTensor™’s experimental system consists of an electromagnetic reverberating chamber surrounded by 160 antennas, able to work alternately as emitters or receivers (see Figure 2). The measurements are gathered in the scattering matrix, which is the input of the reconstruction algorithm. We first validated the forward problem by comparing the experimental data with the simulation.


We then created synthetic data corresponding to an accurate numerical model of a human head with a simulated haemorrhagic CVA as input for the inverse problem.  We designed and tested our inversion algorithm for monitoring the evolution of the CVA, using synthetic data corrupted with 10% white Gaussian noise. Our scalable algorithm uses multiple levels of parallelism, which allows us to reconstruct an image of the brain in 94 seconds using 4,096 cores. Figure 3 shows the reconstructed images for three evolution steps of the haemorrhagic CVA. The reconstruction time, which can be further refined, already fits the physicians’ objective to obtain an image every fifteen minutes for efficient monitoring.

Almost half of stroke survivors suffer fatigue, study reveals

Well shit, survivors could have told you that decades ago. And once again a description of a problem but no solutions. Damn it all, do something for survivors, solve their problems.
http://www.nottingham.ac.uk/news/pressreleases/2017/march/almost-half-of-stroke-survivors-suffer-fatigue-study-reveals.aspx

03 Mar 2017 16:11:23.077
PA35/17
Almost half of people who experience a stroke suffer from fatigue in the early days of their recovery, a landmark new study has found.
Although stroke survivors have reported fatigue as a problem, previous estimates of the numbers of people affected have varied greatly – from one-quarter to almost three-quarters of stroke survivors.
Now, for the first time, a more accurate picture of the problem is being published in the journal Clinical Rehabilitation, thanks to The Nottingham Fatigue after Stroke (NotFAST) study, led by experts at The University of Nottingham.
Click here for full story
The study, funded by the Stroke Association, is the first to specifically exclude patients with depression, which is strongly linked to fatigue, and which may have influenced the outcome of previous studies that included people with depressive symptoms.
Avril Drummond, Professor of Healthcare Research and Director of Research in the University’s School of Health Sciences, led the study.
She said: “Fatigue is not feeling tired; the terms are not the same. Fatigue is an overwhelming feeling of exhaustion which doesn’t improve with sleep or rest and which isn’t related to activity.
“Fatigue is a major problem for stroke survivors and effects all aspects of their lives. It can be a key factor in reducing participation in rehabilitation after stroke, and this can have a real impact on recovery. People simply do not reach their fullest potential.”
The study recruited patients within four weeks of experiencing a stroke from four UK inpatient stroke services at Nottingham University Hospitals, University Hospitals of Leicester, University College London Hospitals and Salford Royal Hospitals over an 18- month period. The study excluded patients with dysphasia, dementia and depressive symptoms.
The participants were assessed for: self-reported fatigue; mobility and activities of daily living; sleep; mood and emotional factors; and cognitive abilities.
The patients were followed up between four and six weeks after their stroke and the study found that 43 per cent of participants reported experiencing fatigue – for a large proportion of them (62 per cent) this was a new, post-stroke symptom.
Professor Drummond added: “We have followed up the patients over the longer term and will publish the results of their progress at six months after their stroke in due course.
“It is incredibly important that clinicians become more aware of fatigue as it has a huge impact on rehabilitation and quality of life.”
Dr Dale Webb, Director of Research and Information at the Stroke Association, said: “We are delighted to have supported this research, and hope that it will help lift the veil on what is one of the most distressing, poorly understood, and inadequately managed conditions caused by stroke. There is so much more that needs to be done, but this research is a significant step towards getting these stroke survivors the support they so desperately need.”

Is There Gender Bias in Stroke Care?

What are the statistics at your hospital? Are they even measuring anything? So if your hospital measures nothing, you have a fucking incompetent hospital. Ask your hospital president if s/he had a stroke and came to their hospital, 'What are the chances of you fully recovering?'

“What's measured, improves.” So said management legend and author Peter F. Drucker


Is There Gender Bias in Stroke Care?

HealthDay News -- Male stroke patients are more than twice as likely as female patients to receive tissue plasminogen activator treatment within 30 minutes of hospital arrival, according to research presented at the annual American Stroke Association's International Stroke Conference, held from February 22-24, 2016 in Houston, Texas.
Archit Bhatt, MD, MPH, a neurologist with the Providence Brain and Spine Institute in Portland, Ore., and colleagues evaluated 2695 stroke patients treated at one of 26 hospitals in the Pacific Northwest between 2009 and 2015. Only 3.9% had ultrafast door-to-needle times (<30 minutes).
Continue Reading Below
Three factors appeared to make a difference in whether or not stroke patients received ultrafast treatment: sex, arrival method, and arrival day. Men were 2.2 times more likely than women to get ultrafast treatment; patients arriving by ambulance were 4.7 times more likely to get the fast treatment than stroke patients driven to the hospital; and weekday arrivals were nearly twice as likely as those arriving during the evening or weekends to get ultrafast treatment.
Regarding the gender disparity, "We could not find a reason for the disparity," Dr Bhatt told HealthDay. "At least, there was nothing measurable in the database."

Reference

Bhatt A, Lucas L, Baraban E. Male gender predicts ultrafast administration of intravenous tissue plasminogen activator in a twenty-six hospital network. Presented at: 2017 International Stroke Conference. February 22-24, 2017; Houston, TX. Poster TMP88.

9 Habits of Emotionally Intelligent People

Doesn't your doctor want you emotionally intelligent? Is your doctor testing you for this to determine whether it needs to be improved so you can handle the craptastic current stroke rehabilitation environment? I would expect our stroke medical staff to know the correlation of recovery to EIQ.
http://www.livestrong.com/slideshow/1011291-9-habits-can-adopt-emotionally-intelligent-people/?
For many, emotions are bewildering -- they can be misread, affect judgment, trigger unexpected and perplexing behavior and sometimes completely overwhelm you. Emotionally intelligent people, however, are less challenged by feelings. Those with high emotional intelligence are able to recognize and express emotion, incorporate it into intellect and manage emotions in themselves and in others. In short, emotional intelligence is the ability to read feelings and respond in an appropriate way, says Tina B. Tessina, psychotherapist and author of “It Ends With You: Grow Up and Out of Dysfunction.” So how can you spot those with high emotional intelligence? The following are nine habits of emotionally intelligent people that help them excel in various aspects of their lives. So follow their lead and see where it takes you.

1.  THEY ARE SELF-AWARE

2.  THEY PRACTICE SELF-REGULATION

3.  THEY ARE EXTERNALLY AWARE

4.  THEY PRACTICE EMPATHY

5.  THEY ARE CURIOUS

6.  THEY ARE MOTIVATED AND MOTIVATE

7.  THEY MAINTAIN BOUNDARIES

8.  THEY ALLOW FOR DIFFICULT EMOTIONS

9.  THEY MANAGE THEIR EMOTIONS

Details at link.


How to Live 35 Years Longer

I bet your doctor is not telling you about any of these. Do not do on your own, it is way too dangerous to do healthy things without your doctors knowledge.

How to Live 35 Years Longer


Overview

Life’s too short. You may not have control over the giant meteor that hits you in the head while you’re walking down the street. But assuming your unlucky lottery number doesn’t come up, you have a remarkable amount of control over how long you live. It turns out, lifestyle is more important than genetics in determining how long you’ll live, according to a study from the University of Gothenburg published in the Journal of Internal Medicine.
And luckily, the lifestyle changes that can score you more years can also score you more quality years, according to Eudene Harry, M.D., medical director for Oasis for Optimal Health wellness center in Orlando and author of "Live Younger in 8 Simple Steps."
To that end, we found eight healthy habits that can add 35 years to your retirement plan.

Get More Friends: Add 7 Years


Use a Standing Desk: Add 2 Years

s.

Floss: Add 6 Years


Eat a Cup of Raw Veggies a Day: Add 2 Years


Think Positive: Add 7 Years


Eat More Nuts: Add 3 Years


Exercise Regularly: Add 5 Years


Details at the link.

Cognitive function decline in patients with acute stroke is not prevented by nimodipine

Then what the hell is the protocol to prevent cognitive decline? Keep after your doctor until you get a specific answer. This decline has been known for decades, has your doctor done one damn thing about finding a solution? Does s/he know about any of the following? Pure incompetence, stupidity, indifference or laziness?
Maybe these:

Exercise May Stave Off Cognitive Decline by 10 Years

Growth Factor in Brain Tied to Slower Mental Decline

Omega 3 fatty acid for the prevention of cognitive decline and dementia

probiotics and tryptophan may slow down social cognitive decline in aging. 

Study shows that IVIG could prevent brain atrophy, delay onset of Alzheimer's disease

Systematic review shows ‘smart drug’ modafinil does enhance cognition

Eating away at cognitive decline: MIND diet may slow brain from aging by 7.5 years

10 Ways to Rev Up Your Brain and Reduce the Risk of Cognitive Decline

You can compare these to mine.
Dementia prevention 19 ways


http://www.healio.com/cardiology/stroke/news/online/%7B74692799-b80b-48ad-a8ef-7b14e75fd3aa%7D/cognitive-function-decline-in-patients-with-acute-stroke-is-not-prevented-by-nimodipine?

The calcium antagonist nimodipine did not prevent the decline of cognitive function in patients with acute stroke and mild cognitive impairment, according to a study presented at the International Stroke Conference.
Huahuang Zheng , MD, from the Capital Medical University in Beijing, and colleagues conducted a randomized, double blind, placebo-controlled trial at 23 sites across China.
The study included patients between the ages of 30 and 80 years who had a Mini-Mental State Examination (MMSE) score greater than dementia threshold corrected based on educational year, Montreal Cognitive Assessment (MoCA) scores less than 26 for more than 12 educational years and Hachinski scores of 7 or more.
Patients were randomly assigned to receive either 30 mg nimodipine (n = 329) 3 times per day or placebo (n = 325).
The primary endpoint of the study was change in cognitive function as determined by MMSE and Alzheimer’s Disease Assessment Scale – cognitive subscale (ADAS–Cog).
Secondary endpoints included changes in score from baseline to 6 months of MoCA and frontal assessment battery.
Zheng said there was no significant difference between the groups in MMSE –3 (OR = 0.56; 95% CI, 0.27-1.26), MMSE 0 (OR = 0.76; 95% CI, 0.55-1.07) or ADAS-Cog 4 (OR = 0.93; 95% CI, 0.52-1.66). For the outcome of ADAS-Cog 0, 34.15% of those assigned nimodipine achieved that threshold vs. 46.74% of those assigned placebo (OR = 0.59; 95% CI, 0.42-0.83).
Key secondary endpoints did not differ between the nimodipine and placebo groups (MoCA: nimodipine group, 1.89; placebo group, 1.66; P = .35; frontal assessment battery: nimodipine group, 0.85; placebo group, 0.67; P = .32).
“Vascular mild cognitive impairment in acute ischemic stroke patients might not benefit from nimodipine in prevention of cognitive function decline when treated 1 week after onset of stroke,” Zheng said during the presentation. “However, nimodipine might have a marginal positive effect on some specific cognitive domains and did not increase risk of stroke and other adverse events.”– by Dave Quaile
Reference:
Zheng H, et al. LB7. Presented at: International Stroke Conference; Feb. 22-24, 2017; Houston.
Disclosure : The study was funded in part by Bayer HealthCare Pharmaceuticals China. Zheng reports receiving research grants from the National Key Technology Research and Development program of the Ministry of Science and Technology of China.

The Clemson entrepreneurs behind Recovr help stroke survivors with a video game

I still prefer the cockroach stomping game.

The Clemson entrepreneurs behind Recovr help stroke survivors with a video game


For stroke victims, therapy can be physically and mentally exhausting as they repeat the same workouts day in and day out just to regain their ability to complete the simplest of tasks, such as picking up a pencil.
But Clemson’s Recovr Inc. is turning physical therapy into a game, not a chore.
Five years ago, Austen Hayes, then a graduate student at Clemson University’s College of Engineering and Science, and Larry Hodges, a computing professor, teamed up and created the computer game “Duck, Duck, Punch.”
The game aims to improve the arm mobility of stroke patients, who sit or stand in front of a television or computer and hit rubber ducks as they go by on the screen. When patients reach out, a virtual arm on the screen knocks down the ducks, earning them points.
“We’re on the cusp of something big,” says Hayes, the company’s CEO. “There is a $17-billion stroke rehabilitation market in the U.S. alone. The need for this kind of therapy is expected to more than double by 2030, according to the National Stroke Association.”
About 800,000 strokes happen each year in the United States, with more than 7 million survivors suffering a long-term stroke disability. In many cases, stroke patients become discouraged when they can’t perform the tasks they once completed easily and discontinue their treatment after leaving therapy.
Patients usually do only 10 percent of the recommended daily therapy exercises, Hayes says. “Duck, Duck, Punch,” which can be played in hospitals and homes, has increased their exercise repetitions during pilot studies.
“It has just blown away therapists that patients are following up on their own between therapy sessions,” Hayes says. Some studies have revealed at least a 15 percent improvement in arm mobility in one week of using the game.
When Greenville resident Nancy Bunch suffered a stroke, she spent weeks in recovery, unable to move her arm. Then her therapist had her play the game, and one year later, she was able to drive herself to the grocery store.
“This really needs to be in hospitals all around the country,” Bunch says. “For me, it represented hope, hope for the hopeless. I am so thankful.”
The company recently received approval from the FDA to market the game as a medical device, now called the Recovr Rehabilitation System. It allows therapists to use the game to record patient progress and provide analytic data.
Recovr has received thousands of dollars in startup capital from Greenville’s Concepts to Companies, a firm that focuses on transforming academic ideas into commercial enterprise by investing capital and offering business expertise.
“It shows that South Carolina has high-quality intellectual capital. There is a huge need for this kind of product, and it’s growing. We’re expecting big things from Recovr,” says John Warner, Concepts to Companies founder and Recovr Inc. director.
The game is currently used by the Medical University of South Carolina and various other facilities throughout the country.
Hayes says Recovr plans to expand by creating new games that could help patients suffering from multiple sclerosis, Parkinson’s disease, and more.

Cannabinoids as Regulators of Neural Development and Adult Neurogenesis

It is cannabinoid based thus will never make it past our idiotic federal legislators having marijuana as a Class I drug.  I bet you have to go to Europe to try it. But ask your doctor how to take advantage of this. Bet you don't get an answer. 
http://link.springer.com/chapter/10.1007/978-3-319-49343-5_6
  • Alline C. Campos 
  • , Juan Paraíso-Luna
  • , Manoela V. Fogaça
  • , Francisco S. Guimarães
  • , Ismael Galve-Roperh
$29.95 / €24.95 / £19.95 *
Buy eBook
$189.00 / €161.19 / £115.50*
* Final gross prices may vary according to local VAT.
Get Access

Abstract

Neurogenesis plays an indispensable role in the formation of the nervous system during development. The discovery that the adult brain still maintains neurogenic niches that allow the continued production of new cells after birth has changed the field of neuroscience. It has also opened a new venue of opportunities for the treatment of central nervous system disorders related to neuronal loss. This chapter has reviewed the studies showing that genetic or pharmacological manipulation of cannabinoid receptors (CB1 and CB2) or the enzymes responsible for endocannabinoid metabolism modify/regulate cell proliferation and neurogenesis during development and in the adult brain. A better characterization of the mechanisms involved in these effects could contribute to the development of new therapeutic alternatives to neurodegenerative and psychiatric disorders.

Accelerometer-Based Recorder of Fingers Dynamic Movements for Post-Stroke Rehabilitation

Measurement only so useless for patients like me with spasticity preventing extension of the fingers. 

Accelerometer-Based Recorder of Fingers Dynamic Movements for Post-Stroke Rehabilitation


Fajar Akhmad Dwiputra, Balza Achmad, - Faridah, - Herianto

Abstract


Stroke is a disease that currently attracts more attention in Indonesia according to the statistics provided by the Ministry of Health of the Republic of Indonesia. This research was motivated by the shortage of physiotherapists which can not catch the increasing number of stroke patients. The therapy becomes less effective and less efficient since each therapist must handle too many patients during his/her work hours. This research has developed a device prototype that can help the therapy to measure and monitor patient exercise, especially at the final stage of rehabilitation when the patient gets therapy to move actively. The angle of the moving body parts  that can represent the ability of patient motion was measured using accelerometers. The developed prototype was in the form of a glove, equipped with an Arduino Nano and two accelerometer modules, that measures the motion of the thumb and index finger. The device was calibrated and tested to determine the characteristics of the sensors. This test showed that the gloves prototype had an accuracy of 95,8% and precision of 99,6%. The application of the prototype was carried out on four types of finger movements, namely thumb abduction-adduction, thumb flexion-extension, finger flexion-hyperextension, and finger abduction-adduction. The prototype was also tested for its ability to work in variations of direction and position of the hand.

Keywords


accelerometer; active rehabilitation; finger movement; post-stroke; physiotherapy.

Full Text:

PDF


DOI: http://dx.doi.org/10.18517/ijaseit.7.1.1973

Predicting rehabilitation treatment helpfulness to stroke patients: A supervised learning approach C

Prediction and prognosis of treatment helpfulness does absolutely nothing for stroke survivors. If you are a survivor with major deficits you will be shunted aside since current therapies can't help you very much. Only the 'good strokes' need apply.
http://www.sciedupress.com/journal/index.php/air/article/viewFile/10668/6807

Architecture guideline for game-based stroke rehabilitation

Useless because this is a review and not relevant for protocols for survivors.
http://www.emeraldinsight.com/doi/abs/10.1108/WJSTSD-06-2016-0039
Author(s):
Mehran Kamkarhaghighi ( University of Ontario Institute of Technology OShawa Canada ) ( Canada )
Pejman Mirza-Babaei ( University of Ontario Institute of Technology OShawa Canada )
Khalil El-Khatib ( University of Ontario Institute of Technology OShawa Canada )
Kathrin M Gerling ( University of Lincoln Lincoln United Kingdom of Great Britain and Northern Ireland )
Citation:
Mehran Kamkarhaghighi , Pejman Mirza-Babaei , Khalil El-Khatib , Kathrin M Gerling , (2017) "Architecture guideline for game-based stroke rehabilitation", World Journal of Science, Technology and Sustainable Development, Vol. 14 Iss: 2/3, pp. -
Downloads:
The fulltext of this document has been downloaded 1 times since 2017
Abstract:
Strokes are the most common cause of long-term disability of adults in developed countries. Continuous participation in rehabilitation can alleviate some of the consequences, and support recovery of stroke patients. However, physical rehabilitation requires commitment to tedious exercise routines over lengthy periods of time, which often cause patients to drop out of this form of therapy. In this context, game-based stroke rehabilitation has the potential to address two important barriers: accessibility of rehabilitation, and patient motivation.
This paper provides a review of design efforts in human-computer interaction (HCI) and gaming research to support stroke rehabilitation.
Based on extensive review, this paper highlights challenges and opportunities in this area, and discusses an architecture guideline for a game-based stroke rehabilitation system.
This study was an original study.
Publisher:
Emerald Group Publishing Limited
Copyright:
© Emerald Group Publishing Limited 2017
Published by Emerald Group Publishing Limited

Vagus Nerve Stimulation Falls Short in Stroke Rehabilitation

Really? Then what the fuck what is a clinically meaningful change? Because nothing in this writeup suggests failure. Fugl-Meyer is totally useless in measurement of recovery, stop using it you fucking idiots.
http://journals.lww.com/neurotodayonline/blog/neurologytodayconferencereporterinternationalstrokeconference/pages/post.aspx?PostID=16
BY ED SUSMAN
HOUSTON—The use of vagus nerve stimulation to help patients who have limited arm movement had mixed but promising results in a blinded, randomized sham-controlled trial, researchers reported here on Friday at the 2017 International Stroke Conference sponsored by the American Heart Association/American Stroke Association.
The randomized trial failed to achieve its primary endpointa clinically meaningful change in scores in the upper-limb Fugl-Meyer scale, which assesses motor recovery, sensory functioning, balance, joint range of motion, and joint pain, after stroke — 30 days after vagus nerve stimulation. [Motor scores ranges from 0 (hemiplegia) to 100 points for normal motor performance.] But at 90 days, there were significant differences in the Fugl-Meyer scale between those who received the active and sham treatments, said Jesse Dawson, MD, a consultant at the Institute of Cardiovascular and Medical Services of the University of Glasgow in Scotland.
At 90 days, patients getting the stimulation showed a significant improvement of 9.5 points on the Fugl-Meyer score compared to an improvement of 3.8 points for those patients getting a sham treatment.
The research team enrolled patients who had experienced an ischemic stroke and had severe arm weakness four months to five years after the initial event. The patients were assessed at one day, 30 days, and 90 days after completing six weeks of rehabilitation training and home exercise. Eight patients were fitted with vagus nerve stimulators, but the devices in nine control patients were not turned on until after the study was completed.
Despite the failure to achieve the study's primary endpoint, Dr. Dawson said that the other secondary endpoints were good enough to encourage the researchers to plan a 120-patient pivotal study, which will begin recruiting in the summer.
He noted that experimental models indicated that vagus nerve stimulation improved outcomes in animals with various types of strokes. In a previous 20-patient pilot study, it appeared that motor function improved, suggesting that the treatment was feasible and that it warranted moving forward to the current trial.
"We have seen that the results of vagus nerve stimulation are consistent across two small trials," he said at a news briefing prior to his presentation. "This technique is acceptably safe and in-clinic and home-based vagus nerve stimulation is feasible."
Commenting on the study, Philip Gorelick, MD, MPH, FAAN, medical director of the Hauenstein Neuroscience Center and clinical professor of translational science at Michigan State University College of Human Medicine in Grand Rapids, said the study is very promising, but a lot more work is needed.
"Arm movements are very critical to better functional outcome for our patients, so this is a great target," he said. "I'd like to see a quality-of-life study on this project, specifically to determine if this improvement helps patients to do things with their fingers, rather than just move their arm more," said Dr. Gorelick.
Functional magnetic resonance imaging studies would be helpful as well, he said, "so we can understand how the brain is reorganizing when it receives these stimulations."
Dr. Dawson said the Canadian group is planning to conduct these studies with the next trial.
The study was funded by Micro Transponder, Inc.
LINK UP FOR RELATED INFORMATION:​​

Saving Brain Cells From Stroke - P7C3

I bet this didn't make our non-existent stroke leaders ears perk up and get to writing an RFP to researchers to test this out in humans. Of course not, SOMEONE ELSE WILL TO SOLVE THE PROBLEM. Our fucking failures of stroke associations don't even have two functioning neurons to know that they are totally fucking useless to survivors.
http://neurosciencenews.com/stroke-p7c3-neurons-6194/

Summary: A compound called P7C3 provides both protection for neurons following a stroke and improves physical and cognitive outcomes, a new study reports.
Source: University of Iowa Health Care.
P7C3 compound protects mature and newborn neurons in rats, and also improves physical and cognitive outcomes, following stroke.
Researchers from the University of Iowa Carver College of Medicine and the University of Miami Miller School of Medicine have shown that a neuroprotective compound tested in rats provides two-pronged protection for brain cells during stroke and improves physical and cognitive outcomes in the treated animals.
Every year, nearly 800,000 Americans have a stroke and almost 130,000 die. Survivors often are left with long-term physical and cognitive disability that significantly alters their lives.
When a stroke interrupts the brain’s blood supply, mature brain cells (neurons) die. In addition, reestablishing blood flow, known as reperfusion, also leads to processes that cause cell death. A part of the brain’s natural response to stroke injury is to increase production of new brain cells in two specific regions (the subgranular zone of the hippocampal dentate gyrus and the subventricular zone of the lateral ventricles), which normally make a smaller number of new brain cells every day. Unfortunately, the vast majority of these newborn cells die within one to two weeks, limiting the benefit of this potential repair process. Minimizing the loss of brain cells is a primary goal for new stroke therapies.
“If we could prevent the mature brain cells from dying that would be beneficial,” says Andrew Pieper, MD, PhD, professor of psychiatry in the UI Carver College of Medicine and co-senior study author. “But if we could also support or enhance this surge in neurogenesis (birth of new neurons), we might be able to further foster recovery, especially in terms of cognitive function, which is critically dependent on the hippocampus.”
Using rats, Pieper and his colleagues Zachary B. Loris and W. Dalton Dietrich, PhD, tested the effects of a compound called P7C3-A20 on these two aspects of neuroprotection following ischemic stroke. Blood flow to the rats’ brains was interrupted for 90 minutes and then the blockage was cleared allowing reperfusion. One group of rats was given the P7C3-A20 compound twice daily for seven days following the stroke. P7C3-A20 has previously been shown to prevent brain cell death in other animal models of neurologic injury, including Parkinson’s disease, amyotrophic lateral sclerosis, stress-associated depression, and traumatic brain injury.
In terms of the brain itself, the P7C3-A20 compound reduced loss of brain tissue (atrophy) and increased survival of newborn neurons six weeks after stroke. In addition to the improved survival of both mature and newborn neurons, rats that received the P7C3-A20 compound for seven days after stroke also had better physical and cognitive outcomes than untreated rats. Treated rats had improved balance and coordination one week after stroke, and improved learning and memory one month after stroke. The findings were published recently in the journal Experimental Neurology.
“There is no previous demonstration of a pharmacologic agent that both protects mature neurons from dying and also boosts the net magnitude of neurogenesis,” Pieper says. “Our compound is beneficial in this animal model of stroke, and we’re hopeful that it might eventually benefit patients.”
“Currently there are limited treatments for acute stroke that make a real difference in patient’s lives. There is an urgent need to identify, test, and translate new therapies to the clinic,” adds Dietrich, co-senior study author and Scientific Director of The Miami Project to Cure Paralysis, professor of neurological surgery, neurology, biomedical engineering and cell biology at the University of Miami where the studies were conducted. “The ability to both protect and repair the injured nervous system has major implications on how we think about improving outcomes in millions of people each year with acute neurological injuries.”
The neuronal protection provided by the P7C3-A20 compound was also associated with a boost in the levels of a substance called nicotinamide adenine dinucleotide (NAD) in the rats’ brains. NAD is emerging as an important player in neuronal health and survival. Levels of this substance are depleted during stroke, and it has been proposed that increasing NAD levels may be a therapeutic target for treating stroke. In this study, P7C3-A20 treatment restored NAD to normal levels in the rats’ cortex after a stroke.
Importantly, the study examined the effects of P7C3-A20 on cognitive and physical outcomes well beyond the time of the initial stroke. The sustained physical and cognitive improvement seen in the rats up to one month after the stroke suggests that the P7C3-A20 compound provides a long-term benefit.